


 Shahriar Lahouti
3 November 2026, by Shariar Lahouti.

📖CONTENTS
- Introduction
- 🧐Clinical Vignette
- Official Definition
- Peripheral vs. Central Causes
- Dizziness characterization
🩺Approach to Diagnosis & Management
- Overview
- STEP 1: Screen for Central & Medical Red Flags
- STEP 2: Syndromic Classification
- AVS
- Episodic syndromes
- STEP 3: Bedside Vertigo Test
- 🩻Diagnostic Imaging
- Specific Conditions
- Treatment
- 🏥Disposition
💡Case Resolution and Clinical Pearls
📚References
Introduction
Dizziness is an imprecise term and a common symptom of many disease processes. The presentation of dizziness, imbalance, vertigo, or lightheadedness accounts for roughly 4% of all United States ED visits. “Dizziness” is a highly nonspecific term that can mean many different things to different patients. The differential diagnosis of dizziness should not be based on symptom quality (e.g., lightheadedness, vertigo, or imbalance) because these descriptors are unreliable. Patients often provide vague and inconsistent descriptions, and warning signs such as visual field deficit or hearing loss may be subtle. Most vertigo encountered in the ED arises from benign peripheral disorders, chiefly benign paroxysmal positional vertigo (BPPV) or vestibular neuritis, yet approximately 3–6% harbor a serious central etiology. Among these, posterior circulation stroke represents the most consequential diagnosis to overlook. Having said that, sometimes it is challenging to differentiate the benign from dangerous causes of vertigo in the ED. This review provides a guide to the differential diagnosis and diagnostic approach to vertigo, informed by recent guidelines *.
Clinical Vignette
Official Definition
“Dizziness” is a non-specific term used inconsistently by patients; approximately 50% of ED patients change their description of the symptom within the same visit. Symptom quality alone is therefore unreliable for risk stratification; the question “what do you mean by dizzy?” may serve as an entry point but cannot guide diagnosis in isolation. For standardized communication, the International Classification of Vestibular Disorders (ICVD) defines *, *
- Dizziness
- Disturbed or impaired spatial orientation (patients often also use this term for lightheadedness, presyncope, “brain fog,” or nausea).
- Vertigo
- Sensation of self-motion when none is occurring, or distorted self-motion during otherwise normal head movement.
- Disequilibrium (unsteadiness)
- Feeling unstable while seated, standing, or walking.
- Ataxia
- Impaired voluntary coordination of muscle movement (truncal or limb). It can involve the trunk, limb, or gait *.
Peripheral vs. Central Causes
Neuroanatomy
👂Peripheral Apparatus
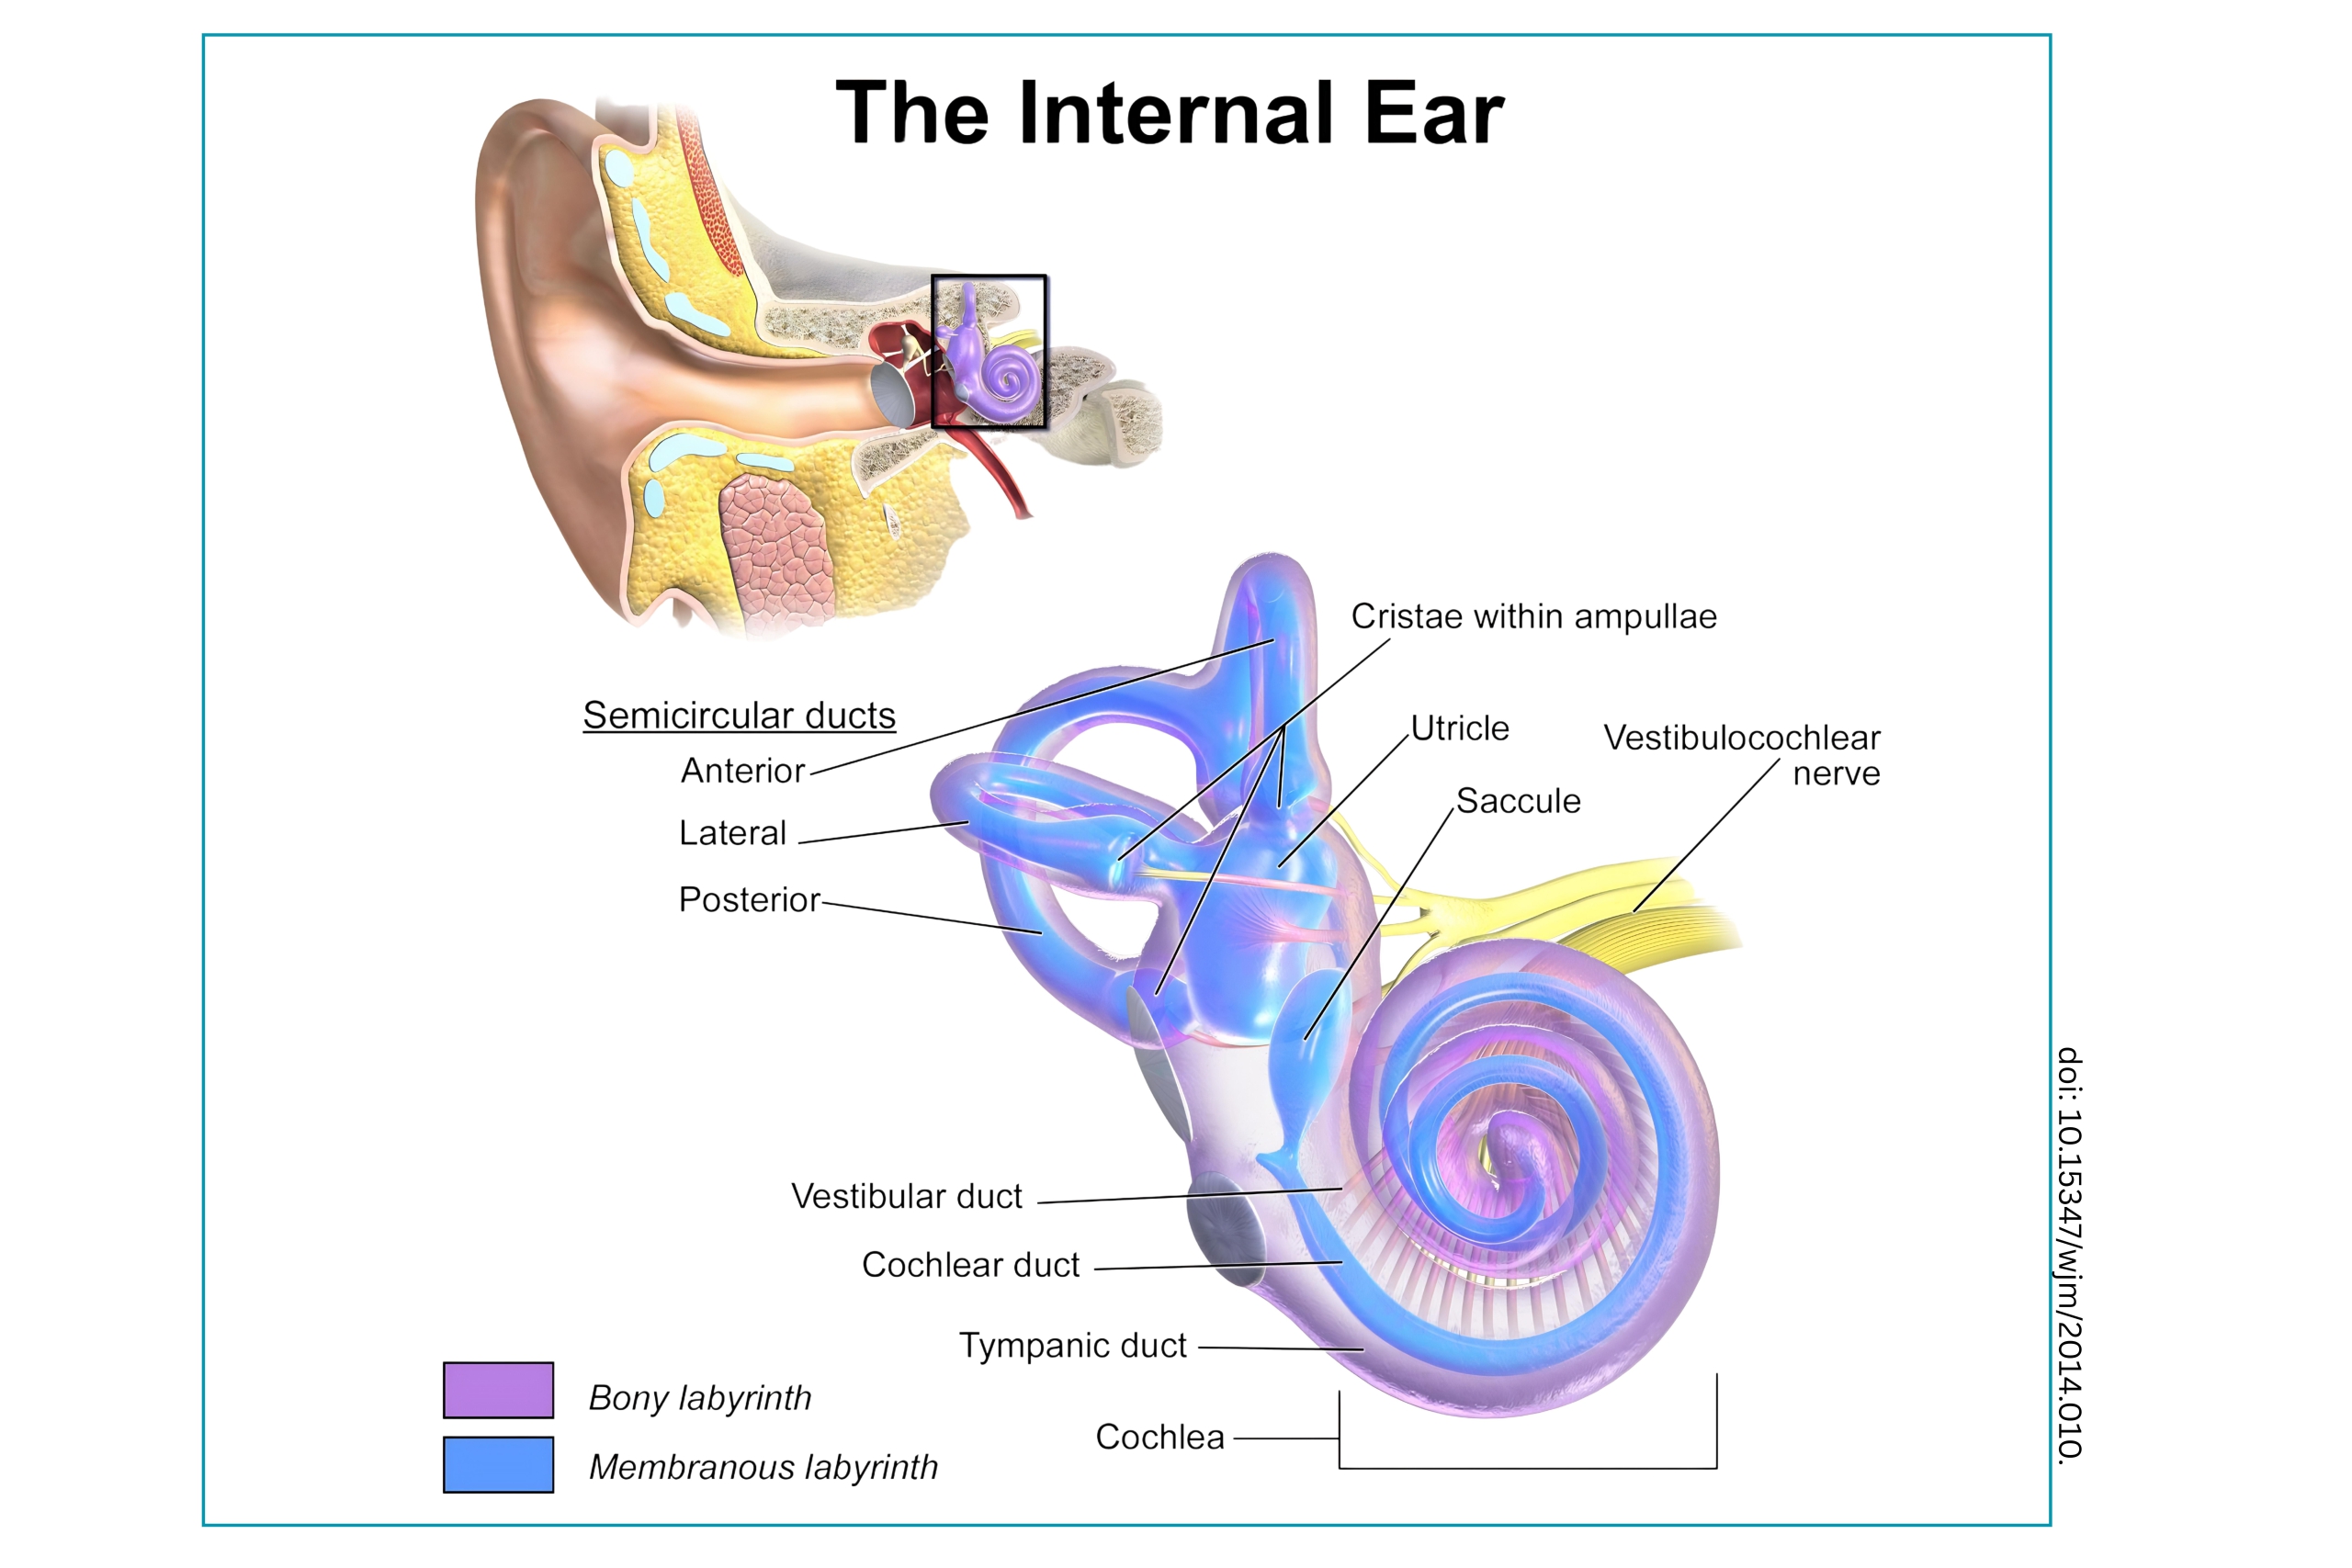
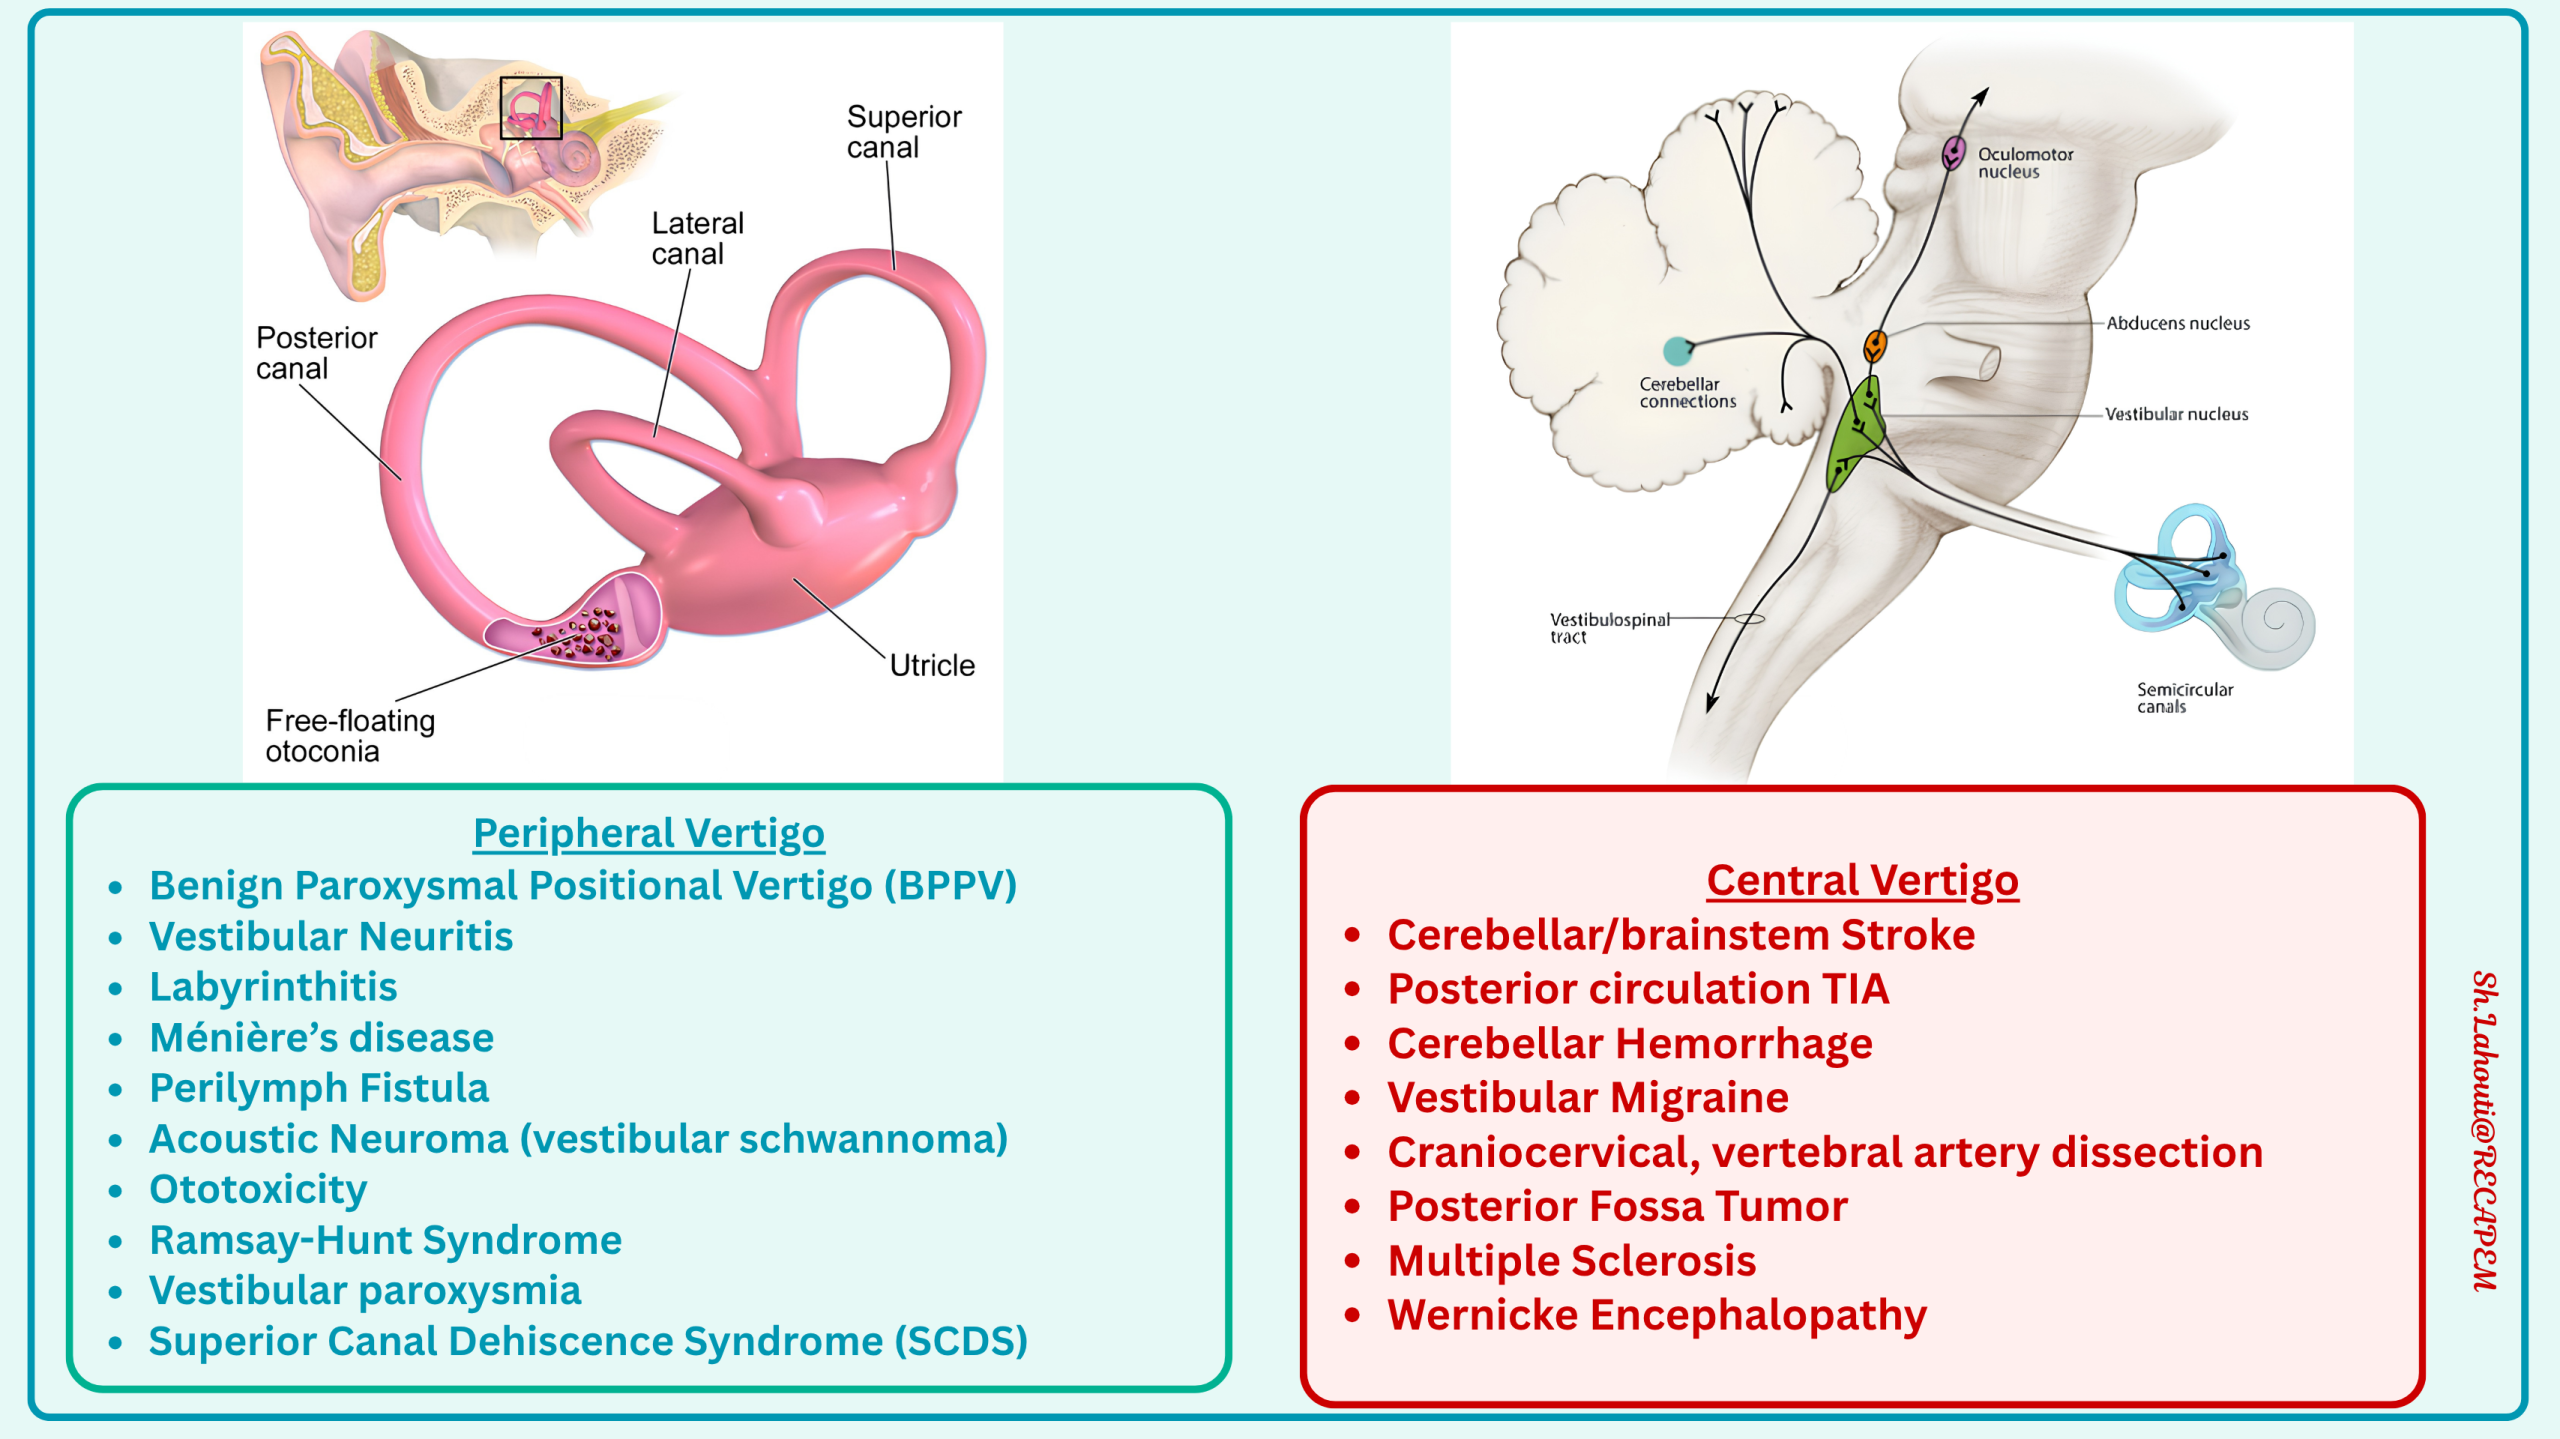
The vestibular system begins in the inner ear (the labyrinth), consisting of the semicircular canals (detecting angular acceleration) and the otolith organs (utricle and saccule, detecting linear acceleration and gravity). Signals from these structures travel via the vestibular nerve (CN VIII), specifically its superior and inferior divisions, to the brainstem. 🖼️ Left figure below.
🩸Arterial Supply of peripheral apparatus
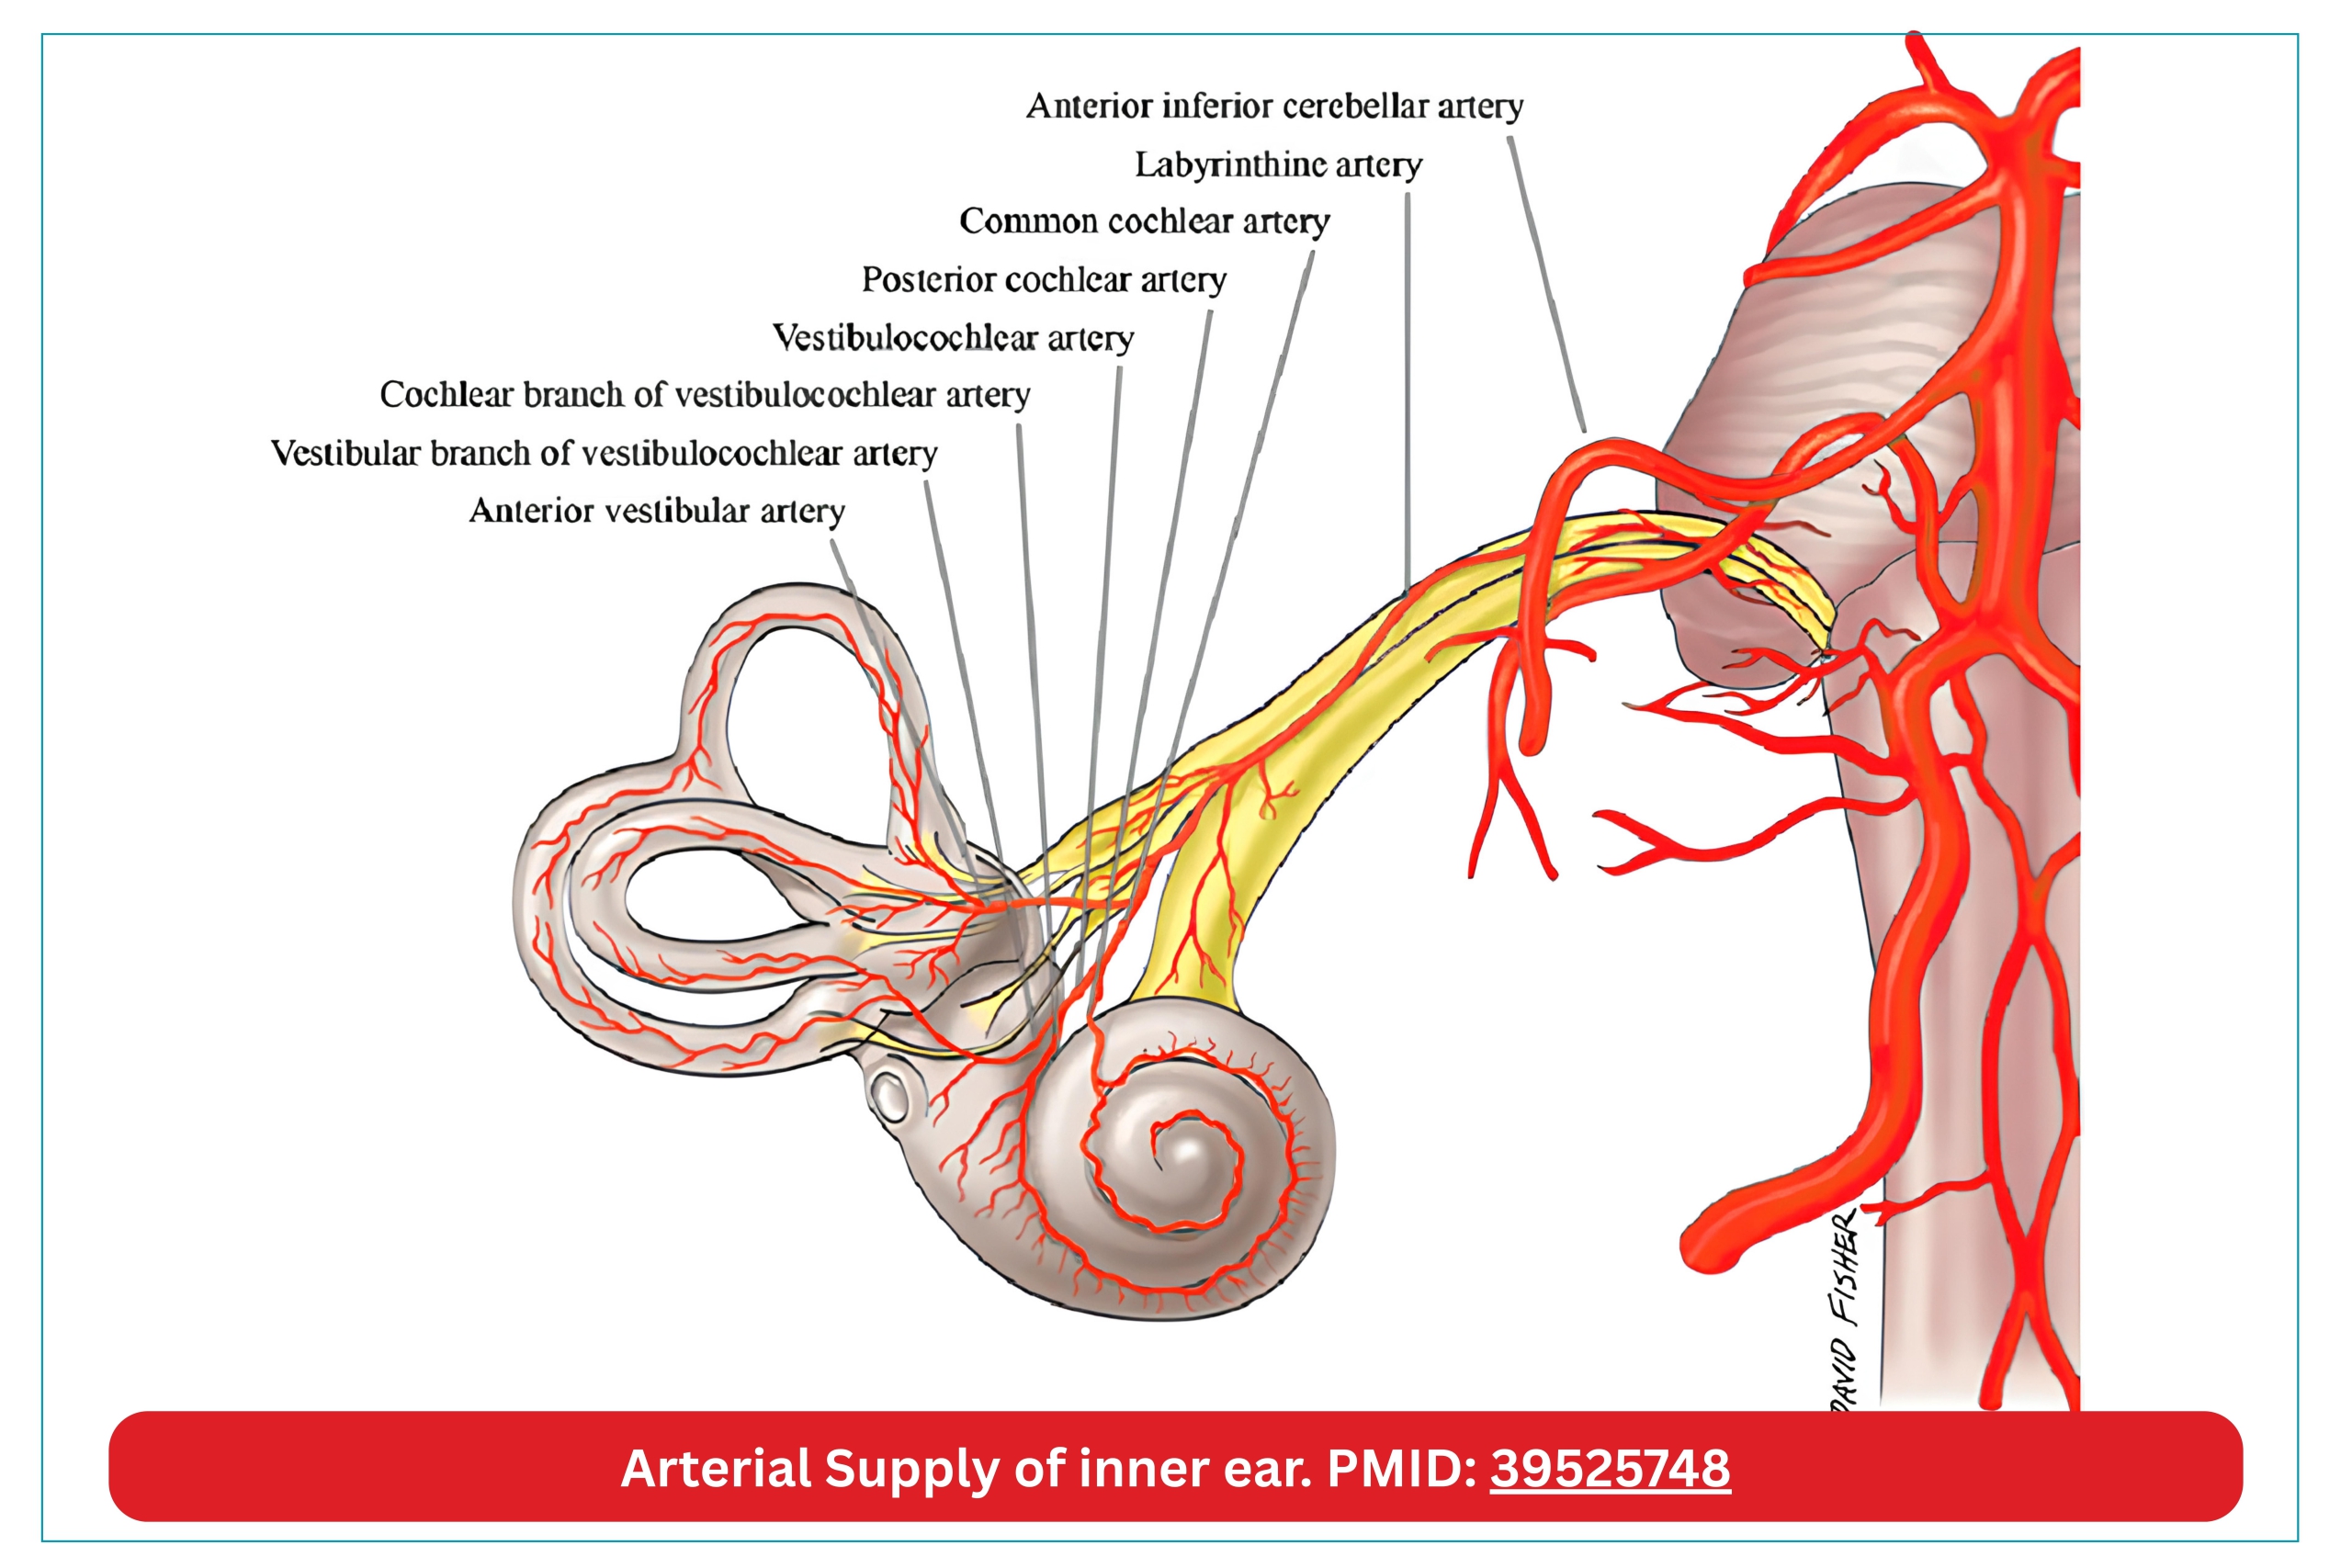
- Inner Ear (peripheral apparatus): Labyrinthine artery (aka. internal auditory artery)
- Origin: It usually branches off the AICA in the cerebellopontine angle.
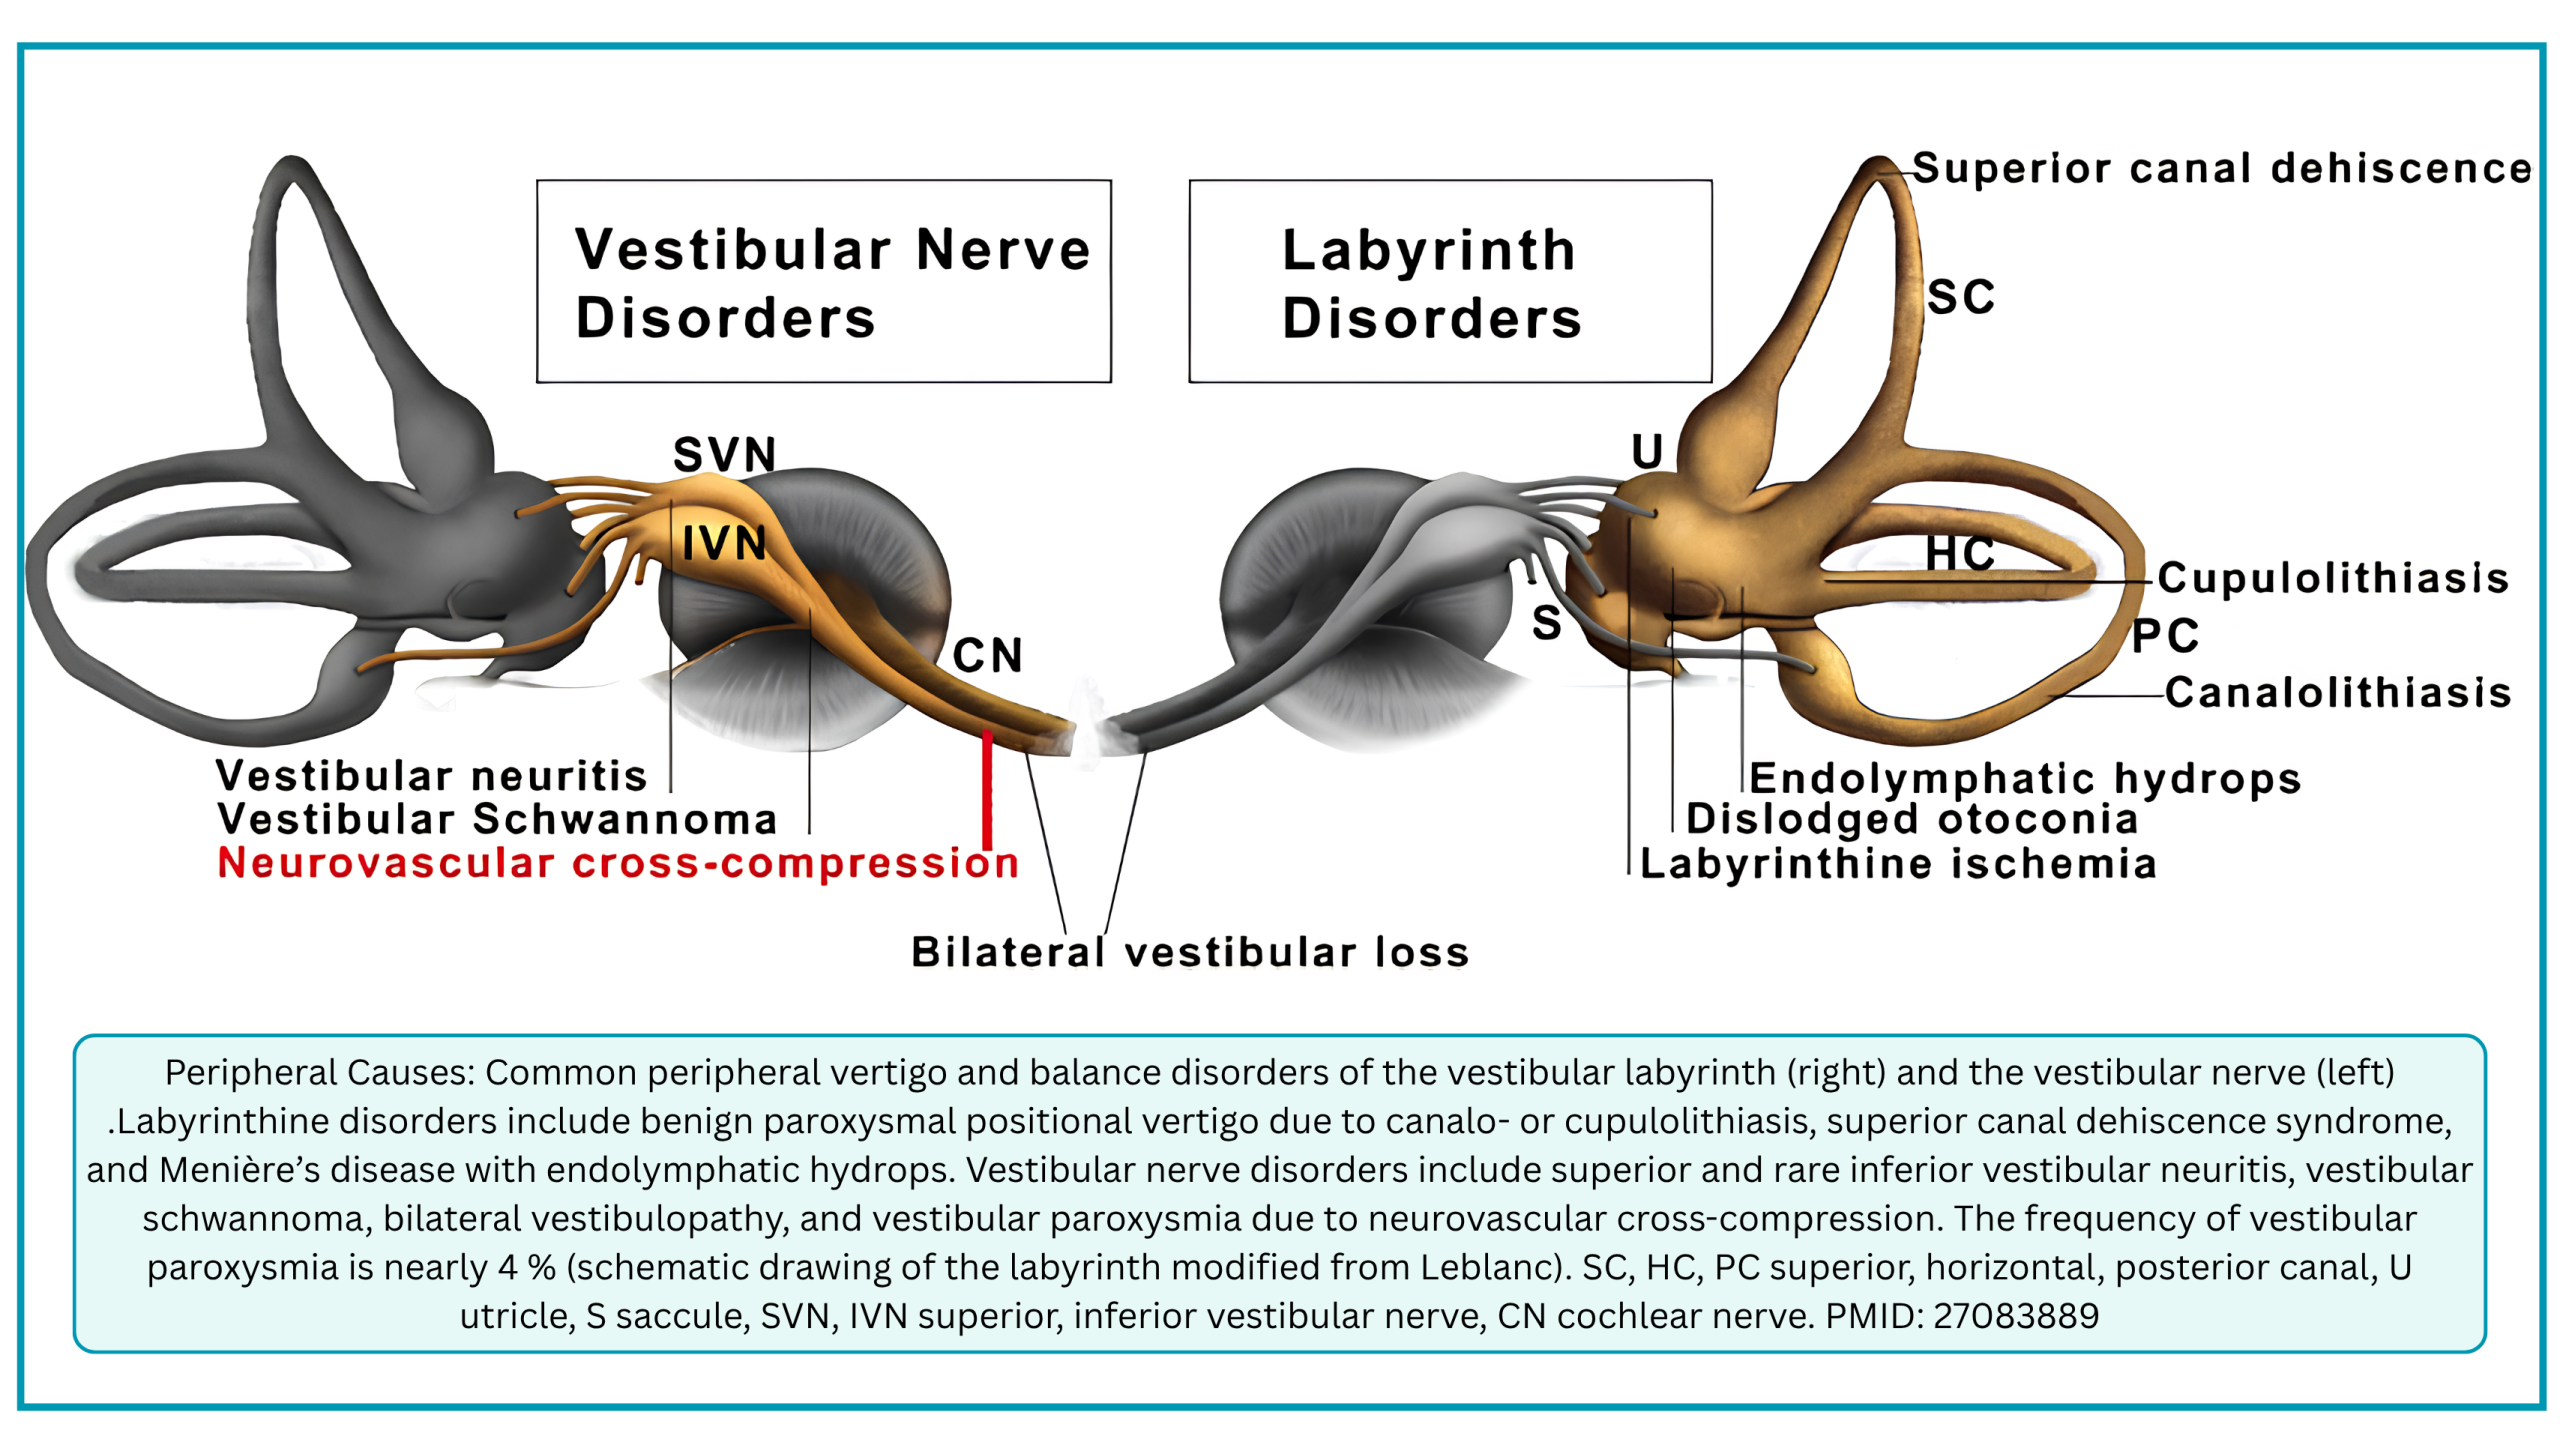
- Course and Function: It travels through the internal acoustic meatus alongside the vestibulocochlear nerve (CN VIII) and facial nerve (CN VII). It is the sole blood supply to the inner ear (labyrinth), which includes the cochlea (hearing) and the vestibular apparatus (balance). 🖼️ Middle figure below.
- 🩺Clinical Significance:
- This anatomy is precisely why AICA infarction causes the classic combination of vertigo plus unilateral hearing loss *.
- Unlike PICA strokes (which typically spare hearing), an AICA stroke knocks out the labyrinthine artery, leading to ischemia of both the vestibular and auditory structures. This is the anatomical basis for the “HINTS Plus” examination (which adds a bedside hearing assessment to detect AICA strokes).
🧠Central Apparatus
Brain stem
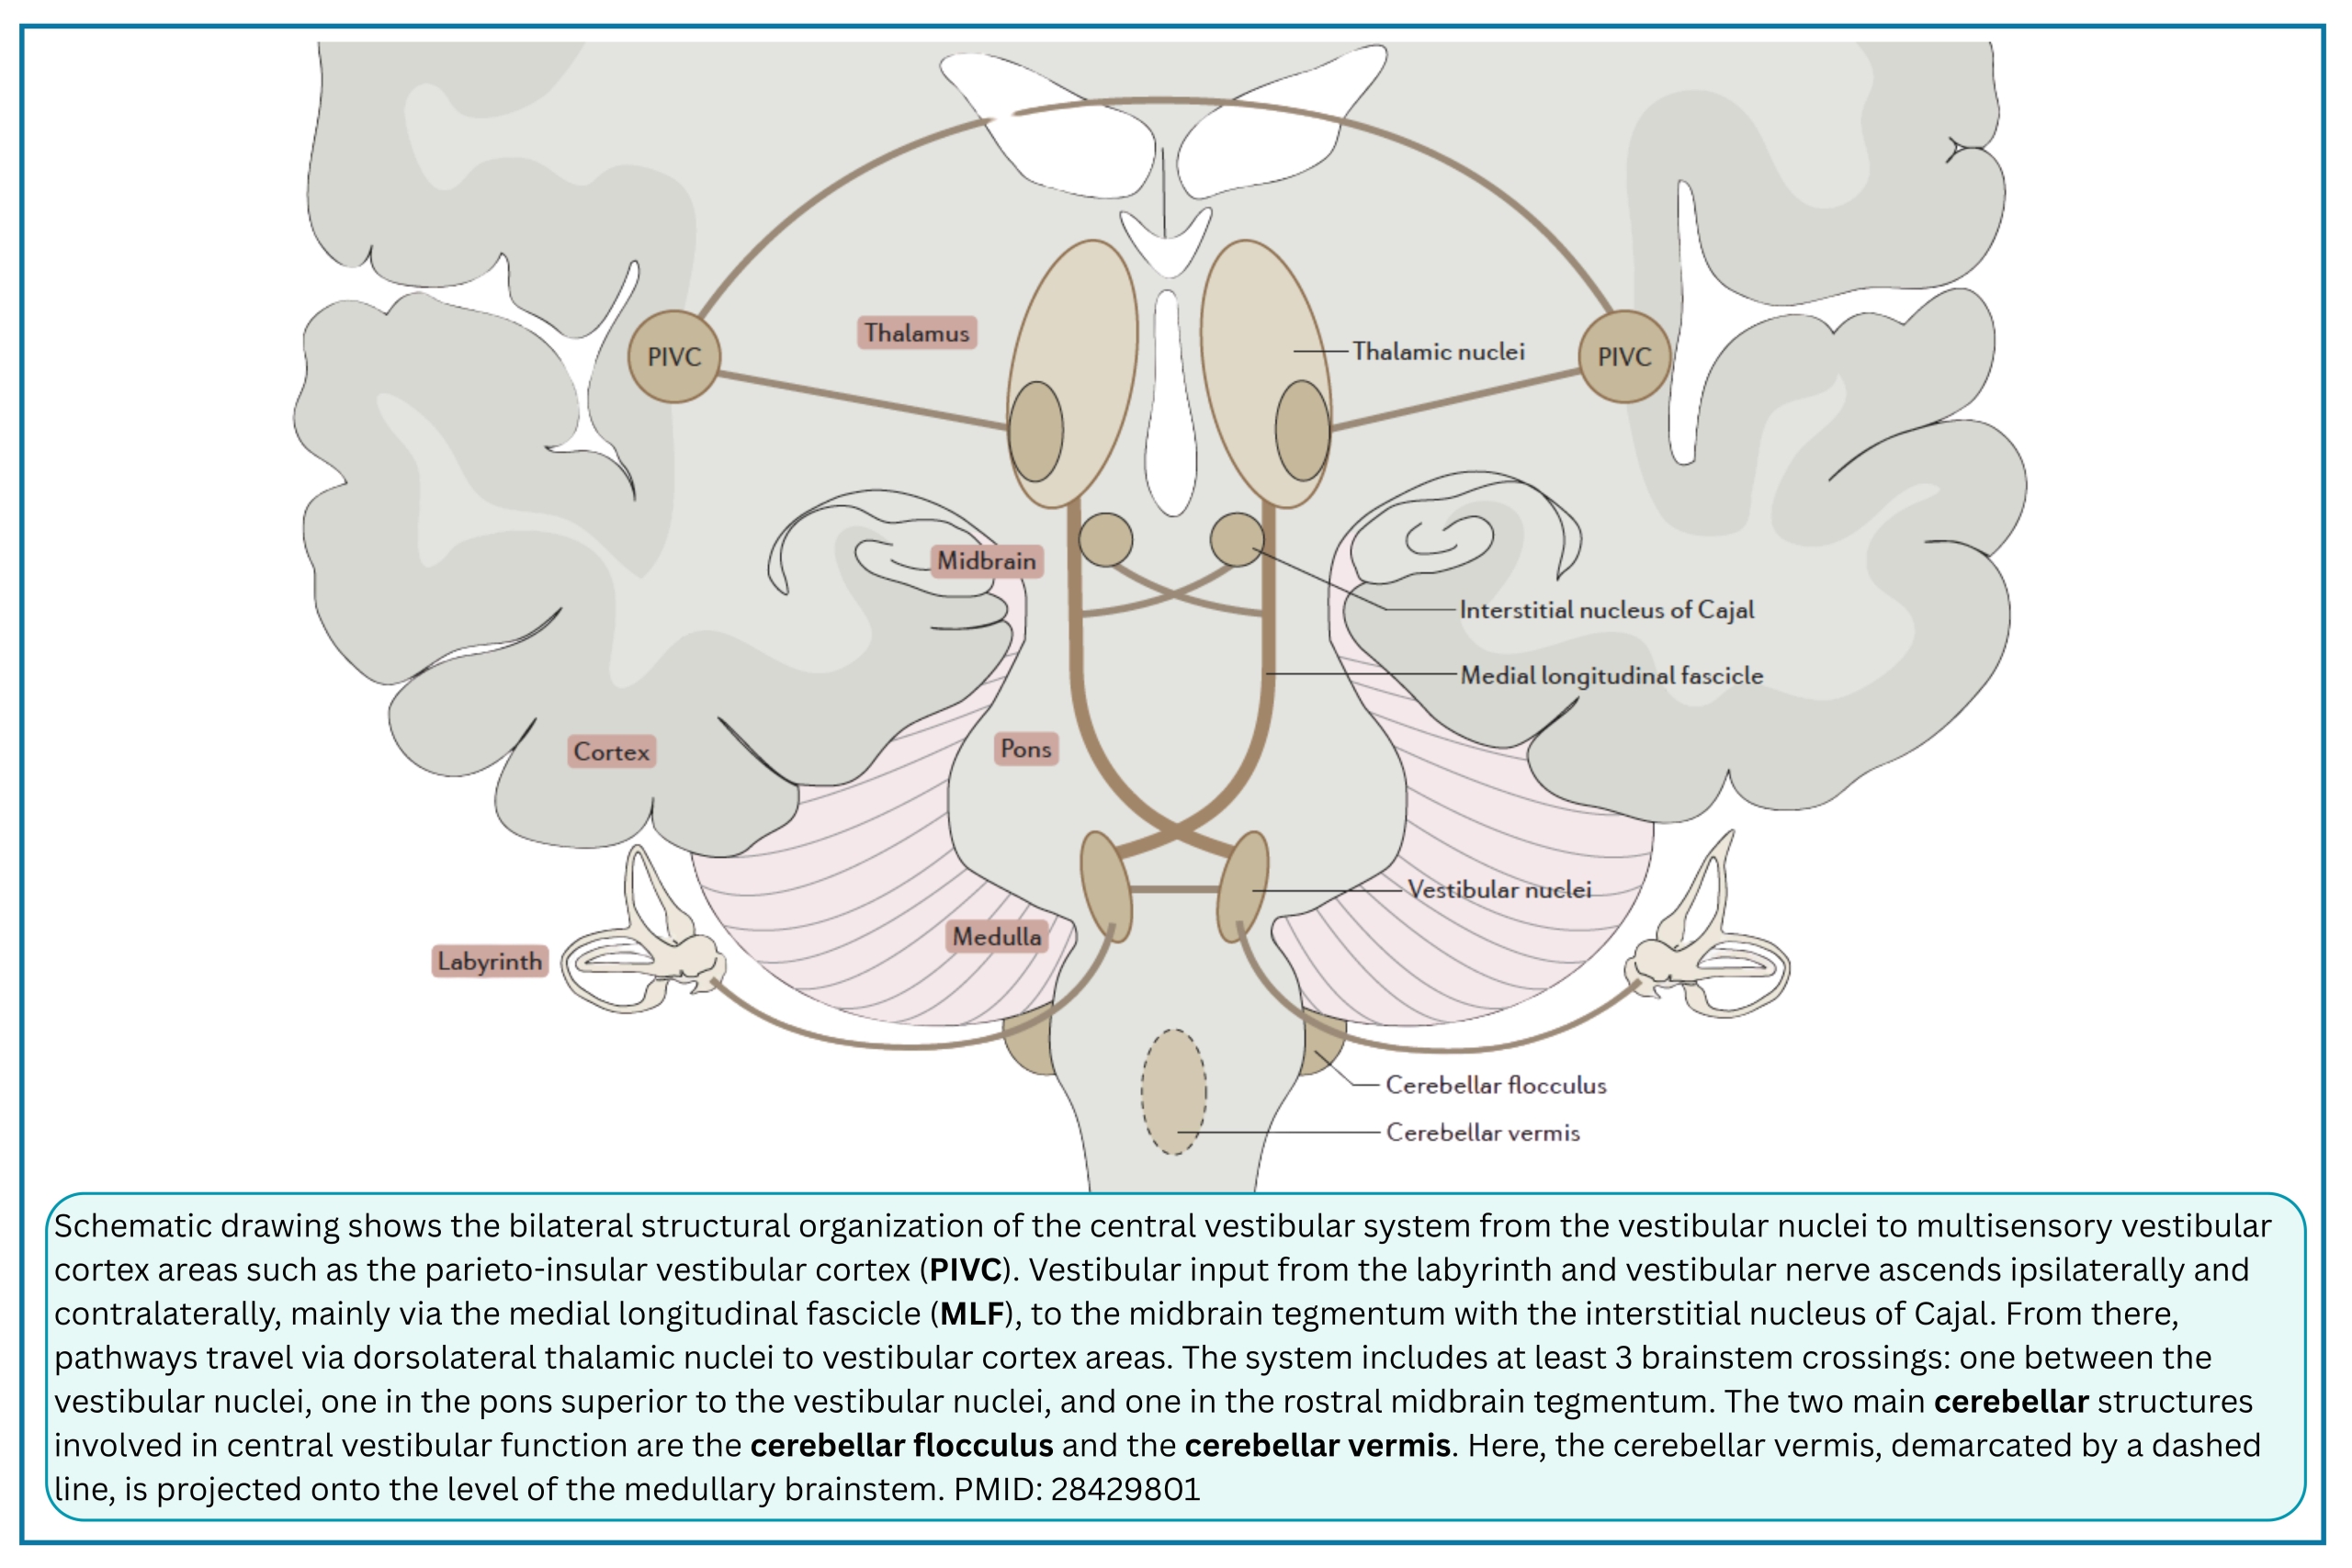
- The vestibular nerve enters the brainstem at the pontomedullary junction and synapses at the vestibular nuclei. From there, second-order neurons project via three main pathways (🖼️Right figure below):
- Vestibulo-ocular reflex (VOR): Projections to the ocular motor nuclei (CN III, IV, VI) stabilize gaze during head movement (the basis for the Head Impulse Test).
- Vestibulospinal tracts: Projections to the spinal cord maintain posture and truncal stability.
- Thalamocortical pathways: Projections ascend through the brainstem (including the medial longitudinal fasciculus and interstitial nucleus of Cajal) to the thalamus, and ultimately to the parieto-insular vestibular cortex (PIVC) and hippocampus for spatial orientation and perception
- 🩸Arterial supply of central apparatus: See here.
Cerebellum
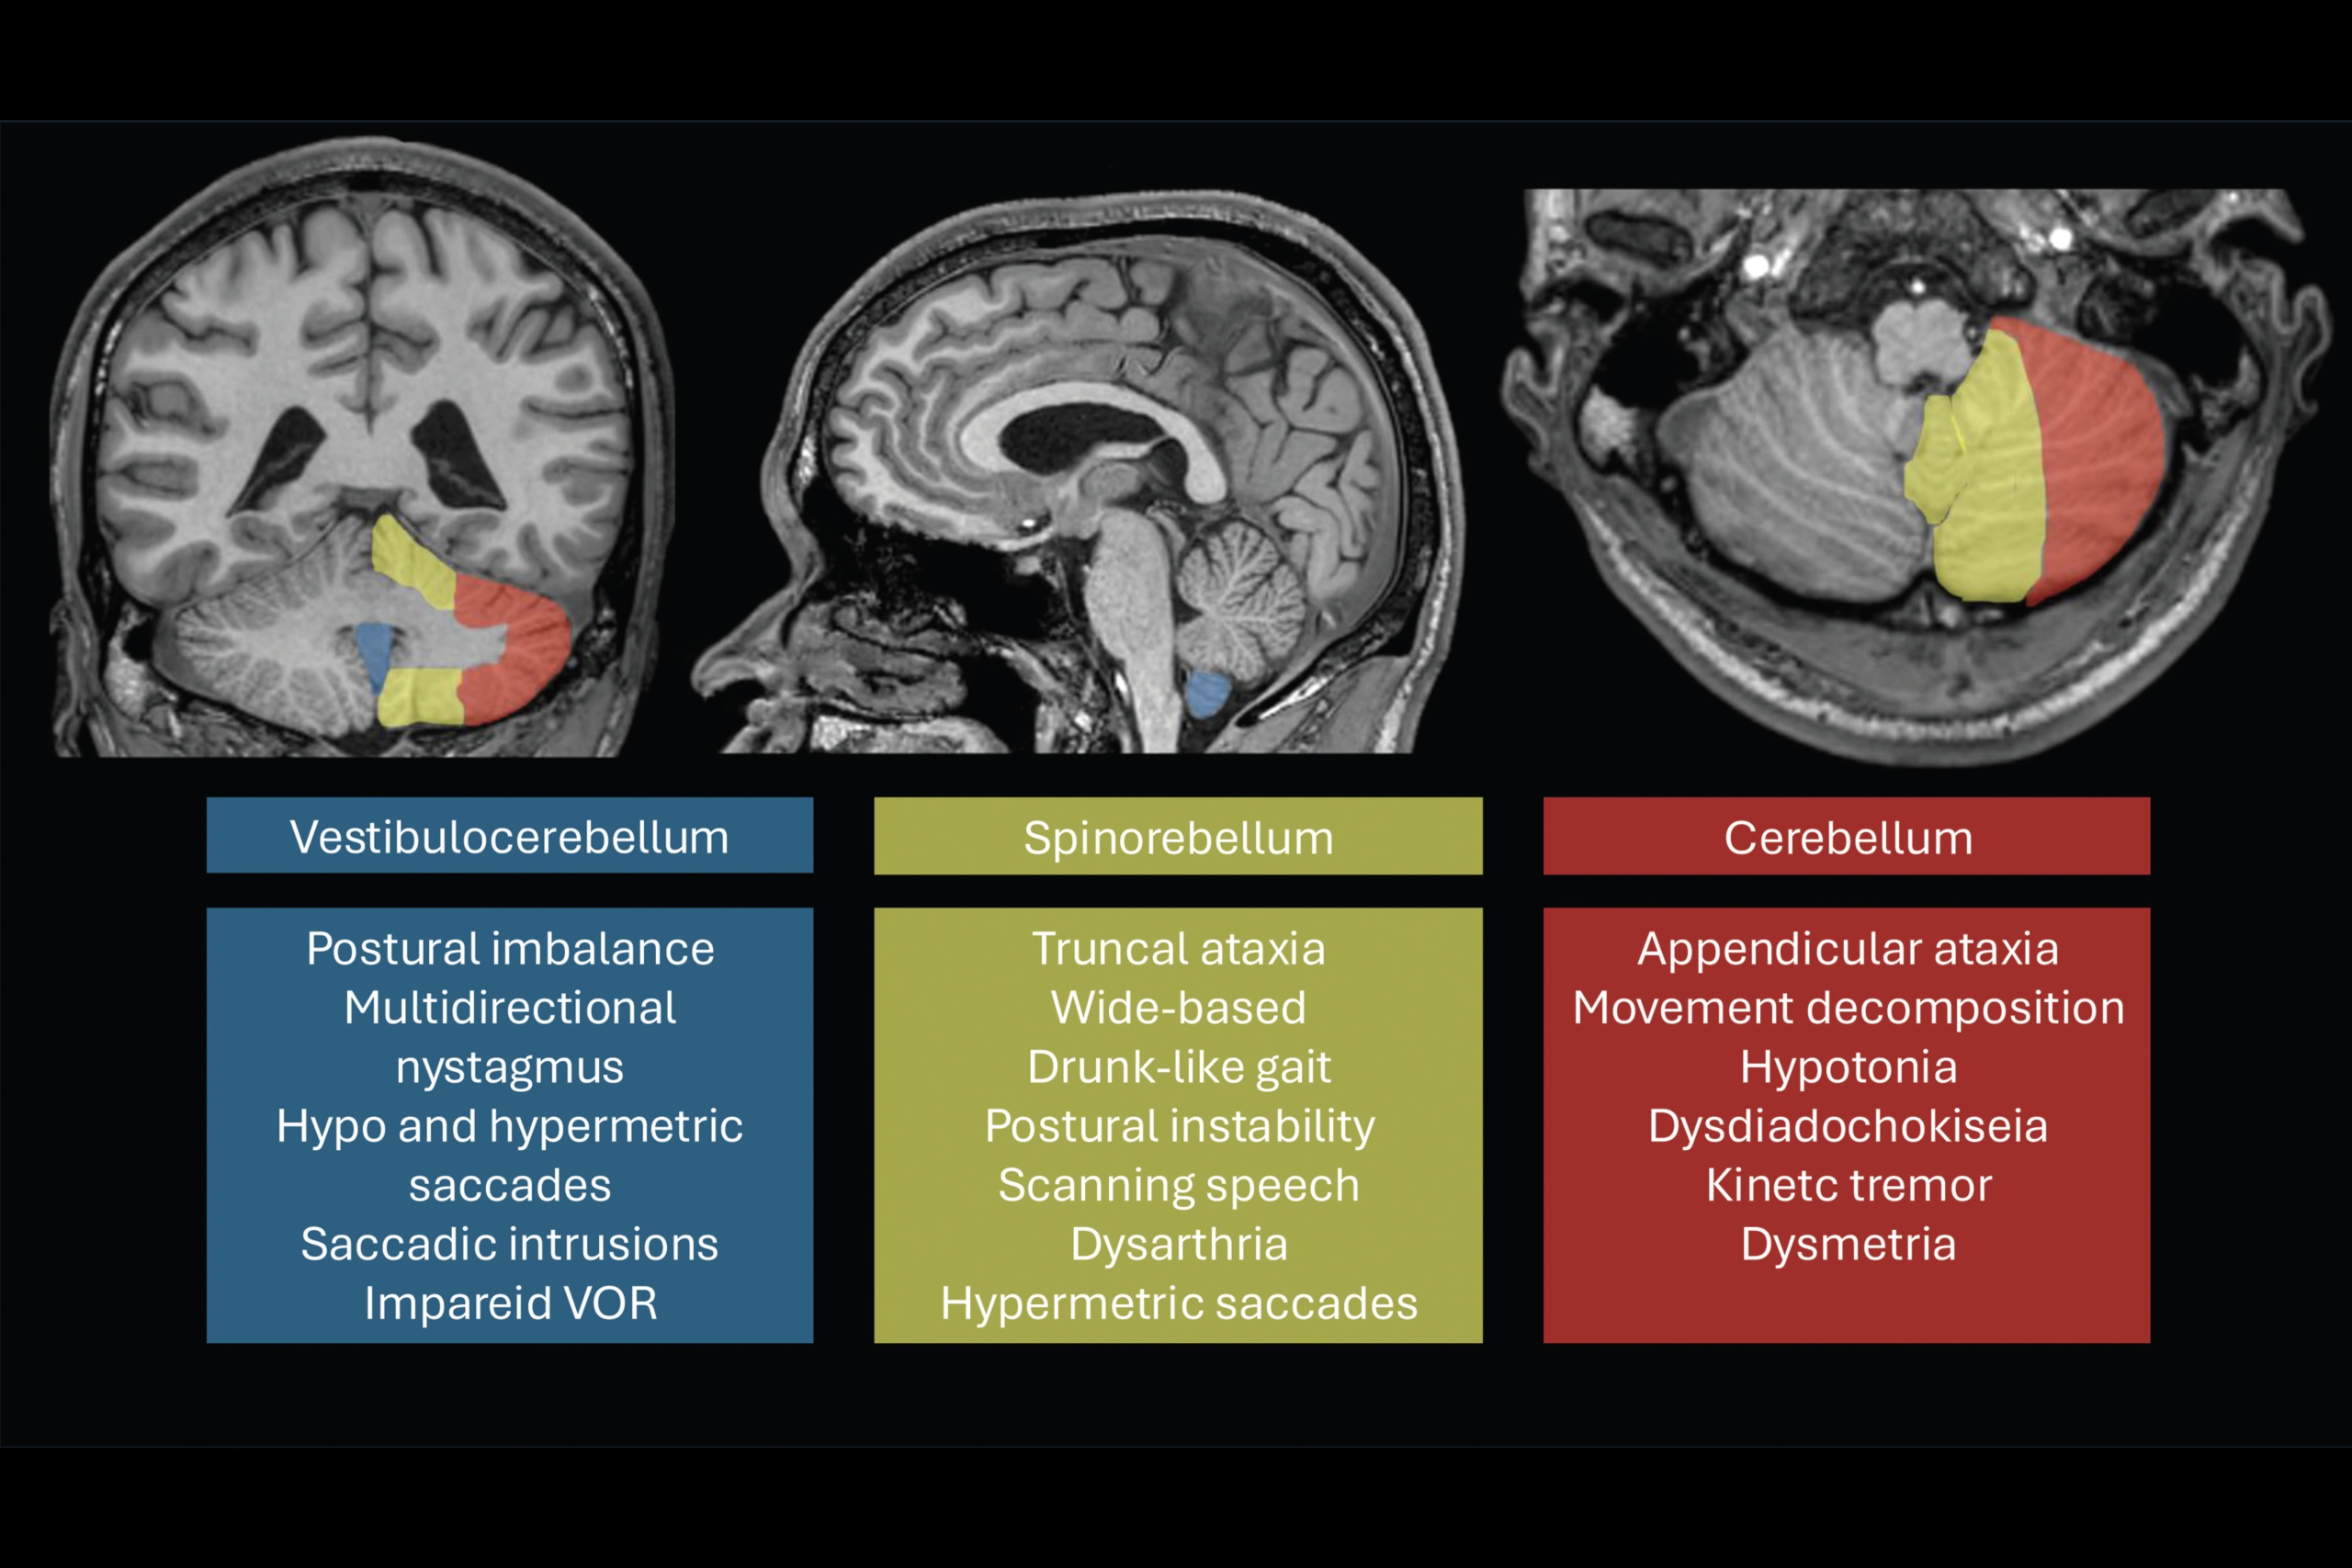
The vestibulocerebellum (flocculus, nodulus, and uvula) serves as a critical modulator, calibrating the VOR and maintaining gaze holding.
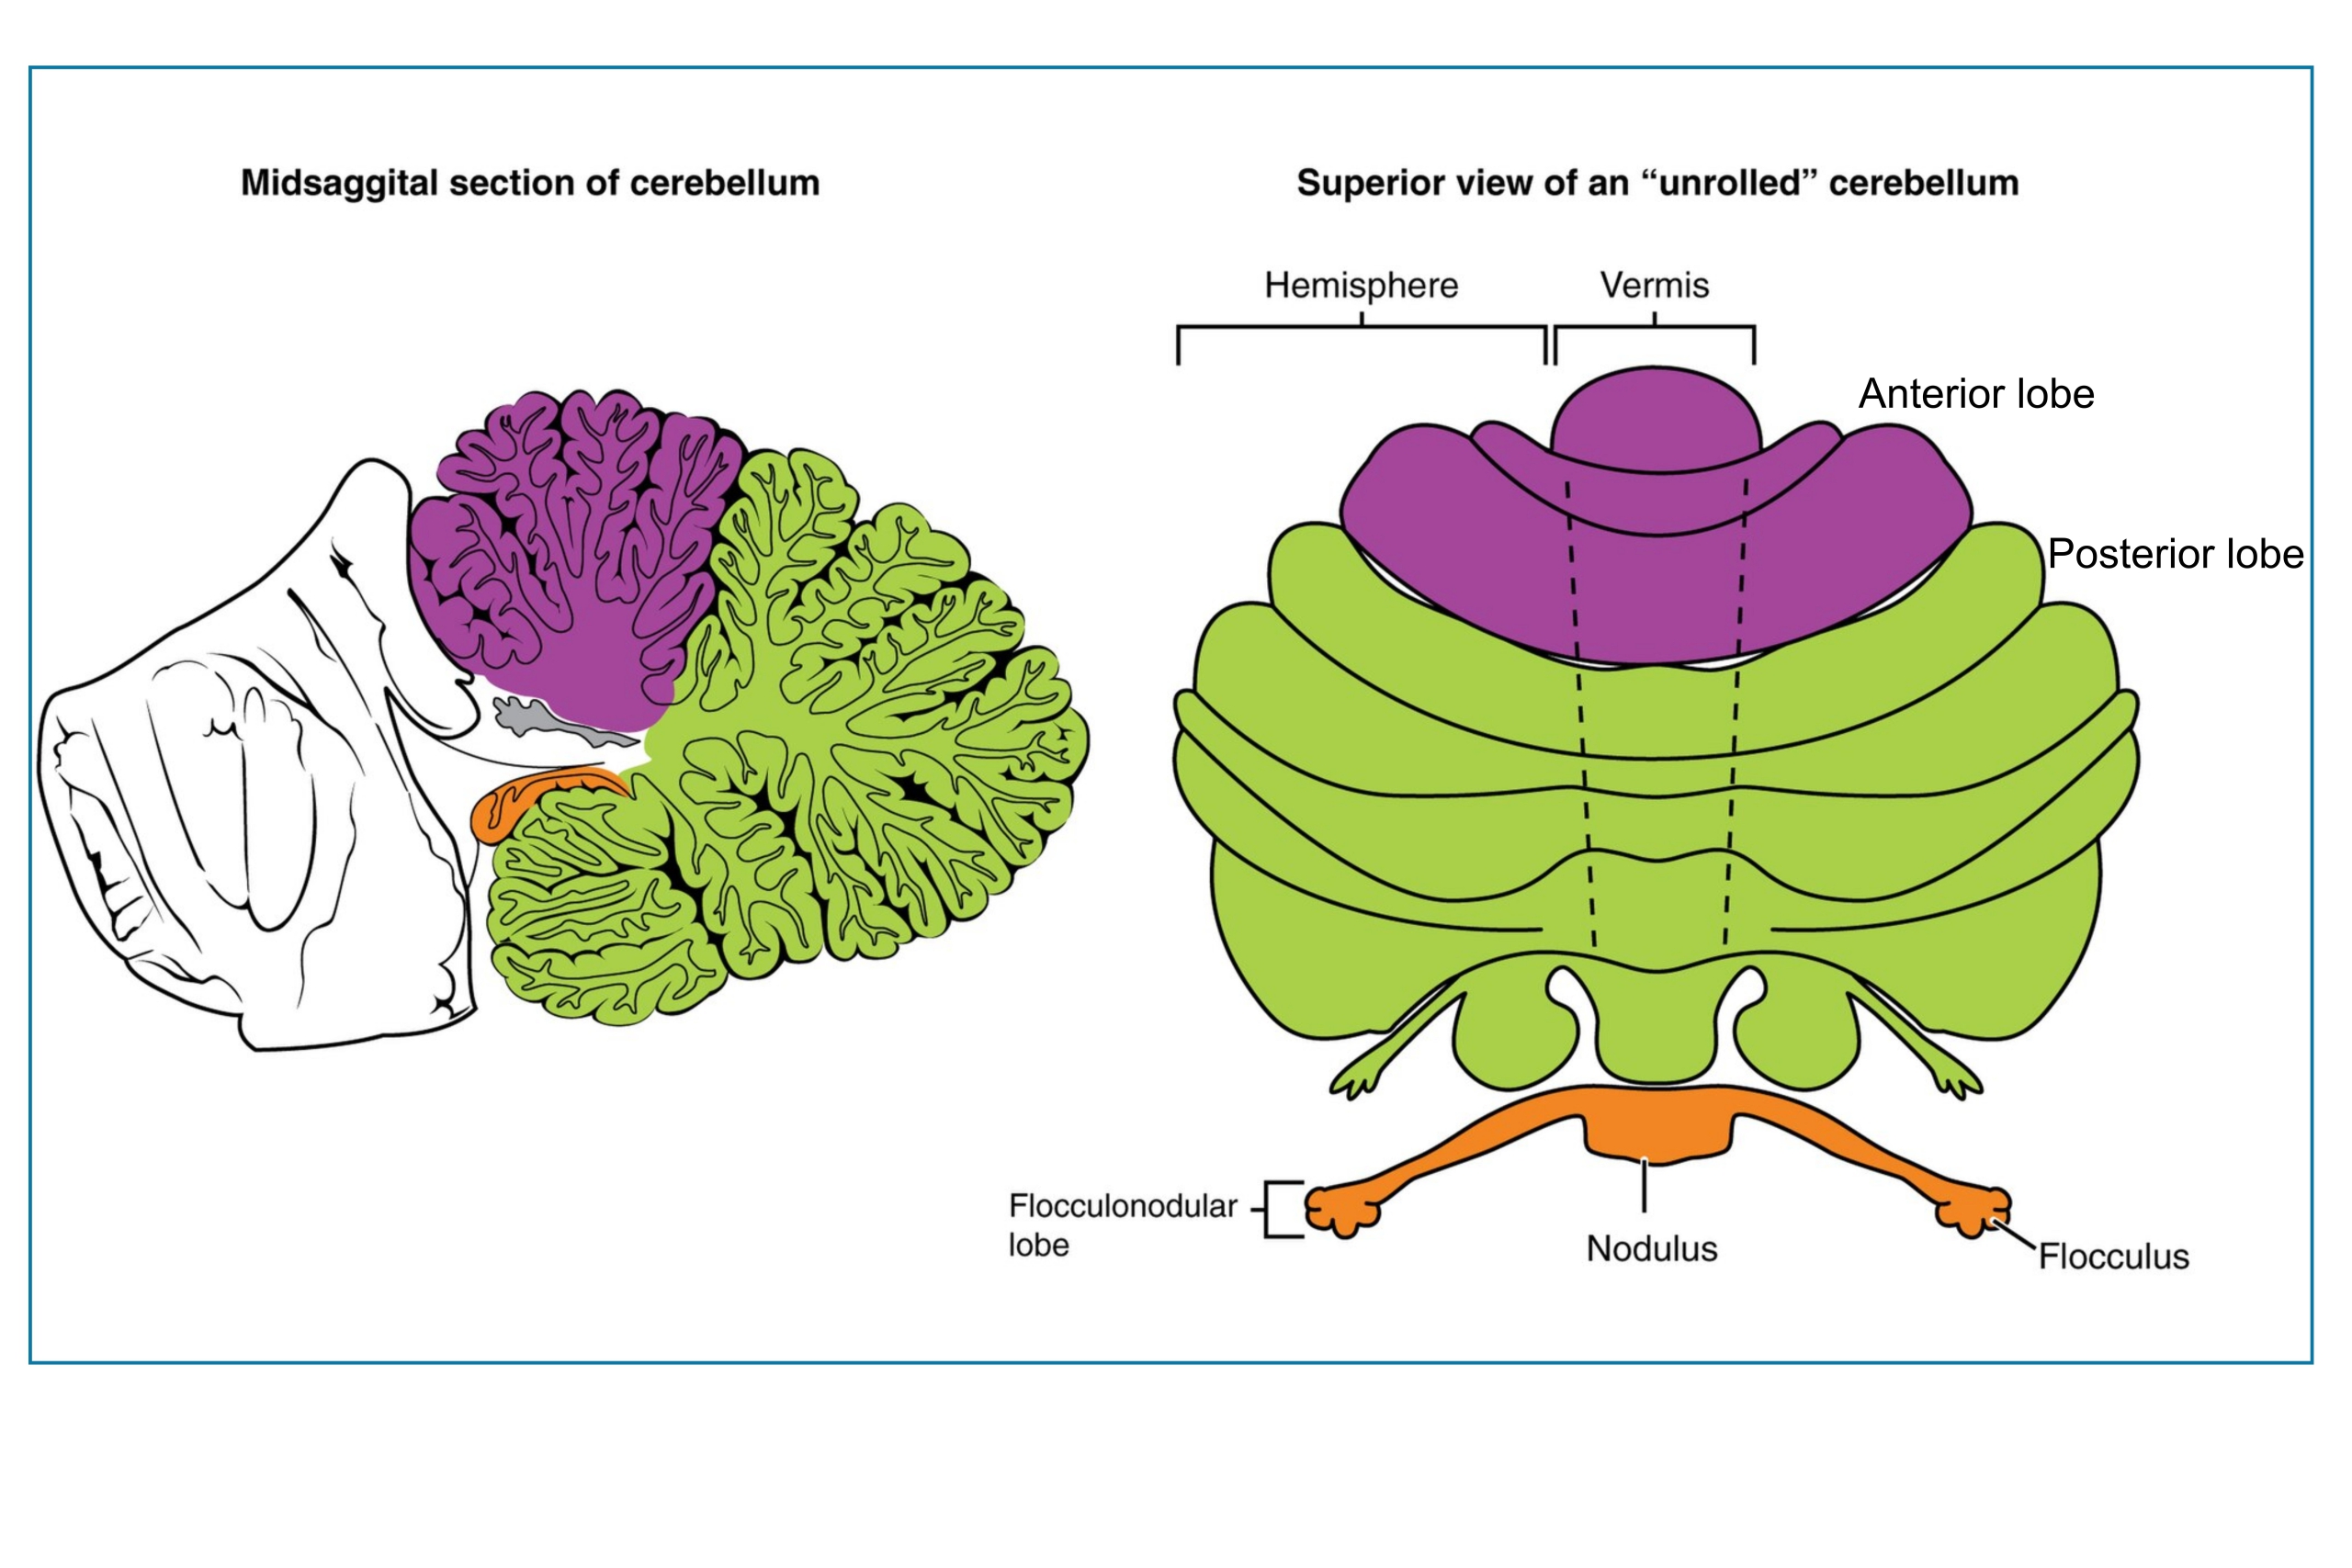
Functional Zones of Cerebellum (Click to expand)
Pathophysiology and causes
◾️Pathophysiology
- Vertigo occurs when there is a mismatch between the brain’s expected sensory input and the actual input received from the vestibular system. This mismatch creates a “tone imbalance” between the left and right vestibular circuits.
- Asymmetry: The brain interprets unequal firing rates from the left vs. right vestibular nerves as movement.
-
For example, a sudden loss of function on the left side causes the brain to perceive a rightward head rotation, resulting in nystagmus with a fast phase to the right (away from the lesion).
-
- Triggered vs. Continuous: If the imbalance is transient and provoked by a specific movement (e.g., otoconia displacing endolymph in a semicircular canal), it causes episodic vertigo. If the imbalance is sustained (e.g., due to nerve inflammation or a brainstem infarct), it causes continuous vertigo.
- Asymmetry: The brain interprets unequal firing rates from the left vs. right vestibular nerves as movement.
◾️Causes
- Because the vestibular pathways span from the inner ear to the cerebral cortex, lesions anywhere along this path can cause vertigo. However, for the emergency clinician, it is most practical to categorize etiologies into Peripheral and Central causes (noting that general medical causes are a separate third category). Common etiologies of peripheral and central causes are illustrated in the figure below (🖼️left).
- Peripheral Causes (Inner Ear and Vestibular Nerve)
- Pathology: Dysfunction of the labyrinth, vestibular ganglion, or the vestibular nerve (CN VIII) itself.
- Key Features: Nystagmus is typically horizontal-torsional, direction-fixed (Unidirectional), and suppressed by visual fixation. Patients often have severe nausea/vomiting, but normal neurological examinations (no other cranial nerve deficits, no limb ataxia, normal gait if they can walk). The common causes are shown in the figure below (🖼️right).
- Central Causes (Brainstem, Cerebellum, and Cortex)
- Pathology: Dysfunction of the vestibular nuclei, the pathways connecting them to the cerebellum, or the cerebral cortex.
- Key Features: Nystagmus may be vertical, purely torsional, or direction-changing (Bidirectional). Patients frequently have other neurological signs (the “deadly Ds”: diplopia, dysarthria, dysphagia, dysphonia, dysmetria, dysesthesia), severe truncal ataxia (unable to sit or walk independently), or a skew deviation. Unlike peripheral causes, nystagmus is often not suppressed by visual fixation.
- Peripheral Causes (Inner Ear and Vestibular Nerve)
💡Note: While distinguishing these two tiers is the primary goal of the bedside examination, a small minority of “peripheral-looking” cases are actually central lesions, such as AICA strokes that infarct both the inner ear and the brainstem, and medial PICA territory infarction that presents with isolated dizziness or vertigo, meaning dizziness or vertigo without other obvious central findings such as limb weakness or dysarthria. This is why the HINTS exam and a high index of suspicion are required.
Common Vestibular disorders
Three of the most common vestibular disorders are featured below.
◾️BPPV
- The most common cause of vertigo in all clinical settings.
- The condition occurs when otoconia (which normally reside in the utricle) are spontaneously displaced or displaced by trauma or infection into the semicircular canals.
- The most common type is displacement into the posterior canal (pc-BPPV).
- Less frequently, displacement into the horizontal (hc-BPPV) or anterior canal (ac-BPPV) can also happen.
- When patients move their head in certain positions, they experience vertigo and nystagmus, sometimes very intense, for less than 2 minutes. Between episodes, the patient may feel terrible due to a vague sense of dizziness and nausea between episodes. Of note, there’s no spontaneous nystagmus between episodes *.
- Diagnosis can be made by the Dix-Hallpike test for pc-BPPV, supine roll test for hc-BPPV, and straight head hanging for ac-BPPV.
- A “positive” Dix-Hallpike means that the patient has symptoms of dizziness and transient nystagmus lasting 20-30 seconds.
- In pc-BPPV: Nystagmus is upbeating and torsional.
- In ac-BPPV: Nystagmus is downbeating and torsional (though torsional component could be subtle).
- Supine roll test: Nystagmus is horizontal, not upbeating and torsional.
- A “positive” Dix-Hallpike means that the patient has symptoms of dizziness and transient nystagmus lasting 20-30 seconds.
◾️Vestibular neuritis
- The second most common peripheral cause of vertigo.
- This is believed to be caused by a deficit in one of the vestibular nerves. The likely cause is a virus.
- The patient develops a prolonged, continuous bout of vertigo that is intense for several days and then resolves over days, weeks, or months. The patient denies additional neurologic symptoms, but prefers to remain still with eyes closed.
- Physical examination reveals spontaneous horizontal and unidirectional nystagmus beating away from the affected ear (toward the healthy side). The nystagmus becomes more pronounced when looking toward the healthy side and resolves when looking toward the affected side (Alexander’s law).
- HINTS Plus test: The head impulse test is abnormal (presence of a corrective saccade) when the head is rapidly turned toward the affected side. Vertical skew deviation is absent.
- Cranial nerve, cerebellar, and gait testing are normal.
◾️Posterior Circulation Stroke (PCS)
- Cerebellar/brainstem stroke is the most feared cause of vertigo. More on PCS, below.
- An older individual with cerebrovascular disease risk factors presents with abrupt onset and persistent dizziness and gait instability.
- Examination
- Coordination and balance
- Truncal ataxia (often assessed using a grading scale, e.g., Grade 0-3).
- 💡Severe truncal ataxia (Grade 3) is a highly specific “red flag” that strongly differentiates central strokes from peripheral vestibular neuritis.
- 👣Gait ataxia
- Is a very common and sensitive sign of PCS (especially in cerebellar involvement).
- Truncal ataxia (often assessed using a grading scale, e.g., Grade 0-3).
- Other findings: May be present depending on location of stroke *.
- Focal weakness & parasthesia
- Cranial nerve findings
- Limb ataxia.
- Dangerous D’s (referring to the classic symptoms seen in PCS) *
- Diplopia.
- Dysphagia
- Dysarthria.
- Dysmetria (limb or truncal)
- Dysphonia.
- Dystaxia (i.e., ataxia and loss of coordination).
- Hiccups *.
- New-onset headache, neck pain (esp. in the setting of recent trauma, may suggest vertebral artery dissection resulting in PCS).
- ⚠️However, some patients may present without these features (isolated vertigo); as such, the condition may resemble vestibular neuritis. See Infarction in the territory of the medial PICA (here).
- 👀Nystagmus
- ⚠️Only 50% of patients will have nystagmus, which may be horizontal, torsional, vertical, or gaze-evoked (beats to the right on rightward gaze and to the left on leftward gaze) *.
- This is precisely why the HINTS exam (which requires the presence of spontaneous nystagmus at rest to be performed) cannot be applied to all patients with acute vestibular syndrome.
- Therefore, in the absence of spontaneous nystagmus at rest in a patient with ongoing isolated vertigo, assessment for gait is crucial (see the overview of approach to dizziness in ED, here).
- ⚠️Only 50% of patients will have nystagmus, which may be horizontal, torsional, vertical, or gaze-evoked (beats to the right on rightward gaze and to the left on leftward gaze) *.
- HINT Exam. See below.
- Coordination and balance
- ⚠️Patients with cerebellar stroke may develop edema causing acute hydrocephalus or brainstem compression that leads to increased disability or death.
Differential Diagnosis
- 📊The common features of other causes of vertigo are summarized in the following table (click to expand).
Differential Diagnosis of Acute Vertigo: Peripheral vs. Central (Click to Expand)
References: 1. Edlow JA, et al. GRACE-3. Acad Emerg Med. 2023;30(5):442-486. 2. Bhattacharyya N, et al. BPPV (Update). Otolaryngol Head Neck Surg. 2017;156(3_suppl):S1-S47. 3. Fife TD, et al. Therapies for BPPV. Neurology. 2008;70(22):2067-2074. 4. Kattah JC, et al. HINTS to diagnose stroke. Stroke. 2009;40(11):3504-3510. 5. von Babo M, et al. Spontaneous dissections. Stroke. 2013;44:1537-1542. 6. Subramanian G, et al. Risk factors for posterior circulation stroke. Can J Neurol Sci. 2009. 7. Hedna VS, et al. Posterior circulation stroke risk factors. Stroke Res Treat. 2012. 8. Brandt T, Strupp M, Dieterich M. Vestibular paroxysmia: a treatable neurovascular cross-compression syndrome. J Neurol. 2016;263(Suppl 1):S90-S97. 9. Minor LB, et al. Sound- and/or pressure-induced vertigo due to bone dehiscence of the superior semicircular canal. Arch Otolaryngol Head Neck Surg. 1998;124(3):249-258.
📊 Vascular Risk Factors: Traditional cardiovascular risk factors carry different weights in the posterior circulation. Diabetes Mellitus (DM) is associated with an increased risk of posterior circulation stroke (OR ~1.14–1.49), while Atrial Fibrillation (AF) is paradoxically associated with a lower risk of posterior vs. anterior circulation stroke (OR ~0.83). However, because AF remains a critical cause of cardioembolism, a routine 12-lead ECG should be obtained in all patients with suspected TIA or central vertigo to rule out arrhythmias.
Dizziness Characterization
- “Dizzy” is a famously vague word. It can mean wildly different things to different people, and that’s exactly why pinning down a diagnosis can be so tricky.
- We’re often taught to start with: “What do you mean by dizzy?” But the literature throws a wrench in that approach: nearly half of ED patients will change their description of the dizziness within the very same visit!
- In other words, the words they use aren’t a reliable anchor for your clinical reasoning. Rather than hanging your hat on the patient’s choice of words, dig into the same details you’d use for any other tricky ED complaint. Ask about timing, triggers, how long each episode lasts, and any associated features.
This structured approach, much like the way you’d tease out chest pain or abdominal pain, will help you narrow the differential and guide your next steps far more reliably than the descriptor alone.
⏳Timing
- When did symptoms begin? Are they still present now?
- How long does the intense episode last?
- Have there been prior episodes?
- In patients with conditions like BPPV, the vertigo lasts a few minutes, but in between attacks the patients may still feel terrible due to nausea & vomiting. So try to sort out how long the dizziness lasts. It might be helpful to ask what you were doing when the symptoms started and whether the intensity of symptoms has changed since then.
⚡️Triggers
- What was the patient doing immediately before onset?
- Do symptoms begin with rolling over in bed, lying down, bending forward, sitting up, standing, or another position change?
📈📉Episode Duration/Between-Episode Symptoms
- Is the dizziness there all the time, or does it come in waves?
- Does the patient stay symptomatic even while holding completely still, or do they return to normal between episodes? And if they don’t fully bounce back, what’s left over? Do they feel vaguely unwell, nauseated, or unsteady?
- A crucial distinction: Separate the duration of the actual spinning from the longer tail of residual symptoms.
- A patient might describe “dizziness all day,” when in reality they had three brief spinning attacks and felt mildly nauseated in between. Catching that nuance can steer you toward the right diagnosis.
🚨Associated features
- Ask about vomiting, trouble walking, hearing changes, headache, neck pain, and any focal neurologic symptoms. And don’t stop at the neuro exam; also screen for non-neurologic symptoms that might point to a systemic cause (e.g., chest pain, palpitations, fever, melena).
- About half of acutely dizzy patients have an underlying medical cause. Consider asking for non-neurological symptoms that may suggest systemic causes. (Note: GRACE-3 explicitly excludes these from the strict AVS definition, but they must be ruled out in the ED)
- Vital sign derangements
- Cardiovascular: Dysrhythmia, hypovolemia from any cause, hypoperfusion, causing presyncope or dizziness.
- Severe Anemia / GI Bleed: Causing cerebral hypoperfusion and unsteadiness.
- Toxic: Carbon monoxide (CO), benzodiazepines, alcohol, anticonvulsants, lithium, causing central vestibular dysfunction.
- Hypoglycemia: Can cause acute confusion, dizziness, and autonomic symptoms.
- Infectious: Urinary tract infection, sepsis.
- Pay attention to:
- Comorbidities
- Cardiovascular risk factors
- Medications and substance use
- Trauma, especially for signs of basilar skull fracture, tympanic membrane rupture, or vertebral artery dissection.
🧐Why does this matter?
- These associated features are often the “tie-breakers” that push you toward one diagnosis and away from another, or flag a dangerous systemic problem hiding behind the dizziness
Approach to Diagnosis and Management
Overview
A comprehensive history and neuroexam can do most of the heavy lifting for vertigo risk stratification, but only if we remain vigilant for subtle clues. A structured ED screening neuro exam is often more important than any specific vestibular maneuvers.
The following illustration shows an overall approach to dizziness. To optimize the diagnostic utility of the HINTS examination and reduce stroke misdiagnosis, clinicians should first screen for central features before applying HINTS and ensure it is only performed for patients with nystagmus at rest *.
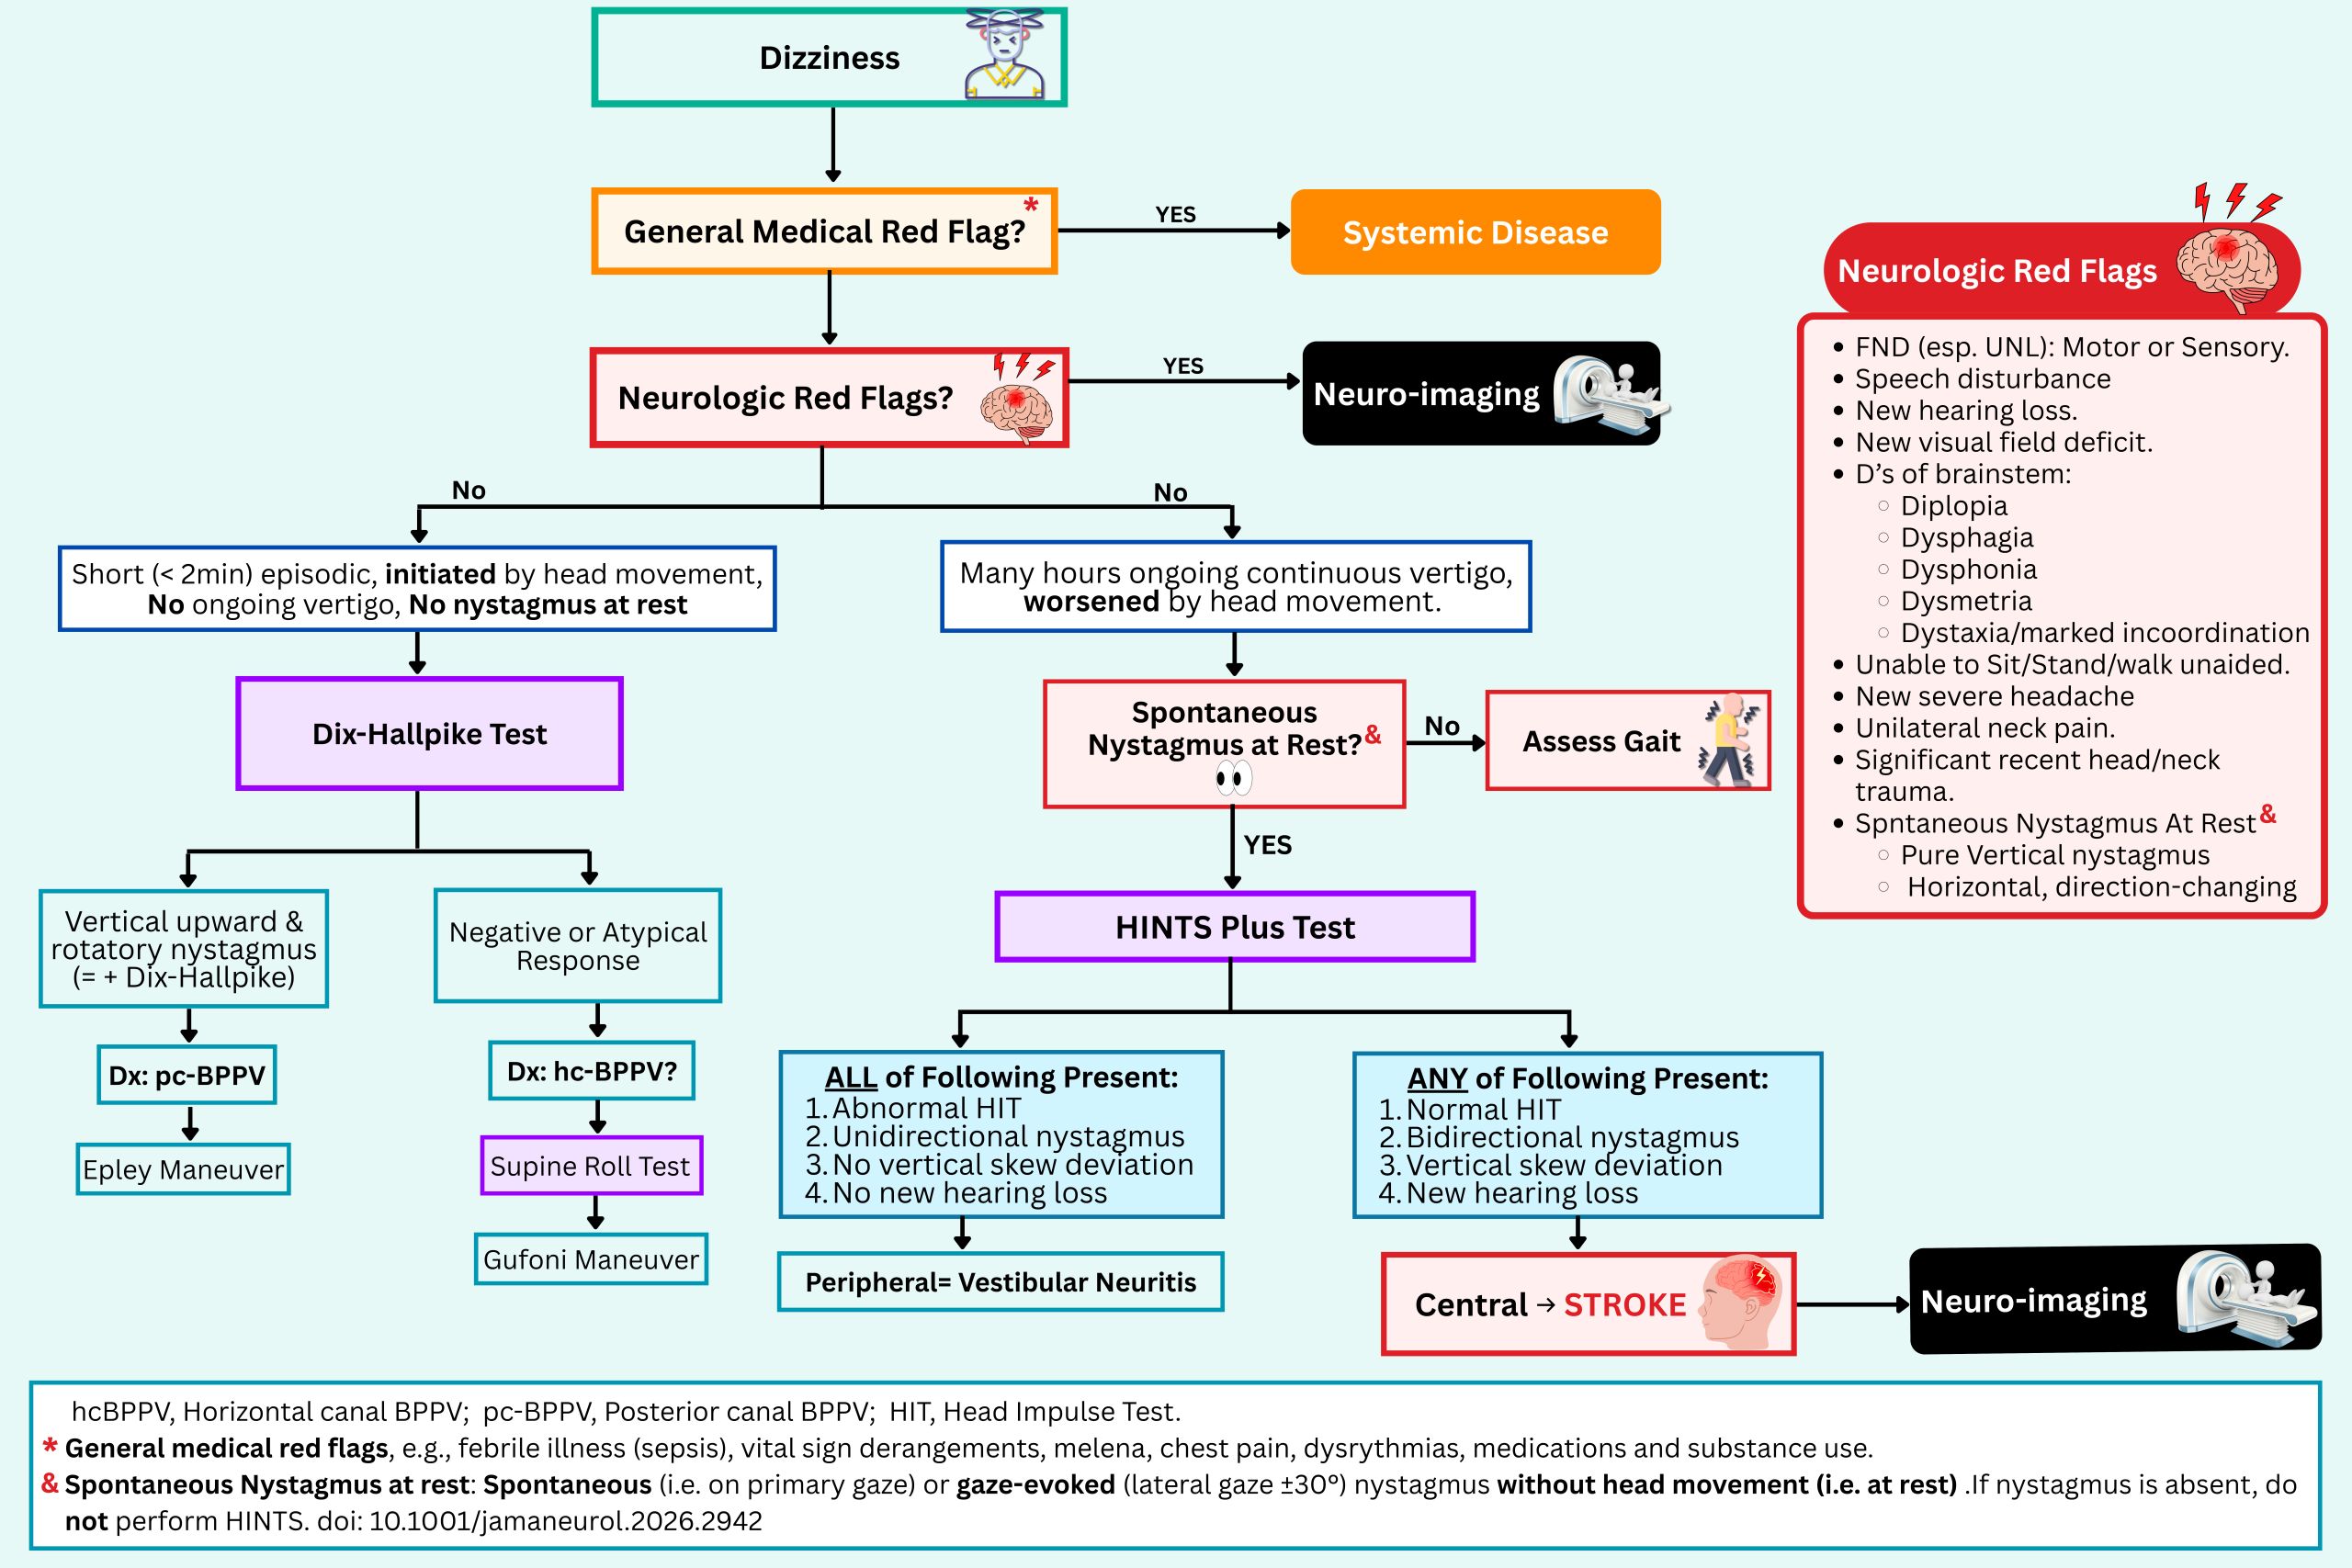
STEP 1: Screen for Central & Systemic Red Flags of Vertigo
Before you even reach for a specific vestibular maneuver, run a structured screening neurologic exam. In many cases, this basic step. Vital signs, a focused neurologic check, and a search for focal deficits do more heavy lifting than any fancy vestibular test.
- Perform a full neurological examination, including gait testing, to ascertain if the patient is experiencing an acute ischemic stroke.
- A targeted posterior circulation examination should be performed as part of a complete neurologic examination.
🚩Red Flags for a Central Cause
- New hearing loss or visual field deficit.
- Patients may not recognize or volunteer these symptoms, so ask and assess deliberately.
- New focal (esp unilateral) weakness, sensory change, speech disturbance, and worrisome D’s of brainstem findings (diplopia, dysphagia, dysphonia, dysmetria, or dystaxia/marked incoordination), and hiccups *.
- Dysmetria on finger-to-nose test or heel-to-shin test
- New severe headache, unilateral neck pain, or significant recent head/neck trauma.
- These may raise concern for posterior circulation stroke or vertebral artery dissection.
- Spontaneous vertical nystagmus at rest or direction-changing nystagmus at rest (ie., with the head held still).
- New inability to sit upright, stand, or walk without assistance

Physical exam
Coordination and gait
◾️Background
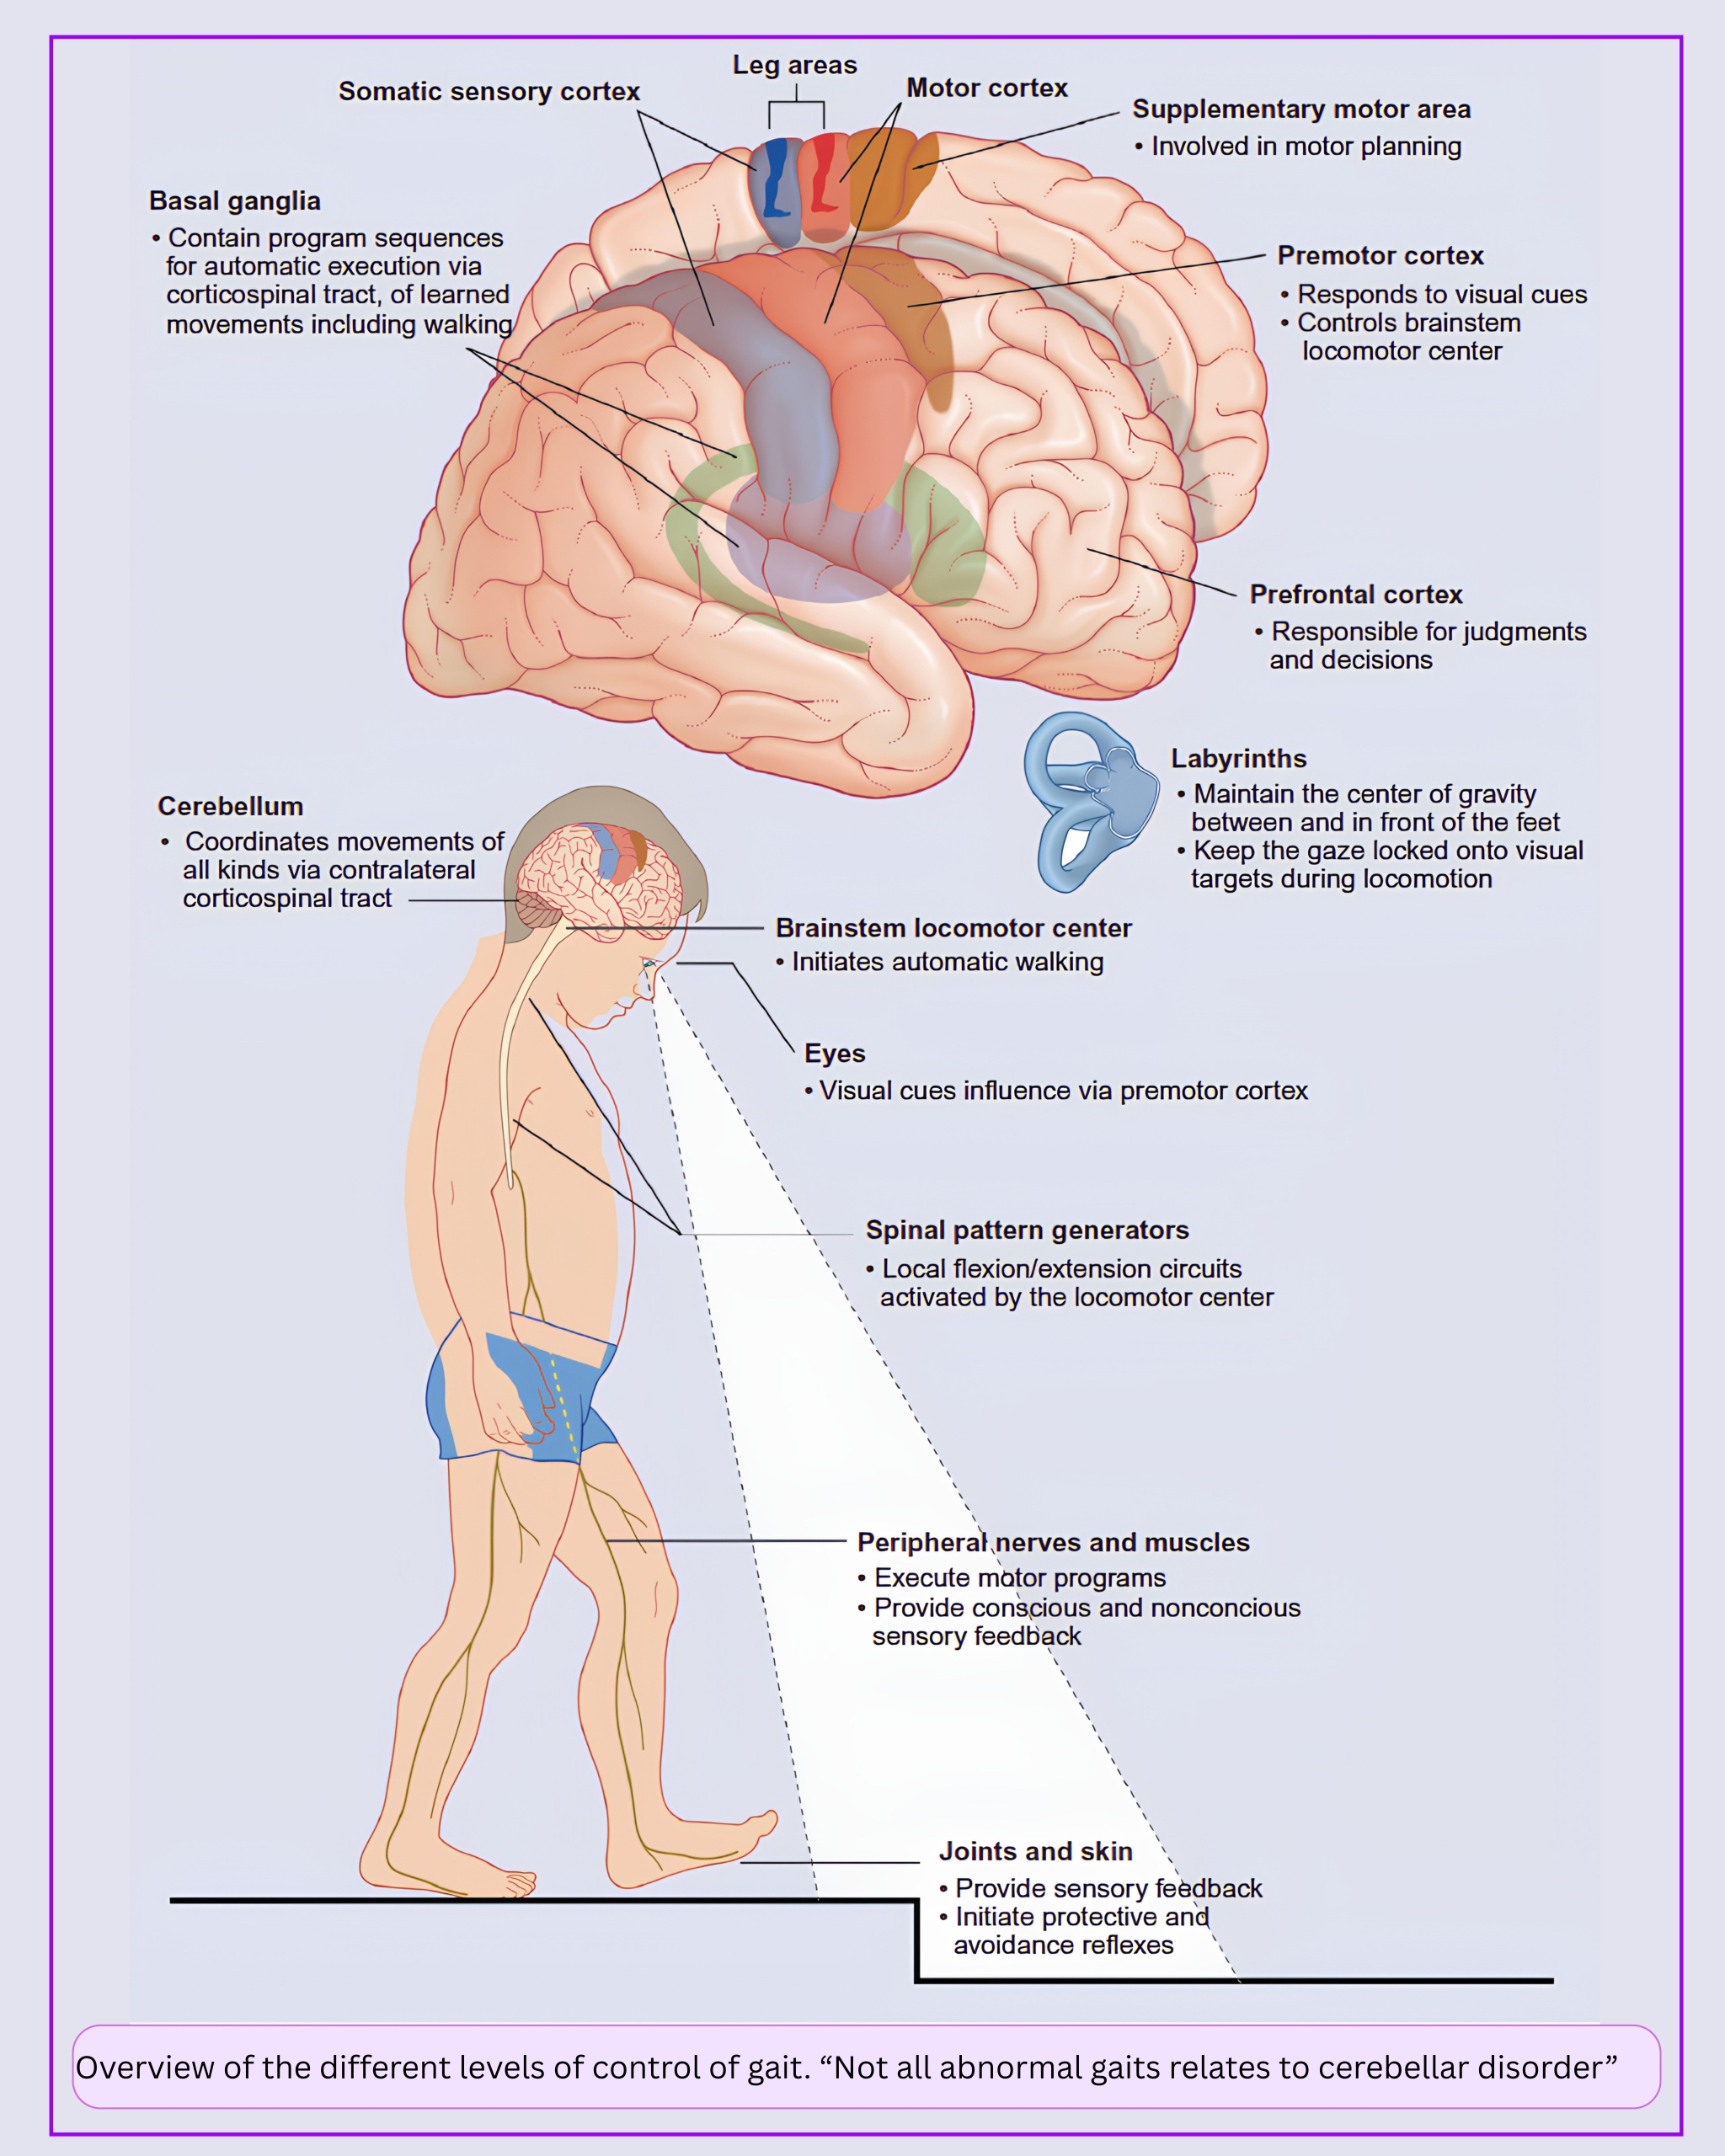
- Contrary to popular belief, coordination & gait disturbance doesn’t necessarily indicate a cerebellar lesion. Instead, it may reflect a pathology involving the proprioception, vision, basal ganglia, or motor pathways (🖼️ Figure below).
- Cerebellar lesions can cause different kinds of dyscoordination depending on their location (see above). Therefore, lesions in a cerebellar hemisphere will lead to dyscoordination (dysmetria) of the same side.
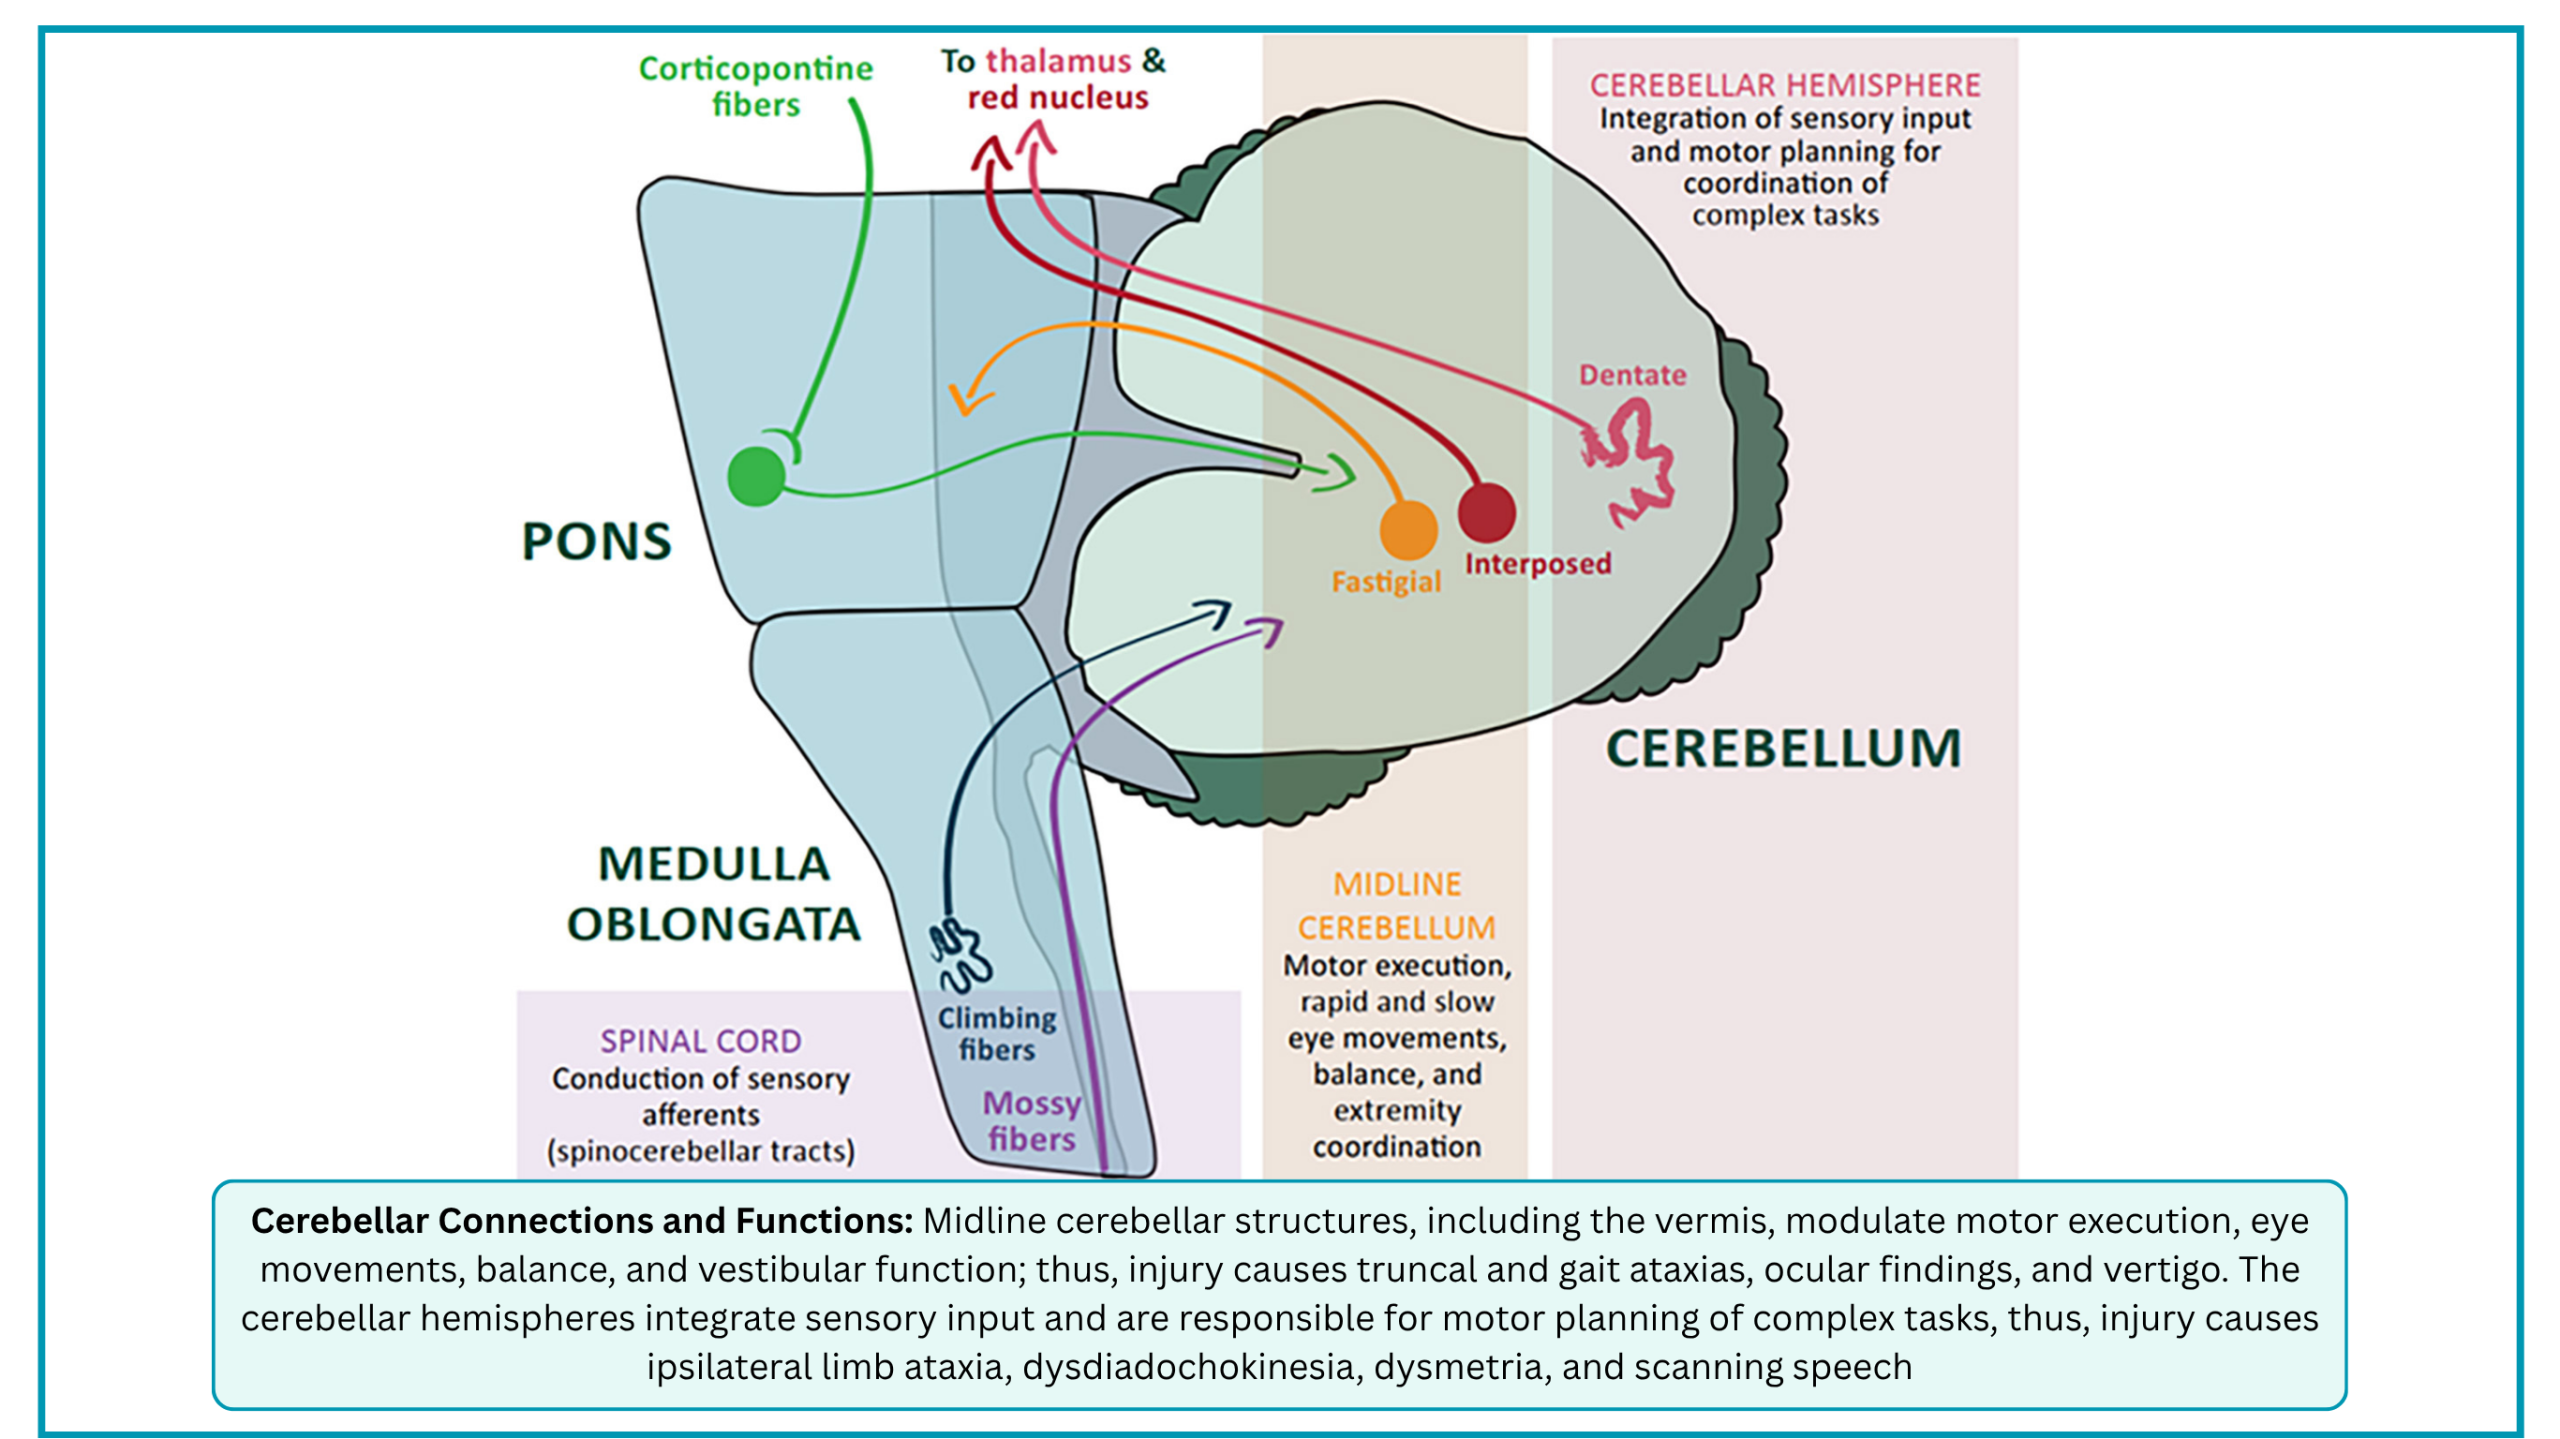
- One important distinction is between truncal ataxia and appendicular ataxia.
- Appendicular ataxia affects movements of the extremities and is usually caused by lesions of the cerebellar hemispheres and associated pathways.
- Truncal ataxia affects the proximal musculature, especially that involved in gait stability, and is caused by midline damage to the cerebellar vermis and associated pathways.
- It is an instability of the trunk and is often seen during sitting.
- Truncal ataxic gait is a wide-based “drunken sailor” gait characterized by uncertain starts and stops, lateral deviations, and unequal steps.
- It is most visible when shifting position or walking heel-to-toe.
◾️Evaluation
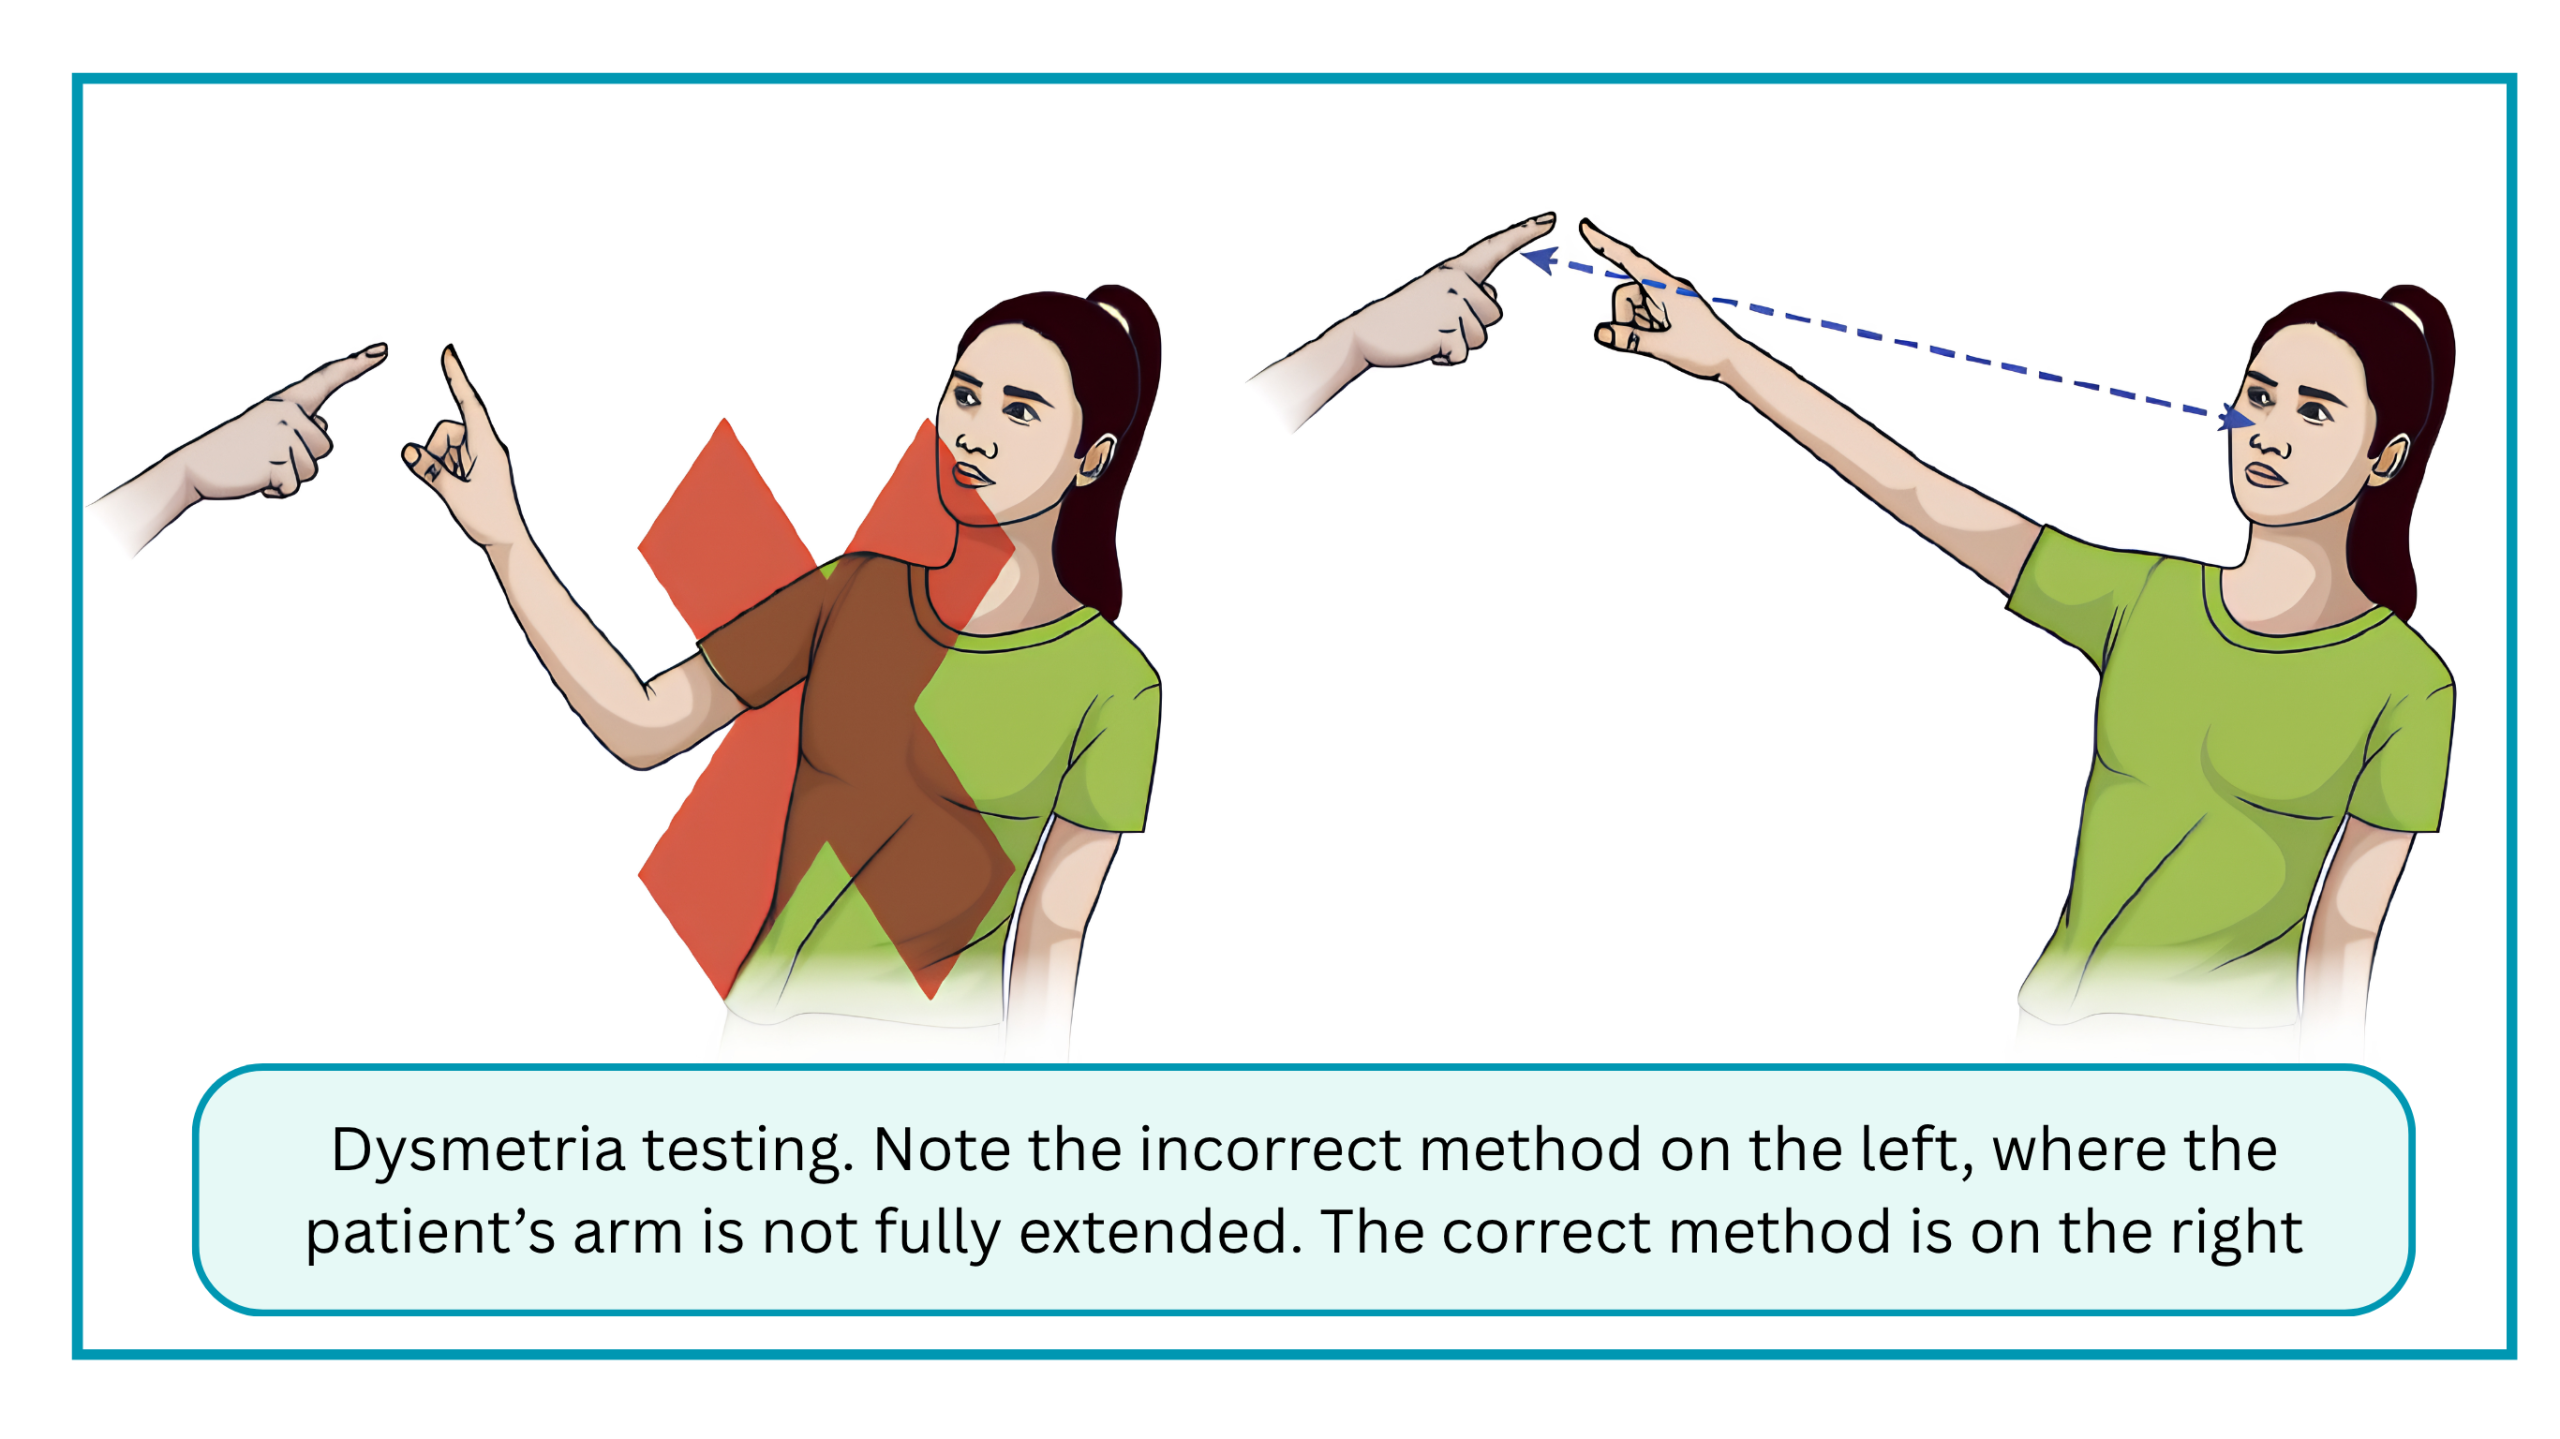
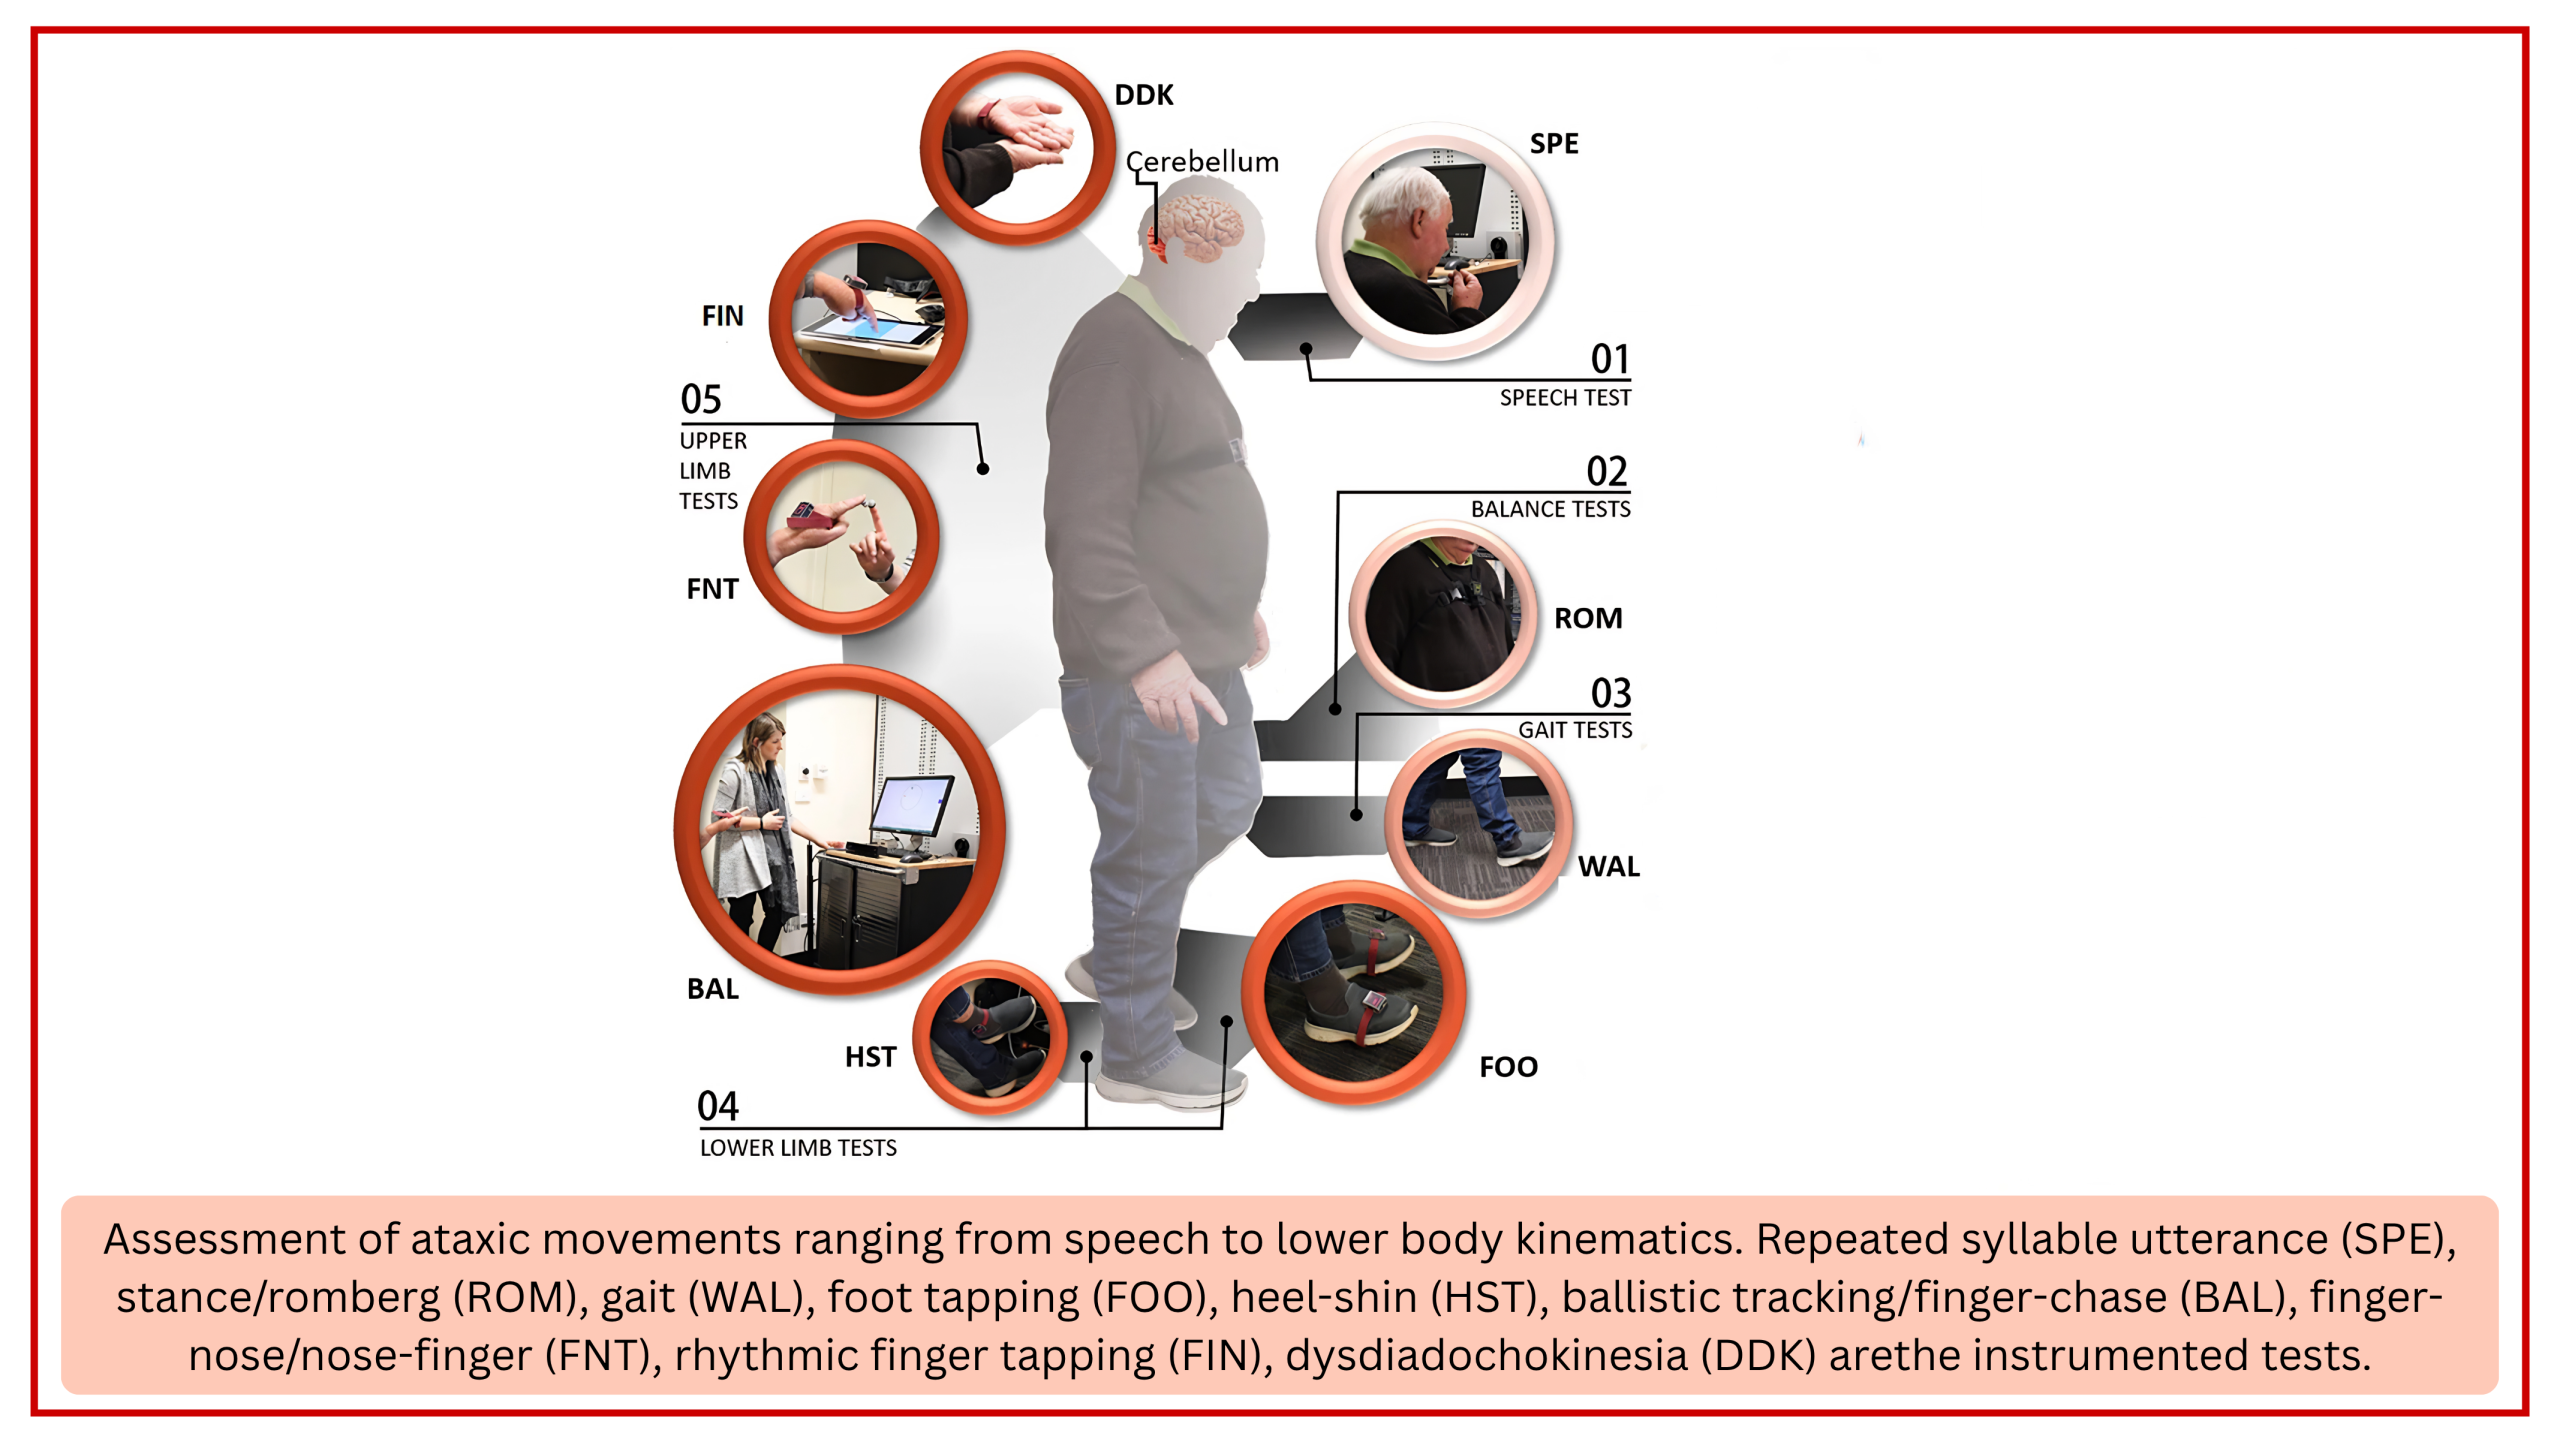
- Appendicular Coordination 🎥
- The two standard tests for ataxia of appendicular coordination are:
- Finger-nose-finger test (🖼️Right figure below).
- Heel-to-shin test
- Other tests, including rapid alternating movements (dysdiadochokinesia), are shown in the figure on the left below 🖼️.
- The two standard tests for ataxia of appendicular coordination are:
- Gait 🎥
- Formal Gait Testing: Assess both truncal stability (sitting up in the stretcher) and walking. Gait testing is a crucial part of risk stratification. Ask the patient to sit up independently, then stand and walk unassisted (if safe), observing their ability to walk in a straight line and turn.
- 📍Peripheral vestibular disorders can also cause imbalance; therefore, interpret gait in clinical context.
- Gait disturbance is not specific for a central cause (🖼️Right figure below). The typical exam findings in common gait disorders are shown in the figure right below 🖼️.
- In one study, 50% of both peripheral and central causes for dizziness were unable to stand unassisted *.
- A commonly used bedside approach is the graded gait and truncal instability (GTI) rating *.
- In this grading system, grade 1 indicates mild to moderate imbalance while walking independently, grade 2 indicates inability to walk without support, and grade 3 indicates falling in the upright posture.
- 💡Clinical Significance: In occasional stroke patients, abnormal gait may be the only finding. It is also critical for determining safe discharge for any patient.
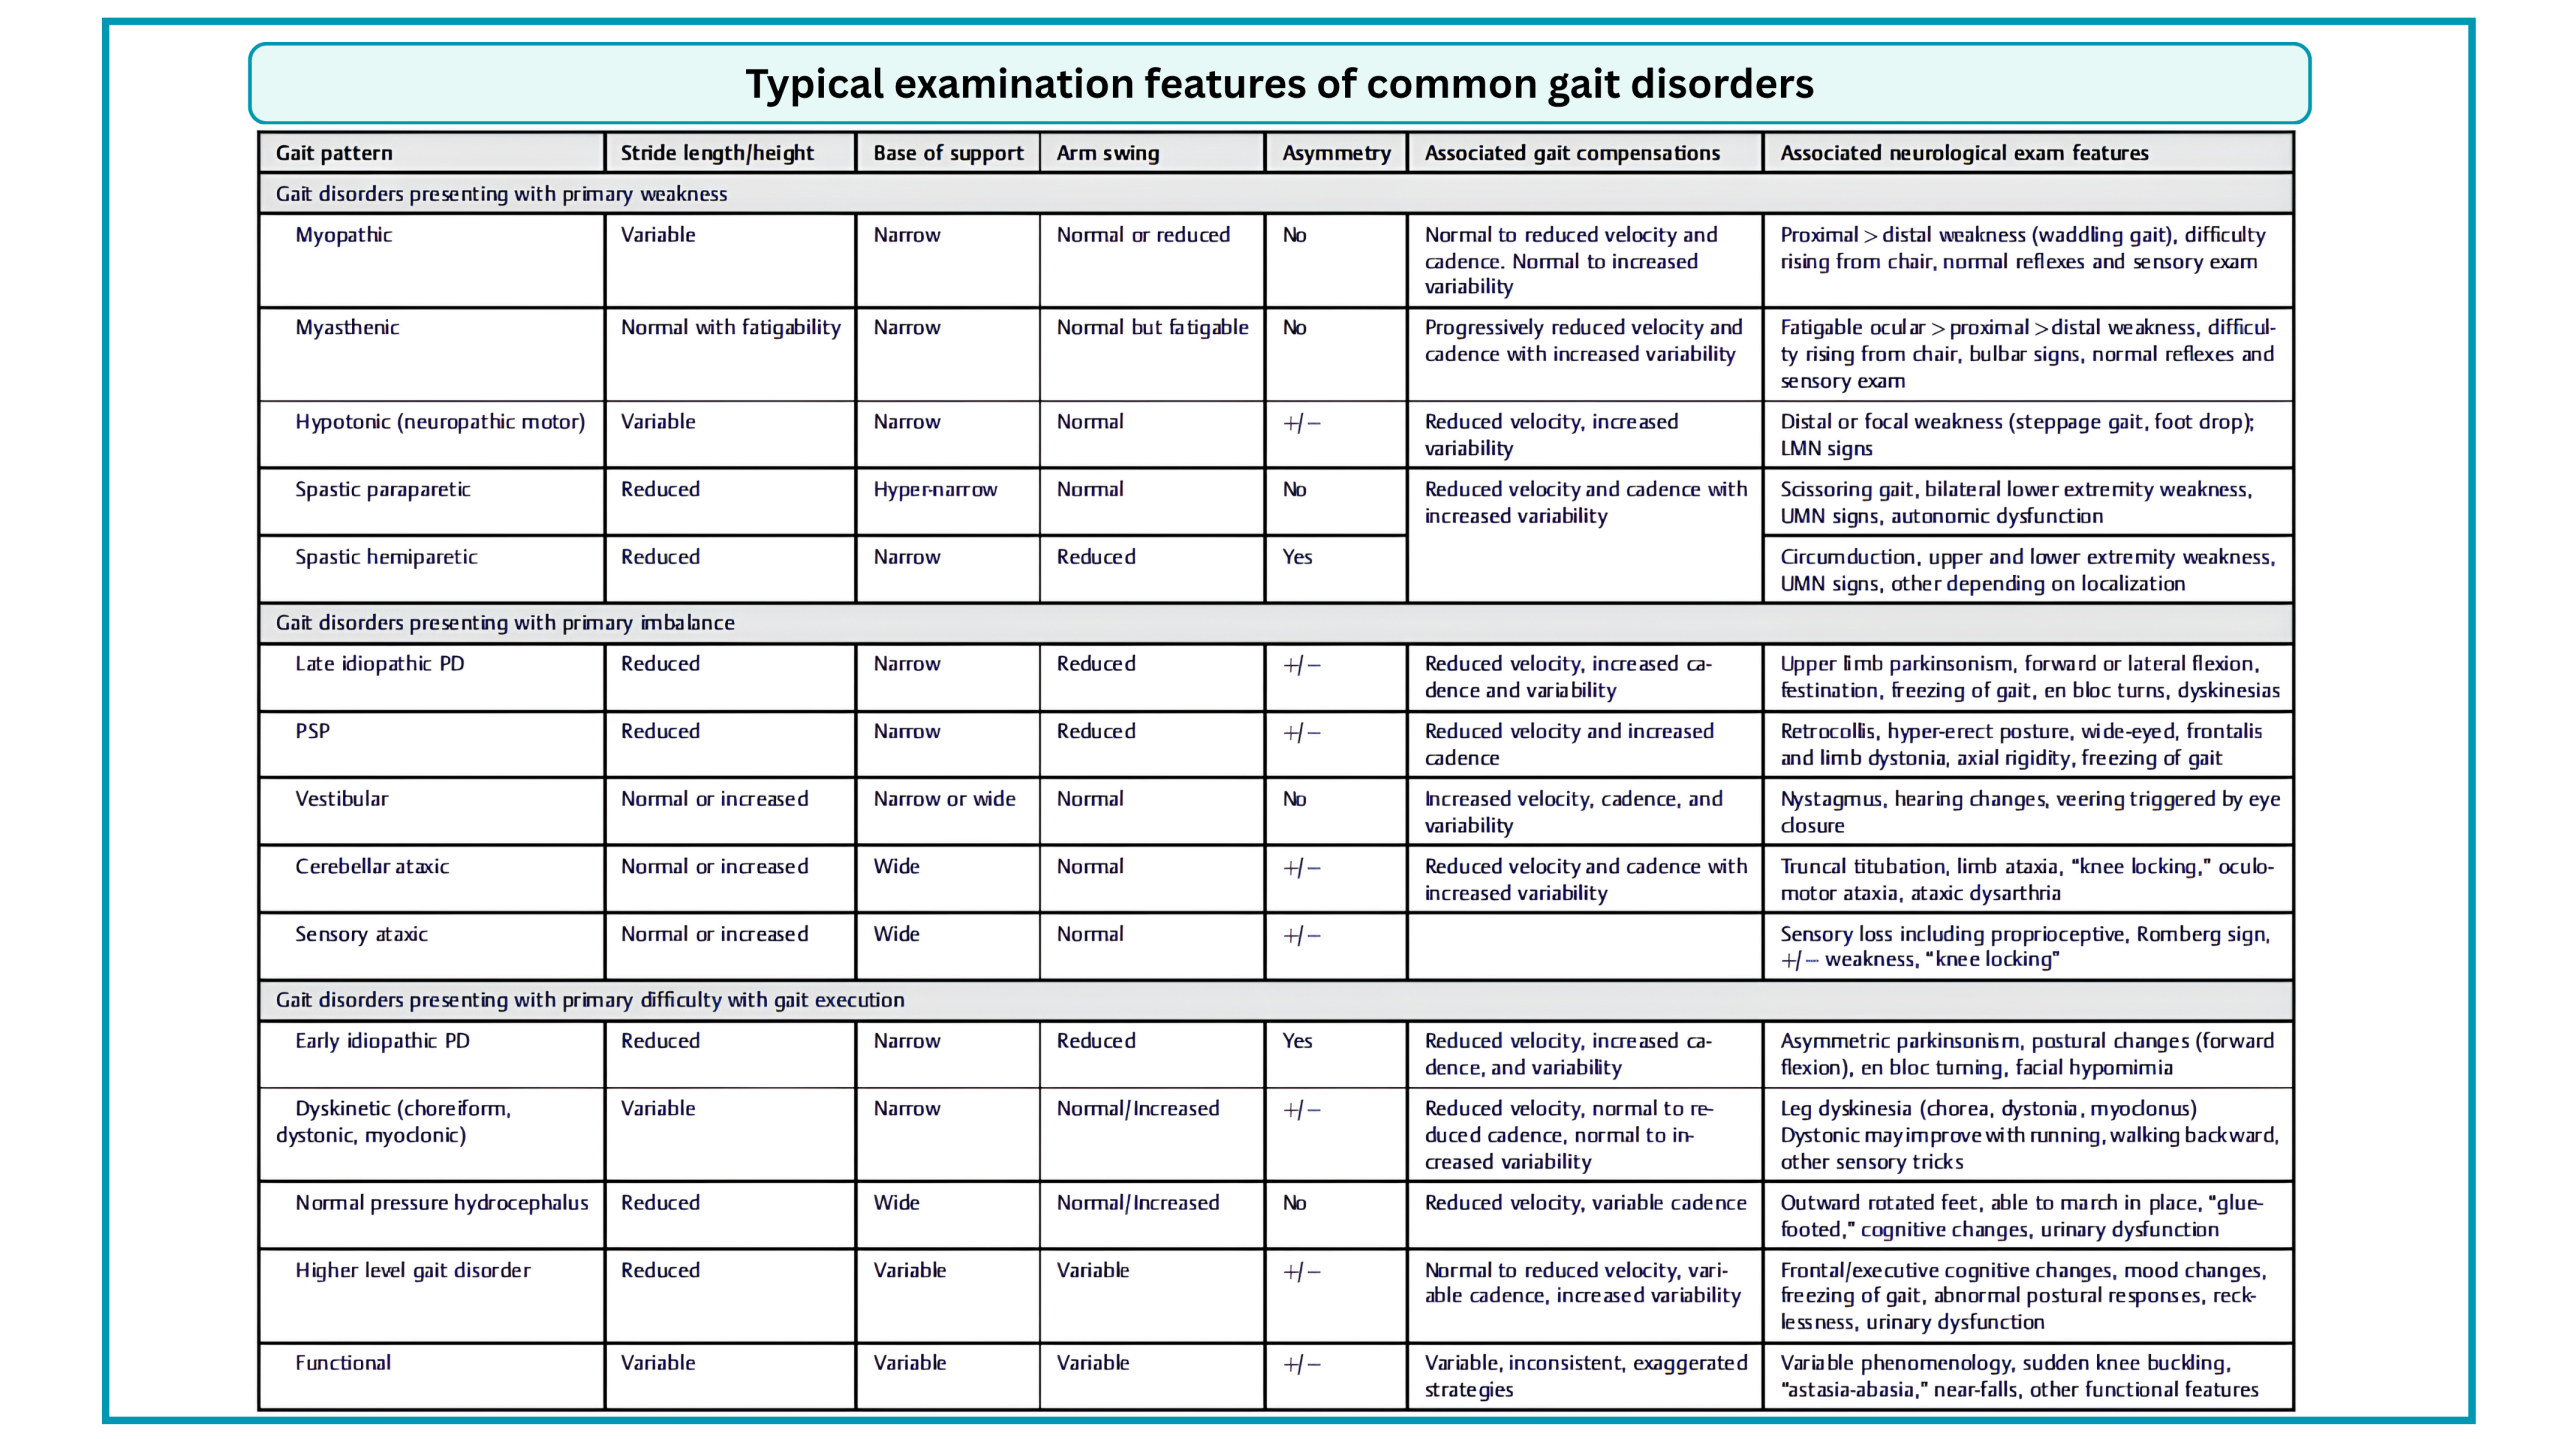
◾️Brainstem Testing
- Perform a thorough cranial nerve examination. More on this here.
◾️Visual Fields (🎥)
- Test visual fields (the terminal branches of the basilar artery supply the posterior cerebral arteries).
◾️Nystagmus
First, the basics for defining nystagmus are discussed below.
- Nystagmus vs. Saccadic intrusion (see the following videos)
- Spontaneous Nystagmus at rest
- Definition of “At Rest”: This means the patient is looking straight ahead at primary gaze without moving their eyes to the left, right, up, or down.
- Definition of “Spontaneous”: This means the nystagmus is unprovoked. It is happening entirely on its own, not triggered by head movement (like the Dix-Hallpike test) or by looking to the side (gaze-evoked).
- Understand the Role of Visual Fixation
- Fixation suppresses nystagmus. If a patient has a mild peripheral vestibular deficit (like vestibular neuritis), their nystagmus might completely disappear when they focus on a target in a well-lit room.
- How to overcome it? If you don’t see nystagmus with the naked eye, it does not mean it is absent. To see the true nystagmus, you must remove visual fixation using Frenzel goggles (which magnify the eyes and block out light) or video-oculography (VOG). If the nystagmus disappears under Frenzel goggles, it is peripheral. If it persists or gets worse, it is central.
How to assess for nystagmus?
- #1. Check for spontaneous nystagmus at rest
- Ask the patient to look at a distant object (like a point on the wall across the room) rather than your nose.
- Looking at a distant object keeps the eyes in a relaxed, parallel position, which is ideal for spotting spontaneous drift. (If you ask them to look at your nose up close, you risk inducing convergence, which can alter the nystagmus).
- Ask the patient to look at a distant object (like a point on the wall across the room) rather than your nose.
- #2. Check for Gaze-Evoked Nystagmus (If Present at Rest)
- Ask the patient to look approximately 30 degrees to the left, and then 30 degrees to the right.
- Clinical Caveat: Avoid extreme lateral gaze (far lateral). Looking to the extreme mechanical limit of the eyes can provoke physiological end-point nystagmus in healthy individuals, which can lead to a false-positive interpretation for a central lesion.
- #3. Interpret the Pattern
- Nystagmus can be horizontal, vertical, tortional, or a combination *.
- Peripheral Pattern (Unidirectional): The nystagmus is purely horizontal and beats in one direction only, regardless of where the patient looks (e.g., it beats to the right when looking straight, right, and left).
- Central Pattern
- Direction-Changing (bidirectional): The nystagmus changes direction depending on the gaze (e.g., it beats right when looking right, and left when looking left). This is a red flag for a central lesion.
- Purely Vertical or Torsional: Any pure vertical (upbeat or downbeat) or purely torsional nystagmus is highly specific for a central lesion *,*.
- ☠️ See the table for high-risk nystagmus below.
- 📍Notes:
- Keep in mind that Spontaneous pure vertical or torsional are red flag for a central cause. This should not be conflated with vertical nystagmus evoked by the Dix-Hallpike test.
- Downbeat nystagmus can occasionally be provoked by the Dix-Hallpike test in anterior canal BPPV, but a spontaneous downbeat nystagmus at rest is a central red flag until proven otherwise.
- 👉Exceptions
- Pure vertical (upbeat or downbeat) nystagmus is highly suggestive of a central lesion. However, rare peripheral exceptions have been reported, particularly in the context of BPPV (bilateral pc-BPPV *) or after certain surgical procedures *.
- Pure torsional nystagmus is highly specific for a central lesion. The rare exception is a peripheral torsional nystagmus seen in superior canal dehiscence syndrome, which may be distinguished by its pulse-synchronous nature *.
- Keep in mind that Spontaneous pure vertical or torsional are red flag for a central cause. This should not be conflated with vertical nystagmus evoked by the Dix-Hallpike test.
- #4. The “Stop” Rule
- If the patient has NO spontaneous nystagmus at rest, the HINTS exam is invalid and cannot be performed. Pivot your assessment to gait/truncal stability and consider neuroimaging (MRI).
📊Nystagmus Quick Bedside Guide
👁️ The Nystagmus Exam: A Quick Guide (Click to Expand)
1. The Basics: Nystagmus vs. Saccades
Nystagmus
- Definition: A rhythmic, involuntary oscillation initiated by a pathological slow drift (the slow phase) off the target, followed by a corrective fast phase (a quick saccade) back to the target.
- Naming Convention: By convention, nystagmus is named for the direction of its fast phase (e.g., “right-beating nystagmus” means the fast phase beats to the patient’s right).
- Key Feature: The slow phase is the defining characteristic. Without a preceding slow drift, the movement is not nystagmus.
- Waveforms: Can be jerk (slow phase + fast phase) or pendular (slow phases only, without a corrective fast phase).
Saccadic Intrusions (and Oscillations)
- Definition: Rapid, inappropriate saccades (fast eye movements) that disrupt steady fixation by taking the eye away from the target, in the absence of a novel visual stimulus.
- Key Feature: The initiating movement is a fast phase (saccade). They are distinguished from nystagmus by the absence of a preceding slow phase.
- Subtypes (based on pauses):
- Without an intersaccadic interval (no pause): Ocular flutter (horizontal) and opsoclonus (multidirectional)—rapid, back-to-back saccades.
- With an intersaccadic interval (pause): Square-wave jerks (small, 150–200 ms pause) and macrosaccadic oscillations—a saccade off-target, a brief pause, then a return saccade.
2. Categorization by Elicitation
To separate benign from dangerous causes, nystagmus must be categorized by how it is elicited:
- Spontaneous
- Gaze-Evoked
- Triggered by maneuvers
Spontaneous Nystagmus (Primary Gaze)
- Peripheral Patterns: Horizontal-torsional, direction-fixed. Follows Alexander’s Law (worse when looking toward the fast phase). Usually suppressed by visual fixation.
- Central Red Flags:
- Purely Vertical (downbeat/upbeat) or Purely Torsional.
- Direction-changing (with gaze).
- Absence of nystagmus in a patient meeting AVS criteria (specificity >97%).
- ⚠️ Myth-Buster: Up to 60% of central strokes *will* suppress with visual fixation. Do not use suppression alone to rule out stroke.
Gaze-Evoked Nystagmus (Eccentric Gaze)
- Physiologic (Normal): Low-amplitude, unsustained, symmetric, only at extreme lateral gaze (>40°). Common in elderly.
- Central Red Flags: Sustained (>20s), high-amplitude, asymmetric, or present at 30° gaze. Indicates neural integrator dysfunction (cerebellar stroke, Wernicke’s, drug toxicity).
Triggered Nystagmus (Maneuvers)
- Positional (Dix-Hallpike / Supine Roll):
Peripheral: Transient (<60s), fatiguing, crescendo-decrescendo.
Central: Downbeat during Dix-Hallpike; Persistent apogeotropic (>60s) during Supine Roll. - Head-Shaking Nystagmus (HSN):
Peripheral: Horizontal, beating toward healthy ear.
Central: Perverted (Cross-Coupled) HSN—vertical nystagmus after horizontal shaking. - Valsalva / Hyperventilation: Hyperventilation can induce downbeat nystagmus (MS/cerebellar). Valsalva-induced can be central (Chiari) or peripheral (SCD).
⚠️ Important Context for the ED
- HINTS is ONLY for Spontaneous Nystagmus: Do not use HINTS on patients with Gaze-Evoked or Triggered nystagmus (like BPPV). It will be inaccurate.
- Trigger vs. Exacerbation: All vertigo can be exacerbated by movement. The key is whether symptoms are entirely triggered by movement (BPPV) or present at rest but worsened by movement (Neuritis/Stroke).
🎥Nystagmus vs. Saccade Intrusions
📝 Click to read the clinical description
📝 Click to read the clinical description
📝 Click to read the clinical description
⚠️Nystagmus Features Pointing Toward a Central Cause
To safely navigate the bedside assessment of nystagmus, clinicians must recognize the high-risk patterns that strongly suggest a central, life-threatening etiology and demand immediate neuroimaging *
⚠️ The Deadly Central Nystagmus Pattern (Click to Expand)
Assume a central cause (e.g., stroke) until proven otherwise if you observe any of the following:
1. Spontaneous Nystagmus (at rest / primary gaze)
- Purely vertical (upbeat or downbeat) or purely torsional.
- Direction-changing horizontal nystagmus (beats right on right gaze, left on left gaze).
- Absence of nystagmus in a patient meeting criteria for Acute Vestibular Syndrome (continuous vertigo, nausea, gait unsteadiness). (Specificity for central cause ~97.9%).
2. Gaze-Evoked Nystagmus (eccentric gaze)
- Pathologic gaze-holding nystagmus: Sustained (>20 seconds) or high-amplitude nystagmus at 30° lateral gaze.
- Rebound nystagmus: Nystagmus that appears upon returning to primary gaze after sustained eccentric gaze.
3. Triggered Nystagmus (provoked by maneuvers)
- Positional (Dix-Hallpike): Purely downbeat nystagmus.
- Positional (Supine Roll): Persistent apogeotropic horizontal nystagmus (>60 seconds) that does not fatigue or resolve with repositioning maneuvers.
- Head-Shaking: Perverted (cross-coupled) head-shaking nystagmus (vertical nystagmus induced by horizontal head-shaking). (Caveat: Rarely seen in Meniere’s disease, but highly predictive of a vestibulocerebellar lesion).
4. Visual Fixation (The Overrated Rule)
- Failure of fixation suppression is a central sign, but presence of suppression does NOT rule out a central cause (seen in up to 60% of strokes).
STEP 2: Syndromic Classification Using a Timing & Triggers Approach
Acute Vestibular Syndrome (AVS)
- Acute onset of continuous vertigo, dizziness, or unsteadiness.
- Lasting for days to weeks (typically >24 hours).
- Accompanied by new, ongoing vestibular system dysfunction, such as:
- Nausea and vomiting
- Spontaneous nystagmus at rest
- Postural instability/gait unsteadiness
- Head motion intolerance
📍Virtually all patients who present to the ED with ongoing vertigo should be considered to have AVS. In the ED, they are symptomatic even when at rest.
- Important Nuance: This percentage varies significantly based on how strictly AVS is defined and the clinical setting:
-
- In studies specifically requiring a stroke risk factor, the stroke rate was as high as 59%.
- In studies where nystagmus was mandatory, the rate was 22%.
- In studies where nystagmus was not mandatory (ICD-11 criteria), the rate was 25%.
- In studies specifically looking at “Isolated AVS” (where the patient has no other focal neurological deficits, such as limb weakness or dysarthria), the stroke rate drops to 5%
- Note: The Coban 2026 review also highlights that the absence of nystagmus in a patient with acute continuous dizziness is a strong red flag for a central cause, as up to 50% of central AVS cases may lack nystagmus *.
- Studies show that MRI-DWI can be falsely negative in ~12–20% of posterior circulation strokes during the first 48 hours after symptom onset in AVS patients—and the miss rate is even higher for small brainstem or cerebellar strokes *,*.
-
Why this matters: You can’t just order an early MRI and breathe a sigh of relief. A negative scan in the first two days does not reliably exclude a stroke.
- This is precisely where HINTS/HINTS Plus earns its keep.
- When performed by a trained clinician, it can help distinguish a peripheral cause (vestibular neuritis) from a central one (posterior circulation stroke), sometimes outperforming that early scan.
◾️Differential Diagnosis of AVS
- The Two Most Important Diagnoses (The “Rule In / Rule Out” Core)
- Other causes of AVS are mentioned in the following table
◾️Diagnostic Approach to AVS
- The diagnostic approach to a patient with dizziness is overviewed here.
- 📍Key point: GRACE-3 and Sars 2026 emphasize that you must screen for “central features” like the “Deadly Ds” before even applying HINTS to a suspected AVS patient *.
The Two Episodic Syndromes: s-EVS and t-EVS
Once you determine the patient’s dizziness is episodic (it comes and goes, with the patient returning to baseline between attacks), the next question is: Is it triggered, or is it spontaneous?
Spontaneous Episodic Vestibular Syndrome (s-EVS)
◾️Patient says: “It just happens out of nowhere.”
-
What it looks like: Sudden attacks of dizziness with no clear trigger. Episodes typically last minutes to hours, and the patient is perfectly fine in between.
-
The exam catch: By the time they reach the ED, they’re usually asymptomatic, so you can’t reproduce it at the bedside. The diagnosis lives and dies on the history.
◾️Differential diagnosis
- Posterior circulation TIA:
- The dangerous one. Hunt for the “deadly Ds” (diplopia, dysarthria, dysphagia, dysphonia, dysmetria, dysesthesia) or a sudden-onset story.
- Vestibular migraine
- The most common benign cause. Look for a migraine history, light/sound sensitivity, or visual auras.
- Ménière’s disease
- Episodes of 20 minutes to 12 hours, paired with fluctuating hearing loss, tinnitus, or ear fullness.
- Cardiac arrhythmia or panic attack
- Worth keeping on your radar, especially if presyncope is part of the picture.
- Vestibular Paroxysmia (VP): See following table 👇
Triggered Episodic Vestibular Syndrome (t-EVS)
◾️Patient says: “It only happens when I do this.”
-
What it looks like: Brief attacks (seconds to minutes) reliably provoked by a specific trigger, usually a head movement or a change in posture.
-
The exam advantage: Patients are fine at rest, but you can reproduce the symptoms right there in the ED (think Dix-Hallpike or supine roll).
◾️Differential diagnosis
- BPPV
- The most common cause. Brief spinning triggered by rolling over in bed or looking up. Discussed above.
- Orthostatic hypotension
- Triggered by standing up. Could be benign (dehydration, meds) or dangerous (GI bleed, sepsis).
- Superior canal dehiscence syndrome (SCDS)
- Triggered by loud sounds (Tullio phenomenon) or pressure changes (Valsalva).
- Central paroxysmal positional vertigo (CPPV). See the following table 👇
STEP 3: Choose the Correct Bedside Vertigo Test for Vertigo
Episodic Vertigo
Dix-Hallpike
- Suspected triggered episodic vestibular syndrome (t-EVS) (a patient with episodic, position-triggered symptoms and no ongoing vertigo and no spontaneous nystagmus at rest), specifically to diagnose posterior canal BPPV (pc-BPPV) in patients with brief, position-triggered vertigo.
- ⚠️ Pitfall: If patient history suggests positional vertigo, you should still do the test.
⛔️ When NOT to perform:
- Patients with non-paroxysmal (continuous) vertigo or those with neurological deficits (e.g., truncal ataxia), as the test is invalid and may provoke unnecessary symptoms.
- NOT indicated when the patient has nystagmus at rest.
🎯Test Performance
- The Dix-Hallpike test is the gold standard for diagnosing posterior canal BPPV, with reported sensitivity of approximately 82% and specificity of 71% when performed by specialty clinicians *. However, accuracy is significantly lower in primary care settings (sensitivity ~45%), underscoring the importance of proper training and technique
💡Interpretation:
- A positive test (transient, crescendo-decrescendo upbeat-torsional nystagmus with latency) confirms pc-BPPV and should be immediately followed by an Epley maneuver.
- The “upbeat” component is indeed a vertical movement (the fast phase beats upward).
- It is typically accompanied by a torsional (rotational) component.
- Note that this vertical nystagmus is seen in the Dix-Hallpike test. It is not spontaneous (at rest) vertical nystagmus, which is a red flag for a central cause.
- A negative test does not exclude BPPV (consider horizontal canal BPPV or “subjective” BPPV).
💡 Pearl: Interpreting a “Negative” Dix-Hallpike (Click to Expand)
A “negative” Dix-Hallpike (no visible nystagmus) does NOT rule out BPPV.
- Subjective BPPV: The maneuver may perfectly reproduce the patient’s typical position-induced symptoms (vertigo) without any visible eye movements. Reproducing the exact positional vertigo is highly valuable—if it feels like BPPV, treat it like BPPV.
- Visual Fixation: Staring at a target can suppress the nystagmus. Consider Frenzel lenses or video-oculography (VOG) to unmask it.
- Wrong Canal: The Dix-Hallpike tests the posterior canal. If the crystals are in the horizontal canal (hc-BPPV), the test may be negative or show horizontal nystagmus instead. Perform the Supine Roll Test.
- Fatigue & Dispersion: The nystagmus can fatigue on repeat testing, or the debris may be too dispersed to generate a strong current—even though the positional change still triggers vertigo.
⚒️Technique
- Pre-Test Preparation
- Explain & Consent: Describe the maneuver beforehand and obtain the patient’s cooperation.
- Set Expectations: Warn that it may briefly provoke intense vertigo, but reassure them it will be short-lived and diagnostic at the bedside.
- Manage Nausea: Consider pre-treating with antiemetics if severe nausea is likely to prevent the patient from completing the test.
- Procedure
- Positioning: Seat the patient, turn their head ~45° toward the tested side, then lower them briskly to supine with the head extended 20–30° below horizontal (keep supported).
- Observation: Instruct the patient to keep eyes open and avoid fixating on you so eye movements can be clearly observed.
- Timing: Wait at least 30–60 seconds for latency before declaring a “negative” test.
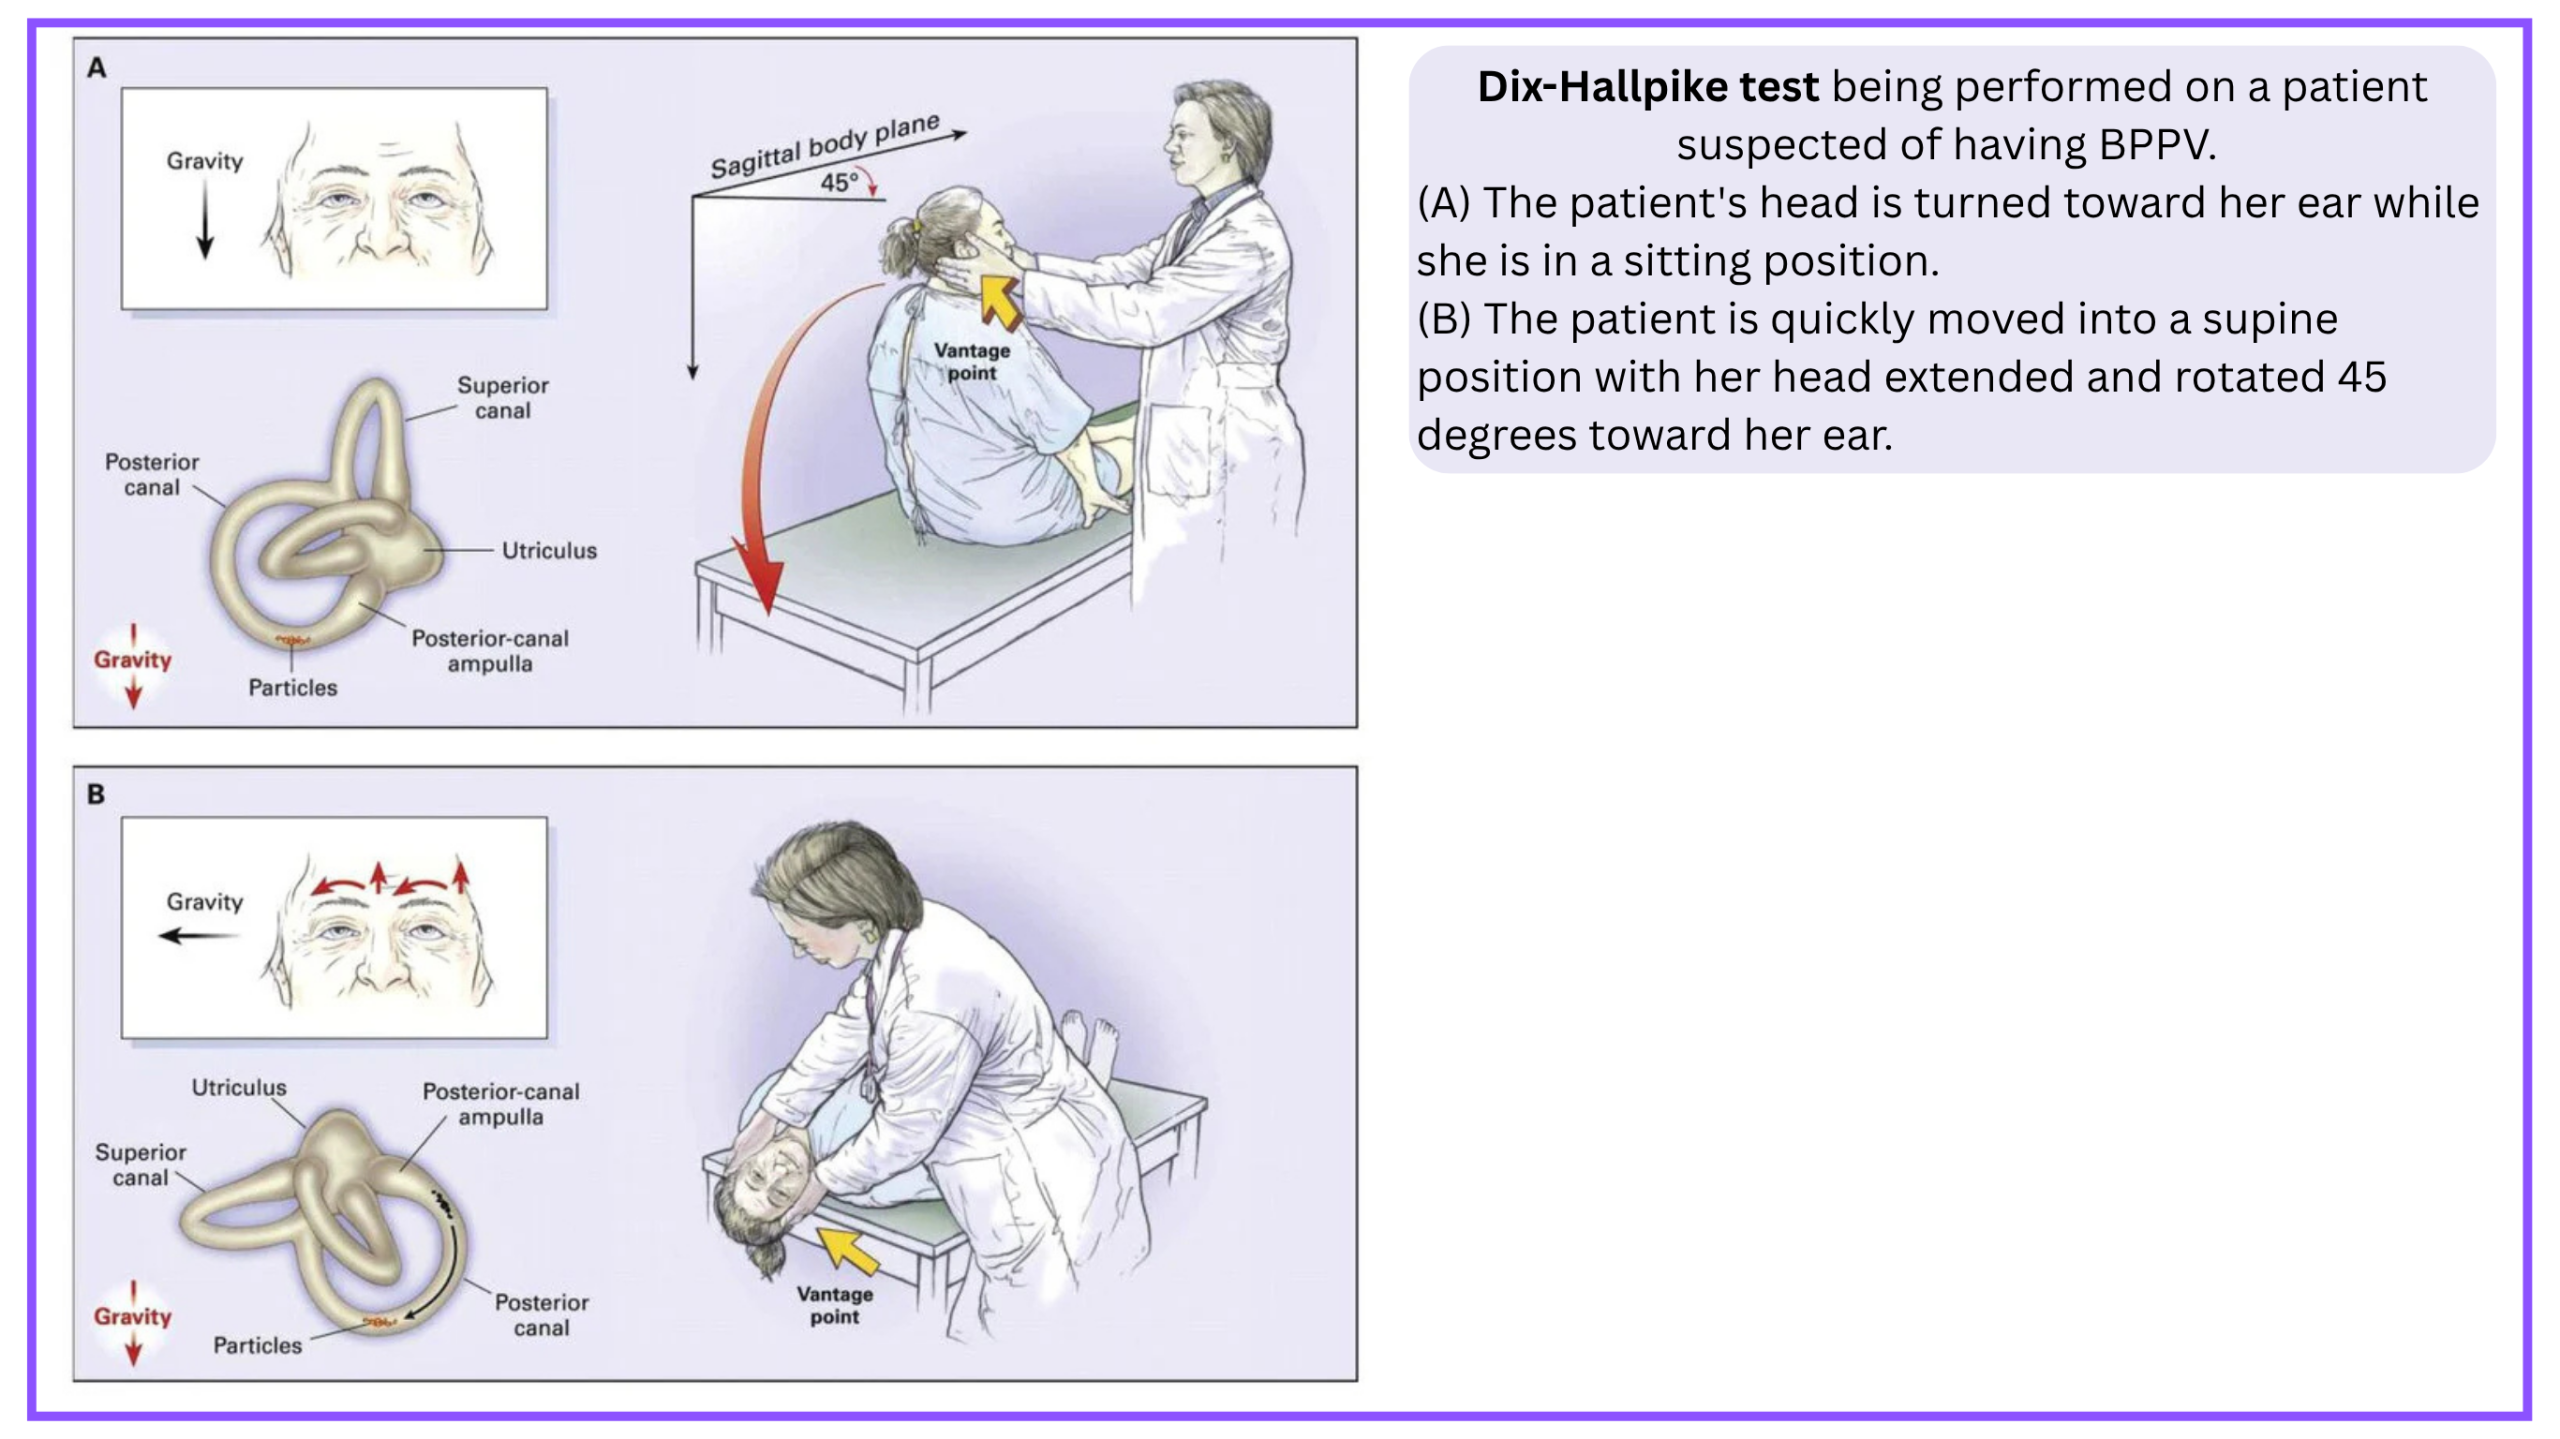
Supine Roll Test
- If Dix-Hallpike is negative or indeterminate, but the history still suggests BPPV, consider a follow-up supine roll test for horizontal canal BPPV (hc-BPPV), looking for provoked horizontal nystagmus.
- The corresponding repositioning maneuver (Gufoni) is more specialized; consider using appropriate teaching resources or referral to a vestibular physiotherapist.
Straight head hanging (ac-BPPV)
Although the anterior canal (AC) variant of BPPV is rare, mainly owing to its orientation relative to gravity (which makes otoconial debris much less likely to enter it), it can occur.
- In a patient with ac-BPPV, nystagmus may be provoked by the right or left Dix-Hallpike maneuvers, as well as with straight head hanging (video below).
- A right Dix-Hallpike maneuver will stimulate the right posterior canal (PC) as well as the left AC.
- When the Dix-Hallpike or head-hanging maneuver is performed, the hallmark sign of anterior canal BPPV is a positional downbeating nystagmus (pDBN)
- Direction: The fast phase of the nystagmus beats downward (toward the patient’s feet).
- Torsion: There is often a small torsional component, but it can be subtle or absent, making the downbeat the most consistent feature.
- Latency: Like other BPPV types, there may be a brief latency (a few seconds) before the nystagmus appears.
- Straight Head-Hanging (SHH) maneuver (moving from sitting to lying with the head tilted straight back) may be even more sensitive than the standard Dix-Hallpike for eliciting the downbeating nystagmus of anterior canal BPPV *.
- When the Dix-Hallpike or head-hanging maneuver is performed, the hallmark sign of anterior canal BPPV is a positional downbeating nystagmus (pDBN)
⚠️ Important Clinical Caveat
- Because downbeating nystagmus can also be a sign of a central lesion (such as a cerebellar or brainstem stroke), it is crucial not to assume it is BPPV automatically.
- If the nystagmus is purely vertical (without torsion), persists without fatiguing, or is accompanied by other neurological signs, a central cause must be ruled out with MRI.
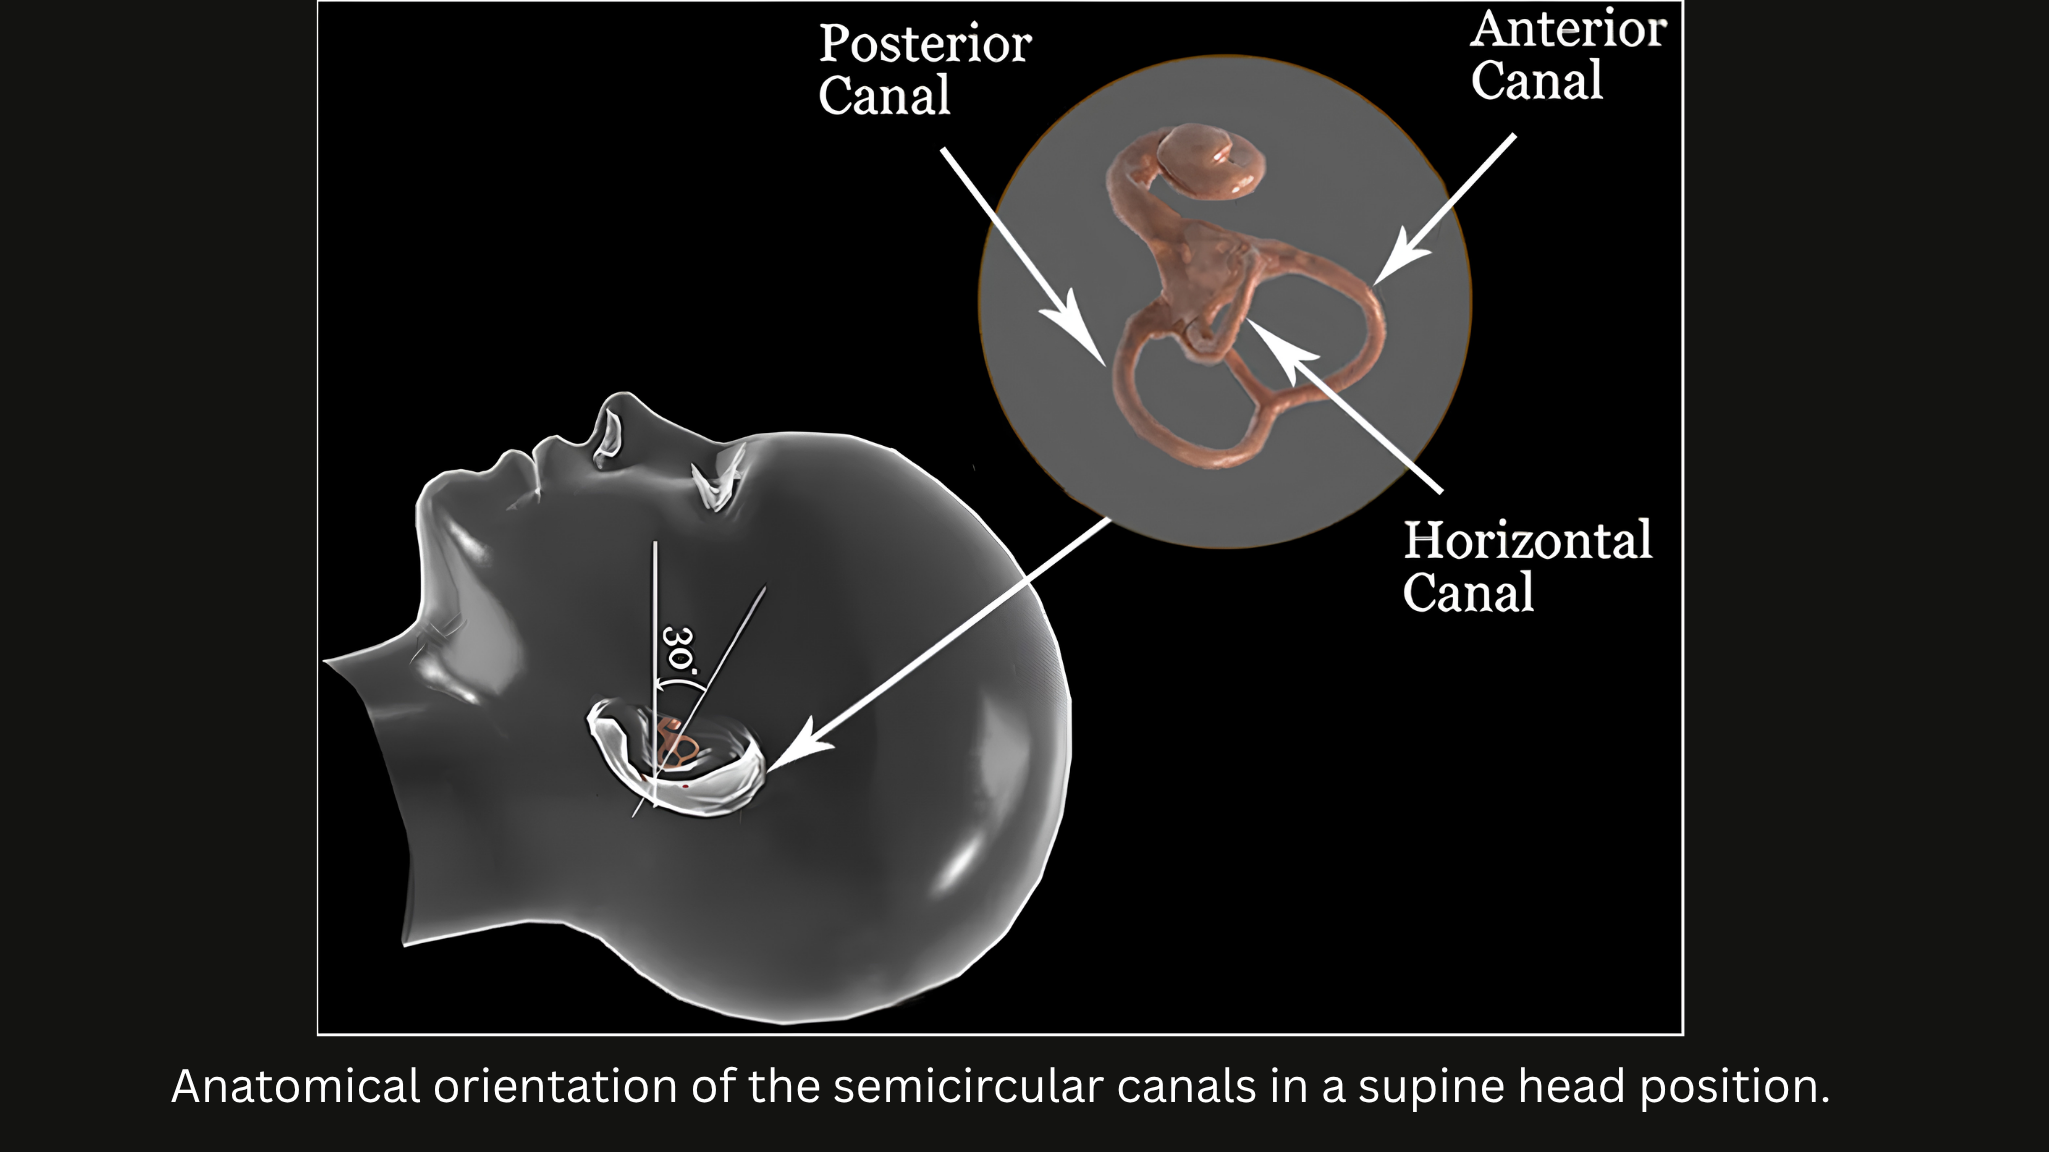
Continuous Vertigo
HINTS Plus (Head Impulse, Nystagmus, Test of Skew + Hearing)
✅ Indication:
- Acute vestibular syndrome (AVS) with spontaneous nystagmus at rest, performed by a trained clinician, to distinguish peripheral (vestibular neuritis) from central (stroke) causes
⛔️ When NOT to perform
- Patients without nystagmus at rest, those with intermittent/episodic dizziness, or those with obvious central signs (focal deficits, inability to walk, new headache/neck pain) should be screened first.
🎯Test Performance
- Sensitivity: 92.9%, Specificity: 83.4% when performed correctly by a trained clinician.
- In AVS Patients: Sensitivity is 93.1%
- The diagnostic accuracy of HINTS drops significantly if performed by untrained clinicians
- It has higher diagnostic accuracy for stroke than an early MRI-DWI in the first 24–48 hours. Early MRI was falsely negative in 15% of strokes (sensitivity 85.1%), whereas HINTS had a sensitivity of 95.3%*.
⚒️ Technique *
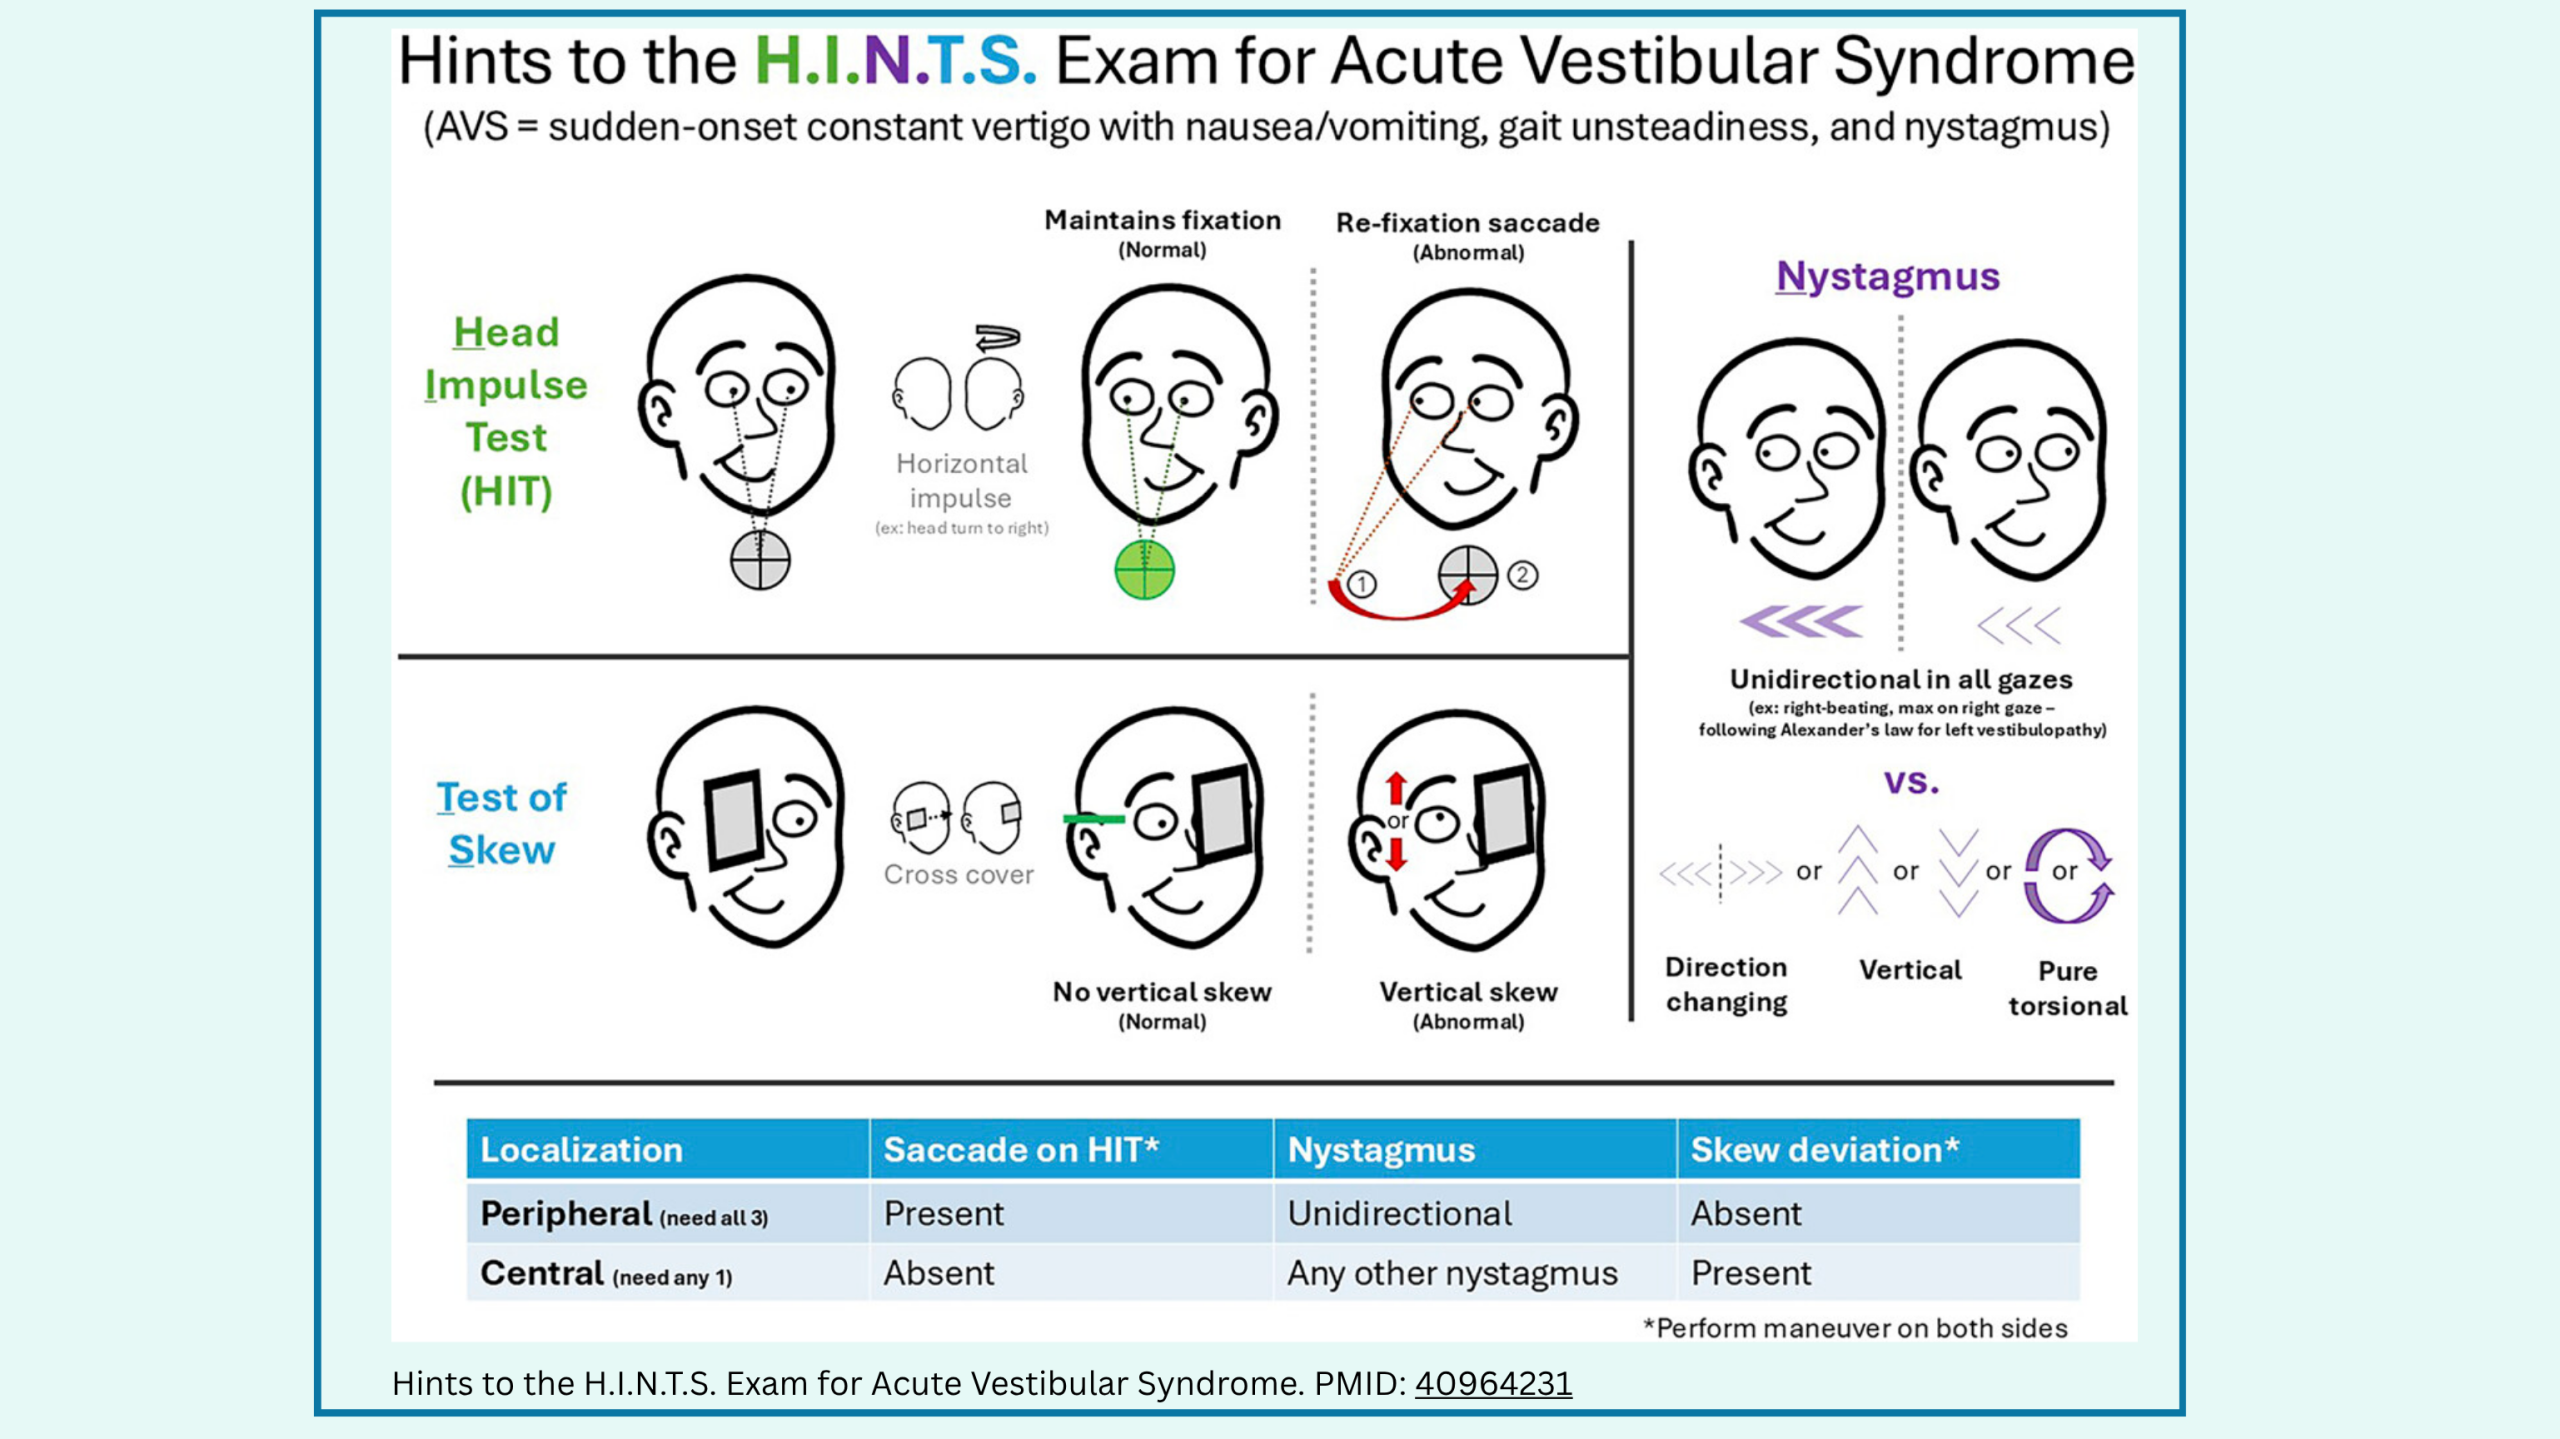
◾️N: Nystagmus
- How to do it: As described in the Physical Examination section above (look straight ahead, then 30° left and right). The key here is to observe how the nystagmus behaves during these gaze shifts.
- Clinical Value in HINTS: This is the entry criterion for the HINTS exam. If there is no spontaneous nystagmus at rest, stop—the HINTS exam is invalid (explained above). If nystagmus is present, interpret it as follows:
- Peripheral: Horizontal, direction-fixed (beats in one direction only).
- Central Red Flag: Direction-changing (beats right on right gaze, left on left gaze) or purely vertical/torsional *.
◾️HI: Head Impulse Test
- How to do it: Ask the patient to fixate on your nose. Hold their head with both hands and rapidly turn it 10–20° to one side (a quick, small-amplitude flick). Observe their eyes during the movement.
- Clinical Value: Tests the vestibulo-ocular reflex (VOR).
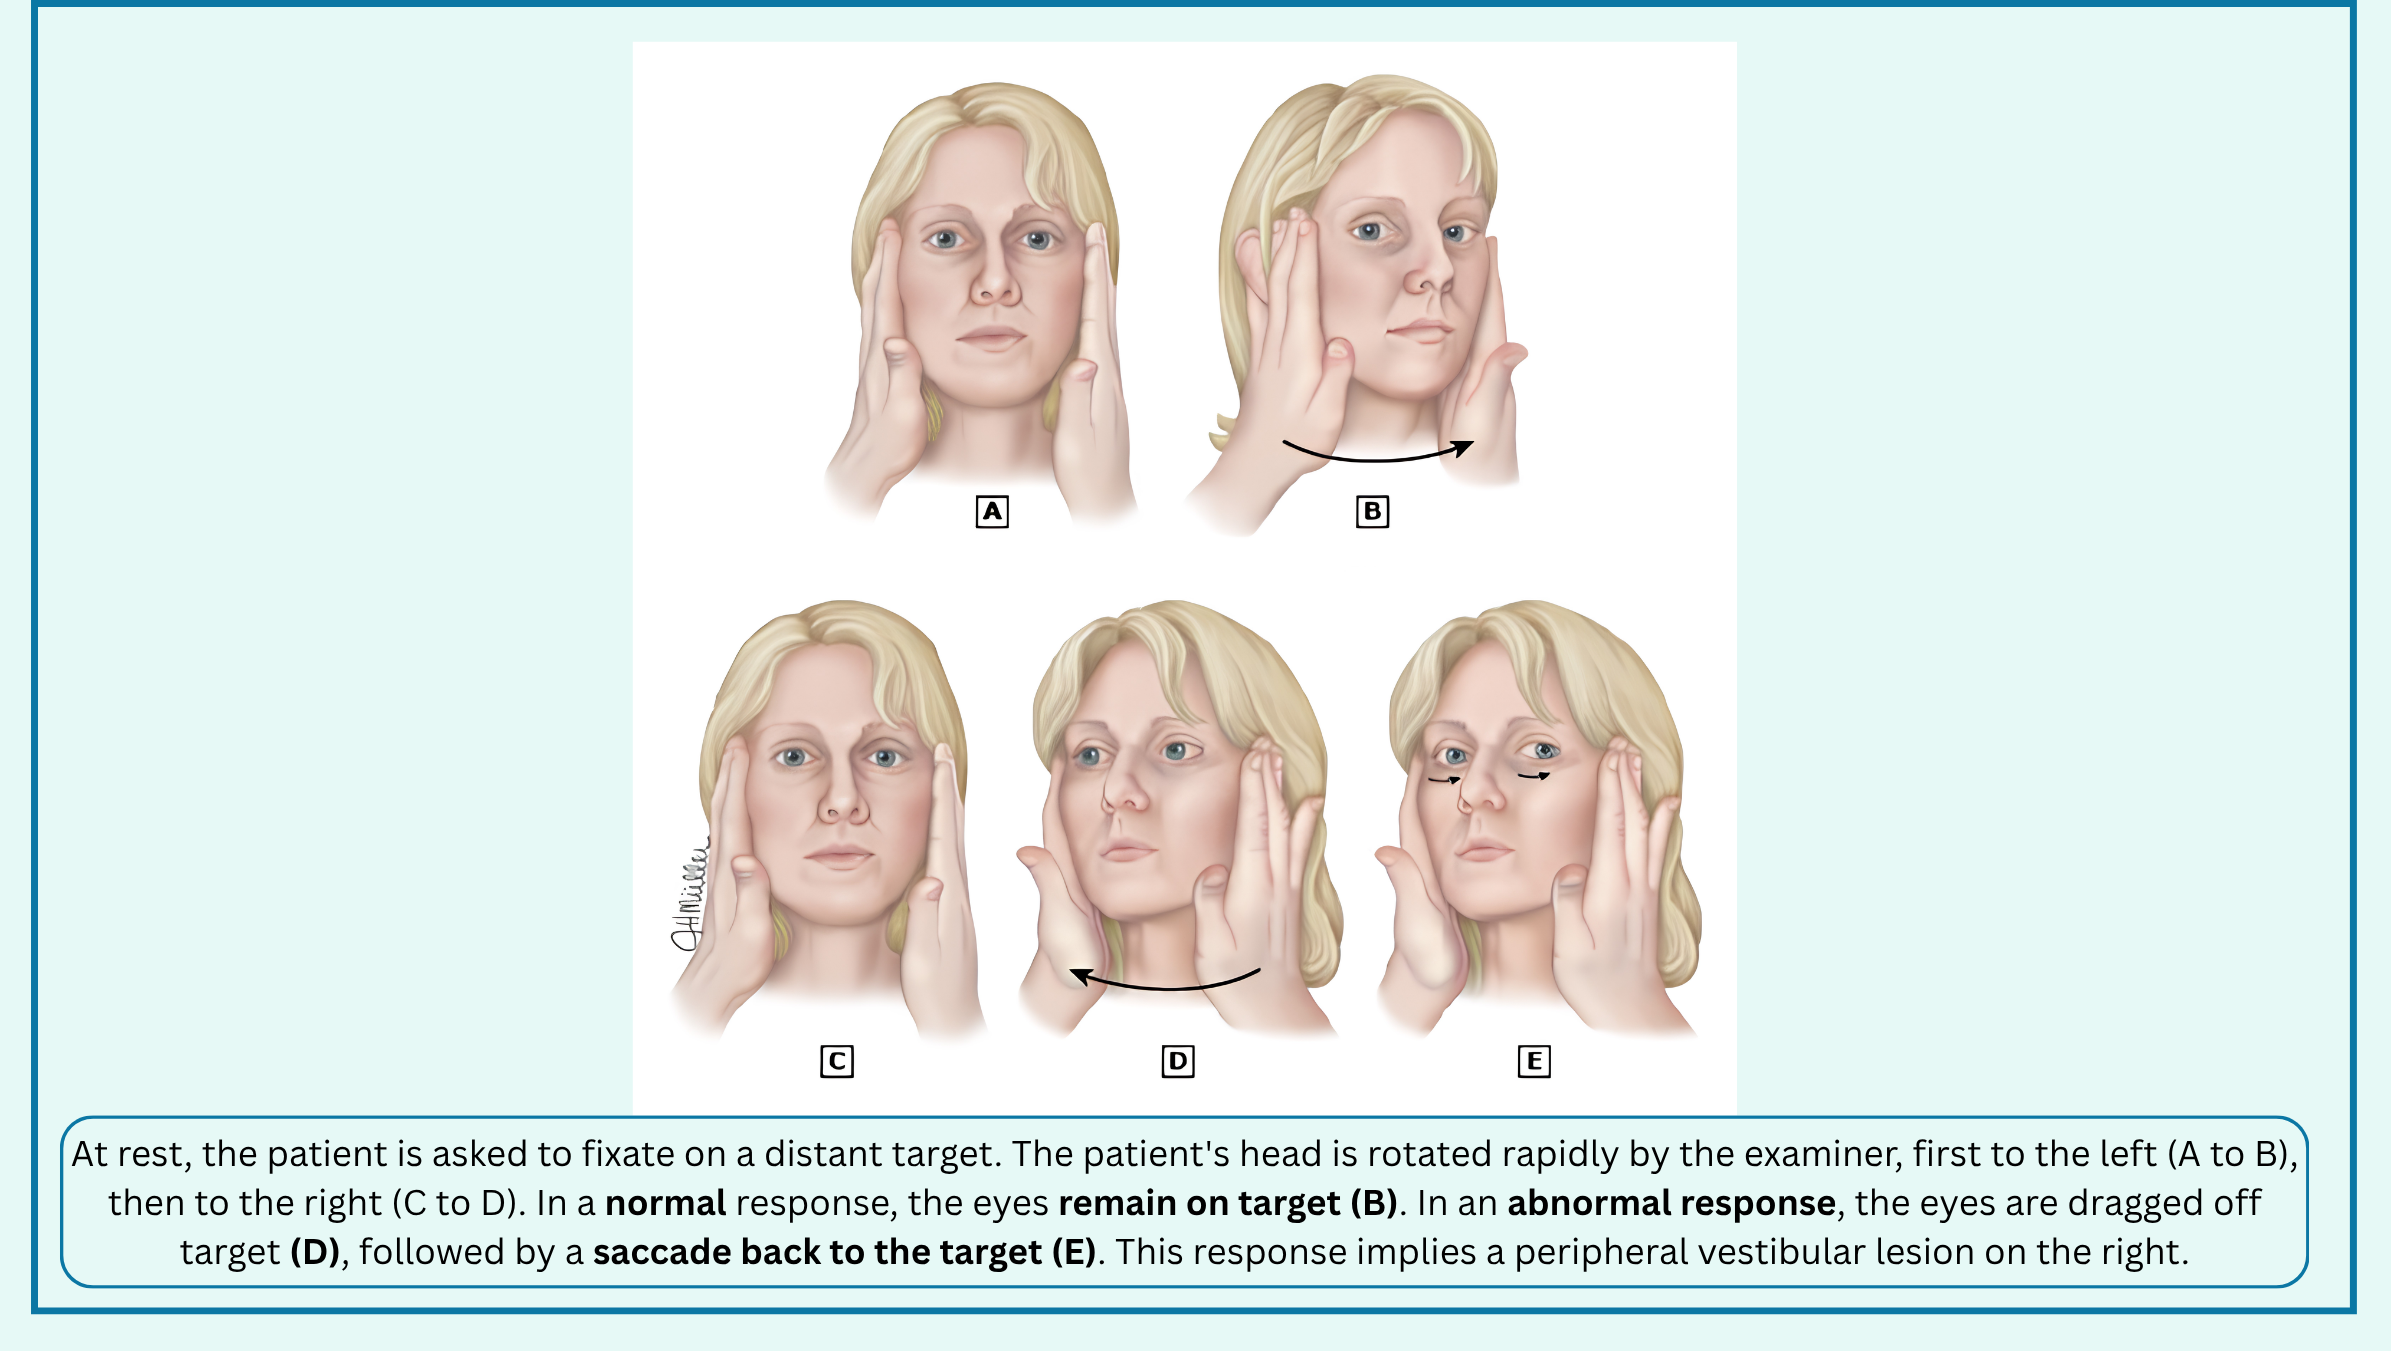
- Abnormal (Peripheral): The eyes move with the head, then a corrective saccade snaps them back to your nose, indicating a lesion of the vestibular nerve/labyrinth, like neuritis. This suggests a peripheral and usually benign etiology for AVS, though with one EXCEPTION!
- ⚠️Stroke in the distribution of the AICA is an exception, and since the abnormal HIT in this situation often reflects labyrinthine ischemia, it is not a benign cause of the AVS
- Normal (Central Red Flag): The eyes stay perfectly locked on your nose with no corrective saccade: Indicates the brainstem/cerebellum is intact, suggesting stroke.
- Abnormal (Peripheral): The eyes move with the head, then a corrective saccade snaps them back to your nose, indicating a lesion of the vestibular nerve/labyrinth, like neuritis. This suggests a peripheral and usually benign etiology for AVS, though with one EXCEPTION!
- Interpritation
- Abnormal HIT
- A unilateral Abnormal HIT suggests a peripheral (Vestibular Neuritis) cause (if other components of HINTS were met, table below).
- A bilateral Abnormal HIT should make you think strongly for a central cause *, such as:
- Wernicke’s encephalopathy.
- Unilateral Infaction of cerebellar flocculus: since cerebellar flocculus has a role in modulation of the high-frequency vestibulo-ocular reflex, an acute unilateral infarction of the flocculus is another possible cause of bilaterally abnormal head impulse testing
- Normal HIT is suggestive of a central cause.
- Abnormal HIT
◾️Test of Skew
- How to do the Test of Skew
- The Setup: Ask the patient to look directly at your nose (or a fixed target).
- The Technique (The Alternate Cover Test):
- Quickly cover one of the patient’s eyes with your hand or a card.
- Remove it, and immediately cover the other eye.
- Repeat this alternating back-and-forth a few times.
- The “Pro-Tip” (Crucial for accuracy): Don’t follow the eye that is being uncovered. Instead, keep your focus strictly on one eye (it doesn’t matter which one) for several cycles. This makes it much easier to spot the tiny vertical correction movement.
- How to Interpret It
- Normal (Peripheral): Both eyes remain perfectly aligned horizontally. When you uncover an eye, it stays looking straight at your nose. There is no vertical correction.
- Abnormal (Central): When you uncover an eye, it makes a small vertical (or diagonal) movement to re-align with the other eye. Think of it as one eye pointing slightly higher than the other, and it has to “snap” up or down to fixate. (Note: Horizontal shifts do not count—only vertical or diagonal shifts count).
- 💡 The Clinical Pearl:
- Any vertical correction (skew deviation) is a strong central sign (often pointing to a midbrain or brainstem lesion). It is one of the three components of the HINTS exam.
- However, remember the golden rule of HINTS: it is only valid in patients with Acute Vestibular Syndrome (continuous vertigo) and spontaneous nystagmus.
◾️The “Plus” in HINTS Plus: The Hearing Test
- How to do it:
- Ensure the ear canal is clear of wax.
- Rub your thumb and index finger together briskly, starting about an arm’s length away.
- Bring your fingers closer, just lateral to the patient’s left ear, and ask if they can hear it clearly.
- Repeat on the right ear.
- The key question: Ask the patient, “Is this new, or have you had trouble hearing on that side before?”
- How to interpret it:
- Normal (Peripheral): Hearing is relatively symmetric, and there is no new deficit.
- Abnormal (Central Red Flag): New unilateral hearing loss.
- 💡 Why this matters (The Clinical Pearl):
- This is the “trap” that catches even experienced clinicians. An AICA (anterior inferior cerebellar artery) stroke can infarct both the brainstem/cerebellum and the inner ear (labyrinth) at the same time.
- Because the labyrinth is damaged, the Head Impulse Test will be abnormal (falsely reassuring you that it’s a benign peripheral issue).
- However, because it’s a stroke, the patient will also have new hearing loss.
- If you see an abnormal Head Impulse and new hearing loss, do not stop at Vestibular Neuritis. Treat it as a central cause (AICA stroke) until proven otherwise.
- This is the “trap” that catches even experienced clinicians. An AICA (anterior inferior cerebellar artery) stroke can infarct both the brainstem/cerebellum and the inner ear (labyrinth) at the same time.
Interpretation of HINTS Exam
Once the bedside components are performed, their findings must be synthesized to determine whether the pattern is consistent with a peripheral or central etiology. See the table below 👇
👁️ HINTS Exam (Click to Expand)
Turn the patient’s head 10–20° rapidly toward one side while they maintain a fixed gaze on your nose.
Observe the eyes in primary gaze, then have the patient look right and left. Look for the fast phase of nystagmus.
Alternately cover one eye, then the other in rapid succession while the patient looks at your nose.
- Peripheral (Vestibular Neuritis): ALL three findings must be “peripheral” (abnormal Head Impulse, direction-fixed horizontal nystagmus, and normal test of skew).
- Central (Stroke): ANY single “central” finding (normal Head Impulse, direction-changing/vertical/torsional nystagmus, OR abnormal skew) overrides the rest and indicates a central cause.
- Validity: HINTS is only valid for Acute Vestibular Syndrome (AVS) in patients with spontaneous nystagmus. Do not use it for episodic (BPPV) or gaze-evoked vertigo.
To solidify these interpretive principles, the following video demonstrates the HINTS Plus examination in real patients, highlighting the contrast between a benign peripheral pattern and a central pattern concerning for stroke
Video not playing? Download the MP4 directly here.
Diagnostic Imaging
While bedside testing helps stratify risk, selecting the appropriate neuroimaging modality requires careful consideration of the suspected etiology, symptom timeline, and specific clinical red flags. See the table below 👇
🖥️ Diagnostic Imaging Recommendations (Click to Expand)
-
Cerebellar/brainstem stroke (Acute Vestibular Syndrome – AVS):
- Do NOT routinely use CTA for isolated, continuous vertigo (AVS). The diagnostic pathway relies on HINTS and MRI.
- Emergent MRI if acute intervention not indicated or HINTS plus indicates central cause and more than 48 hours of vertigo.
- Admit to hospital and perform delayed MRI in 2–3 days if acute intervention not indicated; HINTS plus indicates central cause and symptoms less than 48 hours (due to early false-negative rates).
- Exception – When CTA IS Indicated in AVS: CTA is reserved for specific high-risk scenarios:
- Suspected Basilar Artery Occlusion (BAO): (baseline mRS 0-1, NIHSS ≥ 10, and pc-ASPECTS ≥ 6). CTA is essential to confirm the occlusion and proceed with EVT within 24 hours. It is the key diagnostic step to identify this time-sensitive, life-threatening posterior circulation LVO.
- Recurrent TIA-like episodes (s-EVS): where vascular stenosis is a concern.
- Suspected dissection: (significant neck pain or trauma).
- Vestibular migraine: None required if clinical history and presentation are diagnostic for vestibular migraine.
- Suspected vertebral artery dissection (significant ongoing neck pain): CT angiography or MRI/MRA of head and neck.
- TIA with neurologic symptoms or signs beyond vertigo and nystagmus: CT angiography or MRI/MRA.
- Suspected TIA without neurologic symptoms (isolated vertigo): Consider CT angiography or MRA if patient has significant risk factors for stroke/TIA; an optimal diagnostic strategy has yet to be defined.
- Ménière’s disease: None required for typical presentations. However, delayed post-gadolinium MRI (Hydrops MRI) can be considered for ambiguous or atypical cases to visualize endolymphatic hydrops and differentiate from vestibular migraine.
- Suspected cerebellar hemorrhage (significant ongoing headache or decreased level of consciousness): CT of the head.
- Multiple sclerosis: MRI.
- Postconcussive vertigo: CT of the head if intracranial hemorrhage suspected.
-
Labyrinthitis:
- Viral: None
- Bacterial: MRI
- Superior canal dehiscence syndrome: CT of temporal bone (ultra-high-resolution). Note: Clinical correlation is essential as imaging can overestimate true dehiscence due to volume averaging.
- Vestibular schwannomas: MRI.
References: 1. Edlow JA, et al. GRACE-3: Guidelines for Reasonable and Appropriate Care in the Emergency Department. Acad Emerg Med. 2023;30(5):442-486. 2. AHA/ASA Guideline for the Early Management of Patients With Acute Ischemic Stroke: 2026 Update. Stroke. 2026. 3. Kim et al. Diagnostic value of delayed post-gadolinium MRI in Menière’s disease. Otol Neurotol. 2024. 4. 2026 study on ultra-high-resolution CT for Superior Canal Dehiscence Syndrome (overestimation due to volume averaging). 5. Seetge J, Tarnutzer AA. Diagnostic challenges in posterior circulation ischemic stroke presenting with acute dizziness and vertigo. Front Neurol. 2026;17:1960712.
◾️CTA
- This is the diagnostic cornerstone for identifying a large-vessel occlusion (LVO), including in the posterior circulation (vertebral arteries, basilar artery, and P1 segment of the posterior cerebral artery).
- 🎯The primary goal is to confirm the presence of a treatable occlusion to offer endovascular thrombectomy (EVT) *.
- Specific Indications for Posterior Circulation Stroke
- PCS are frequently missed on initial presentation. The literature emphasizes maintaining a low threshold for CTA in patients with symptoms suggestive of vertebrobasilar ischemia, even if they don’t fit the classic “stroke” picture *.
- Indications:
- Unexplained Decreased Level of Consciousness Without a Clear Cause
- Cranial Nerve Abnormalities, e.g., diplopia, dysarthria, facial weakness.
- Severe Vertigo with Neurologic Findings: Vertigo accompanied by other neurological signs (e.g., ataxia, sensory loss).
- Quadriparesis: Weakness in all four limbs.
- Fluctuating Symptoms: Symptoms that come and go, which is characteristic of basilar artery occlusion.
- ⏱️Timing & Patient Selection
- Early Window (< 6 hours): CTA is indicated to detect LVO and expedite thrombectomy for eligible patients.
- Late Window (> 6 hours): Recent trials (such as MR CLEAN LATE) suggest that CTA can also be used to select patients for EVT based on collateral assessment (good collateral flow), even if perfusion imaging (CTP) does not show a penumbra *.
- “CTA-for-All” Concept: Some literature advocates for emergent CTA in all patients presenting within 24 hours of symptom onset, regardless of baseline NIHSS score, because LVO can only be diagnosed by vascular imaging, and mild deficits can still harbor a dangerous proximal occlusion.
- 🚨 Important Caveat
- While CTA is essential, it is important to note that its sensitivity for detecting PCS overall is lower (~44%) compared to the anterior circulation. However, it is roughly 80% sensitive for vertebrobasilar occlusion in selected cohorts. Therefore, a negative CTA does not entirely rule out a PCS, and MRI with DWI may be needed if clinical suspicion remains high *.
◾️MRI
- Background
- Non-Contrast CT for PCS: Sensitivity 16-44%
- CTA is roughly 80% sensitive for vertebrobasilar occlusion; it is only ~44% sensitive for posterior circulation stroke overall *.
- 📍Therefore, a negative CT/CTA does not rule out a stroke.
- The Role of DWI-MRI
- Diagnostic
- This is the most sensitive modality, with pooled estimates around 80% sensitivity and high-resolution DWI approaching 90-95% in some series.
- ⚠️Caveat: it is important to note that even early MRI-DWI (within the first 24-72 hours) can miss 10-20% of PCS. If suspicion remains high after a negative MRI, a repeat study in 1-2 days may be considered.
- Selecting Patients for Reperfusion Therapy
- MRI is also indicated for treatment selection, particularly in extended time windows or specific scenarios.
- Extended Window Thrombolysis (4.5–9 hours or Wake-up Stroke): For patients with unknown onset time or those presenting beyond 4.5 hours, MRI DWI-FLAIR mismatch can be used to identify patients who may still benefit from intravenous thrombolysis.
- Pediatric Stroke: The updated AHA/ASA guidelines specifically recommend MRI guidance for thrombectomy in pediatric patients with acute ischemic stroke, minimizing radiation exposure compared to CT-based approaches.
- MRI is also indicated for treatment selection, particularly in extended time windows or specific scenarios.
- Diagnostic
- 💡 Key Takeaway
- MRI is not routinely the first-line imaging modality for all suspected strokes (CT/CTA remains the rapid initial workhorse). Instead, MRI is indicated as a problem-solving tool when the clinical picture strongly suggests a posterior circulation stroke, but initial CT/CTA is unrevealing, or as a selection tool for reperfusion therapy in extended time windows.
Specific Conditions
Vestibular Migraine
◾️Epidemiology
- Vestibular migraine is the most common central cause of vertigo.
- After BPPV, it is the second most frequent cause of vertigo in the ED.
- In the ED, it is a diagnosis of exclusion that hinges on recognizing a characteristic episodic vestibular pattern intertwined with migrainous features, after ruling out dangerous central and peripheral mimics *.
◾️Diagnostic criteria
-
VM is defined by the Bárány Society and International Headache Society consensus as recurrent vestibular symptoms (spontaneous or positional vertigo, head-motion intolerance, visually induced dizziness) occurring in patients with a history of migraine *. The diagnosis is purely clinical; there is no definitive biomarker or imaging finding.
- Definite Vestibular Migraine (Bárány/IHS Criteria) requires all four of the following *:
- At least 5 episodes of vestibular symptoms of moderate to severe intensity, lasting 5 minutes to 72 hours.
- Current or previous history of migraine (with or without aura) per ICHD criteria.
- At least 50% of episodes are accompanied by at least one migrainous feature: headache with migrainous characteristics, photophobia/phonophobia, or visual aura.
- Not better accounted for by another diagnosis (e.g., TIA, Menière’s, BPPV).
- Probable Vestibular Migraine applies when the history of migraine is absent, but migrainous features occur during the attacks, or when episodes are atypical in duration but otherwise fit
🚑 ED Approach: Exclusion & Red Flags
In the emergency setting, your primary task is to exclude central causes (posterior circulation stroke/TIA) and peripheral mimics (BPPV, Menière’s, vestibular neuritis). The diagnosis of VM is retrospective and rarely confirmed during a single ED visit.
- Focused History (The Diagnostic Core)
- Pattern: Ask about episodic vertigo (minutes to hours) versus continuous (AVS). True VM is episodic; continuous vertigo is a red flag for stroke or neuritis.
- Migrainous Features: Headache is not required, as up to 32% of VM patients have vertigo without headache *. Ask specifically about photophobia/phonophobia, visual aura, and head-motion intolerance during episodes *.
- Triggers: Stress, sleep deprivation, hormonal changes, and specific foods are common, but not required.
- Bedside Examination (When Symptomatic)
- Nystagmus: During an acute attack, you may see central or peripheral patterns (spontaneous, positional, or gaze-evoked). A purely peripheral pattern (unidirectional horizontal) does not exclude VM, but any central red flag (direction-changing, vertical, skew) mandates stroke workup.
- HINTS:
- A normal HINTS exam (negative head impulse, no skew) in a patient with continuous vertigo is concerning for a central cause—do not assume VM if HINTS is central.
- Between Attacks
- The exam is typically normal. Any persistent focal deficit or central nystagmus at rest is a red flag.
🚩Red Flags Mandating MRI/CTA (Do Not Diagnose VM)
- Acute continuous vertigo (AVS) with central HINTS pattern.
- New focal neurologic deficits (diplopia, dysarthria, hemiparesis).
- Sudden onset (“thunderclap”) headache.
- Significant vascular risk factors (age >50, hypertension, diabetes, smoking) with new-onset vertigo.
⚠️ Important diagnoses that must be cleared in ED (all of which can also be accompanied by headache centered primarily in the nuchal region):
- PCS, Basilar artery thrombosis
- Posterior circulation TIA
- Brainstem/cerebellum hemorrhage
- Vertebral artery dissection
◾️Diagnostic Testing
-
Routine labs/ECG: To exclude hypoglycemia, anemia, or arrhythmia.
-
Neuroimaging (MRI): Indicated if red flags are present, criteria are not fully met, or the diagnosis is uncertain. Do not order CT to “rule out” VM; CT is insensitive for posterior fossa ischemia.
◾️ED Management (Symptomatic Relief)
There are no FDA-approved acute treatments for VM. The 2025 rizatriptan RCT was negative for the primary endpoint at 1 hour, though it showed some benefit for unsteadiness and motion sensitivity at 24 hours. In practice:
-
Vestibular suppressants (meclizine, promethazine) provide symptomatic relief but should be used sparingly (avoid prolonged use due to rehabilitation interference).
-
Antiemetics (ondansetron, metoclopramide) for nausea/vomiting.
-
Referral: Discharge with outpatient Neurology/Headache or Neuro-otology referral for preventive therapy (e.g., flunarizine, beta-blockers, tricyclics, CGRP-targeted therapies)
Posterior Circulation TIA
Posterior circulation TIA (PC-TIA) is not a benign vestibular syndrome; it is a cerebrovascular warning sign with a distinct, high-risk profile. The emergency department approach must balance the recognition of transient focal symptoms with the understanding that the presence of vertebrobasilar stenosis dramatically amplifies the short-term risk of a completed stroke.
Definition:
- PC-TIA is a transient episode of neurological dysfunction caused by focal ischemia in the vertebrobasilar territory, without evidence of acute infarction on imaging. Diagnosis is challenging because symptoms often overlap with anterior circulation events and frequently present non-specifically (e.g., isolated dizziness), leading to misdiagnosis.
- The 2026 AHA/ASA acute ischemic stroke guideline emphasizes that clinical judgment must guide decision-making, but the diagnostic pathway for posterior circulation events remains less standardized than for anterior circulation *.
⚠️ The Core Threat: Vertebrobasilar Stenosis and Early Recurrence
The most critical data for the emergency physician comes from prospective studies of vertebrobasilar stenosis:
-
Prevalence: In consecutive patients with posterior circulation TIA or minor stroke, 26.2% had ≥50% vertebral or basilar stenosis, more than double the prevalence of significant carotid stenosis in anterior circulation events *.
-
90-Day Stroke Risk: With stenosis, the risk of recurrent stroke at 90 days was 22%, and the combined risk of TIA or stroke was 46%. A pooled analysis confirmed this, showing a 24.6% 90-day stroke risk with stenosis versus 7.2% without (OR 4.2) *.
-
Intracranial vs. Extracranial: Intracranial stenosis carries an even higher risk (33% at 90 days) than extracranial stenosis (16.2%) *.
-
Timing: Recurrences cluster within the first 20–30 days after the initial event *. This is not a risk that can wait for an outpatient workup.
🩺 Symptom Profile During the Episode
When a patient is actively symptomatic, the symptoms reflect transient ischemia of the brainstem or cerebellum
- Weakness of the face or limbs.
- Sensory changes (numbness).
- Dysmetria (limb or truncal ataxia).
- Diplopia, dysarthria, dysphagia, or dysphonia.
The presence of any of these focal neurological symptoms alongside vertigo moves the patient from the “uncertain isolated vertigo” category into a clear TIA pathway, warranting the same urgent triage, investigation, and treatment as anterior circulation TIA.
🚨 Critical Rule: Focal Signs = Code Stroke, NOT HINTS EXAM
- When focal brainstem signs (diplopia, dysarthria, dysphagia, dysmetria) or other red flags (hemiparesis, sensory loss) are present alongside vertigo, the diagnosis of a central lesion is already clinically evident. HINTS is not indicated in this scenario—it is designed to differentiate central from peripheral causes in isolated Acute Vestibular Syndrome (AVS), where focal signs are absent. The correct action is immediate stroke pathway activation: non-contrast CT, CTA to identify basilar artery occlusion, and consideration of reperfusion therapy. The 2026 AHA/ASA guideline emphasizes streamlined stroke systems of care with rapid triage and imaging to identify reperfusion candidates.
🚫 The Critical Caveat: HINTS Plus is Invalid for Resolved TIA
- Since HINTS Plus testing should be performed only on patients with ongoing vertigo and nystagmus, HINTS Plus testing is not appropriate for transient ischemic attack patients whose vertigo and/or other posterior circulation symptoms have resolved.
- This is a crucial safety point. If the patient’s vertigo has completely resolved by the time you see them, you cannot use HINTS to “rule out” a central cause. The exam will be normal (because the ischemia is transient), providing false reassurance. In this scenario, the diagnosis relies entirely on the history and vascular imaging (CTA/MRA).
◾️Diagnostic Workup & Risk Stratification
- HINTS Exam (Active Symptoms Only): A 2025 prospective ED study found HINTS had 100% sensitivity and 85.9% specificity for stroke in acute vertigo, significantly outperforming ABCD2 (sensitivity 65.5%). For PC-TIA presenting as isolated dizziness, HINTS is the superior bedside tool *.
- This is the superior bedside tool only when the patient has nystagmus and continuous symptoms, and only when focal signs are absent.
- ABCD2 Score: Its performance in posterior circulation is inconsistent. A 2015 study found ABCD2 performed poorly in posterior circulation (AUC 0.535) compared to anterior circulation (AUC 0.790), with diabetes mellitus being the strongest predictor in PC-TIA. A 2023 study found equivalent predictive ability for both territories, so the evidence is mixed. Do not rely on ABCD2 alone to rule out PC-TIA *.
- Vascular Imaging is Mandatory: GRACE-3 explicitly recommends CTA or MRA if there is concern for TIA in patients with spontaneous episodic vestibular syndrome. For PC-TIA, this means CTA or MRA of the head and neck is the essential next step after HINTS suggests a central cause or the clinical picture is concerning.
- The 2026 AHA/ASA guideline reinforces the importance of identifying large vessel pathology, though its recommendations primarily focus on acute ischemic stroke management rather than TIA specifically *.
- MRI Caveat: DWI-negative stroke is approximately five times more likely in the posterior circulation than in the anterior circulation (OR 5.1, 95% CI 2.3–11.6), underscoring that a negative initial MRI does not exclude a posterior circulation stroke [Edlow et al., 2017]. If initial MRI is negative but suspicion remains high, proceed with vascular imaging or consider repeat imaging.
◾️Management Principles
- Urgent Secondary Prevention
- Given the high recurrence risk, antiplatelet therapy should be initiated promptly. The 2026 AHA/ASA guideline includes updated recommendations on antiplatelet therapy for acute ischemic stroke and TIA, emphasizing that clinical judgment should balance the benefits of early treatment against bleeding risk *.
- Aspirin (or DAPT if high-risk features) should be initiated promptly after hemorrhage is excluded.
- Given the high recurrence risk, antiplatelet therapy should be initiated promptly. The 2026 AHA/ASA guideline includes updated recommendations on antiplatelet therapy for acute ischemic stroke and TIA, emphasizing that clinical judgment should balance the benefits of early treatment against bleeding risk *.
- Targeting Stenosis
- If significant vertebrobasilar stenosis is identified, aggressive medical management (including statins and antiplatelets) is crucial. The role of stenting remains under investigation, but identifying high-risk patients with compromised distal flow is important for future interventional or medical therapies *.
- Admission vs. Rapid Outpatient Workup
- All patients with TIA require urgent evaluation. PC-TIA patients with vascular risk factors or stenosis often warrant admission for monitoring and workup, while low-risk patients may be suitable for rapid outpatient evaluation.
Posterior Circulation Stroke (PCS)
Ischemic strokes comprise 87% of all strokes, and posterior circulation stroke (PCS) accounts for approximately 20–25% of all acute ischemic strokes. It remains a diagnostic challenge in the acute phase compared to anterior circulation stroke (ACS) because patients often present late with non-specific and fluctuating symptoms. This puts them at increased risk of being misdiagnosed or missed in the emergency department.
◾️Risk Factors
Risk Factors: Anterior vs. Posterior Circulation Stroke (Click to Expand)
◾️Mechanism of Stroke
Mechanisms of Stroke: Anterior vs. Posterior Circulation (Click to Expand)
• Genetics: RNF213 variant is found in anterior intracranial atherosclerosis.
• Less common diseases: Fibromuscular Dysplasia (FMD), MELAS (often occipital infarcts), Dolichoectasia (basilar artery), and Reversible Cerebral Vasoconstriction Syndrome (RCVS).
Posterior Circulation Vascular Territory and Neuroanatomy
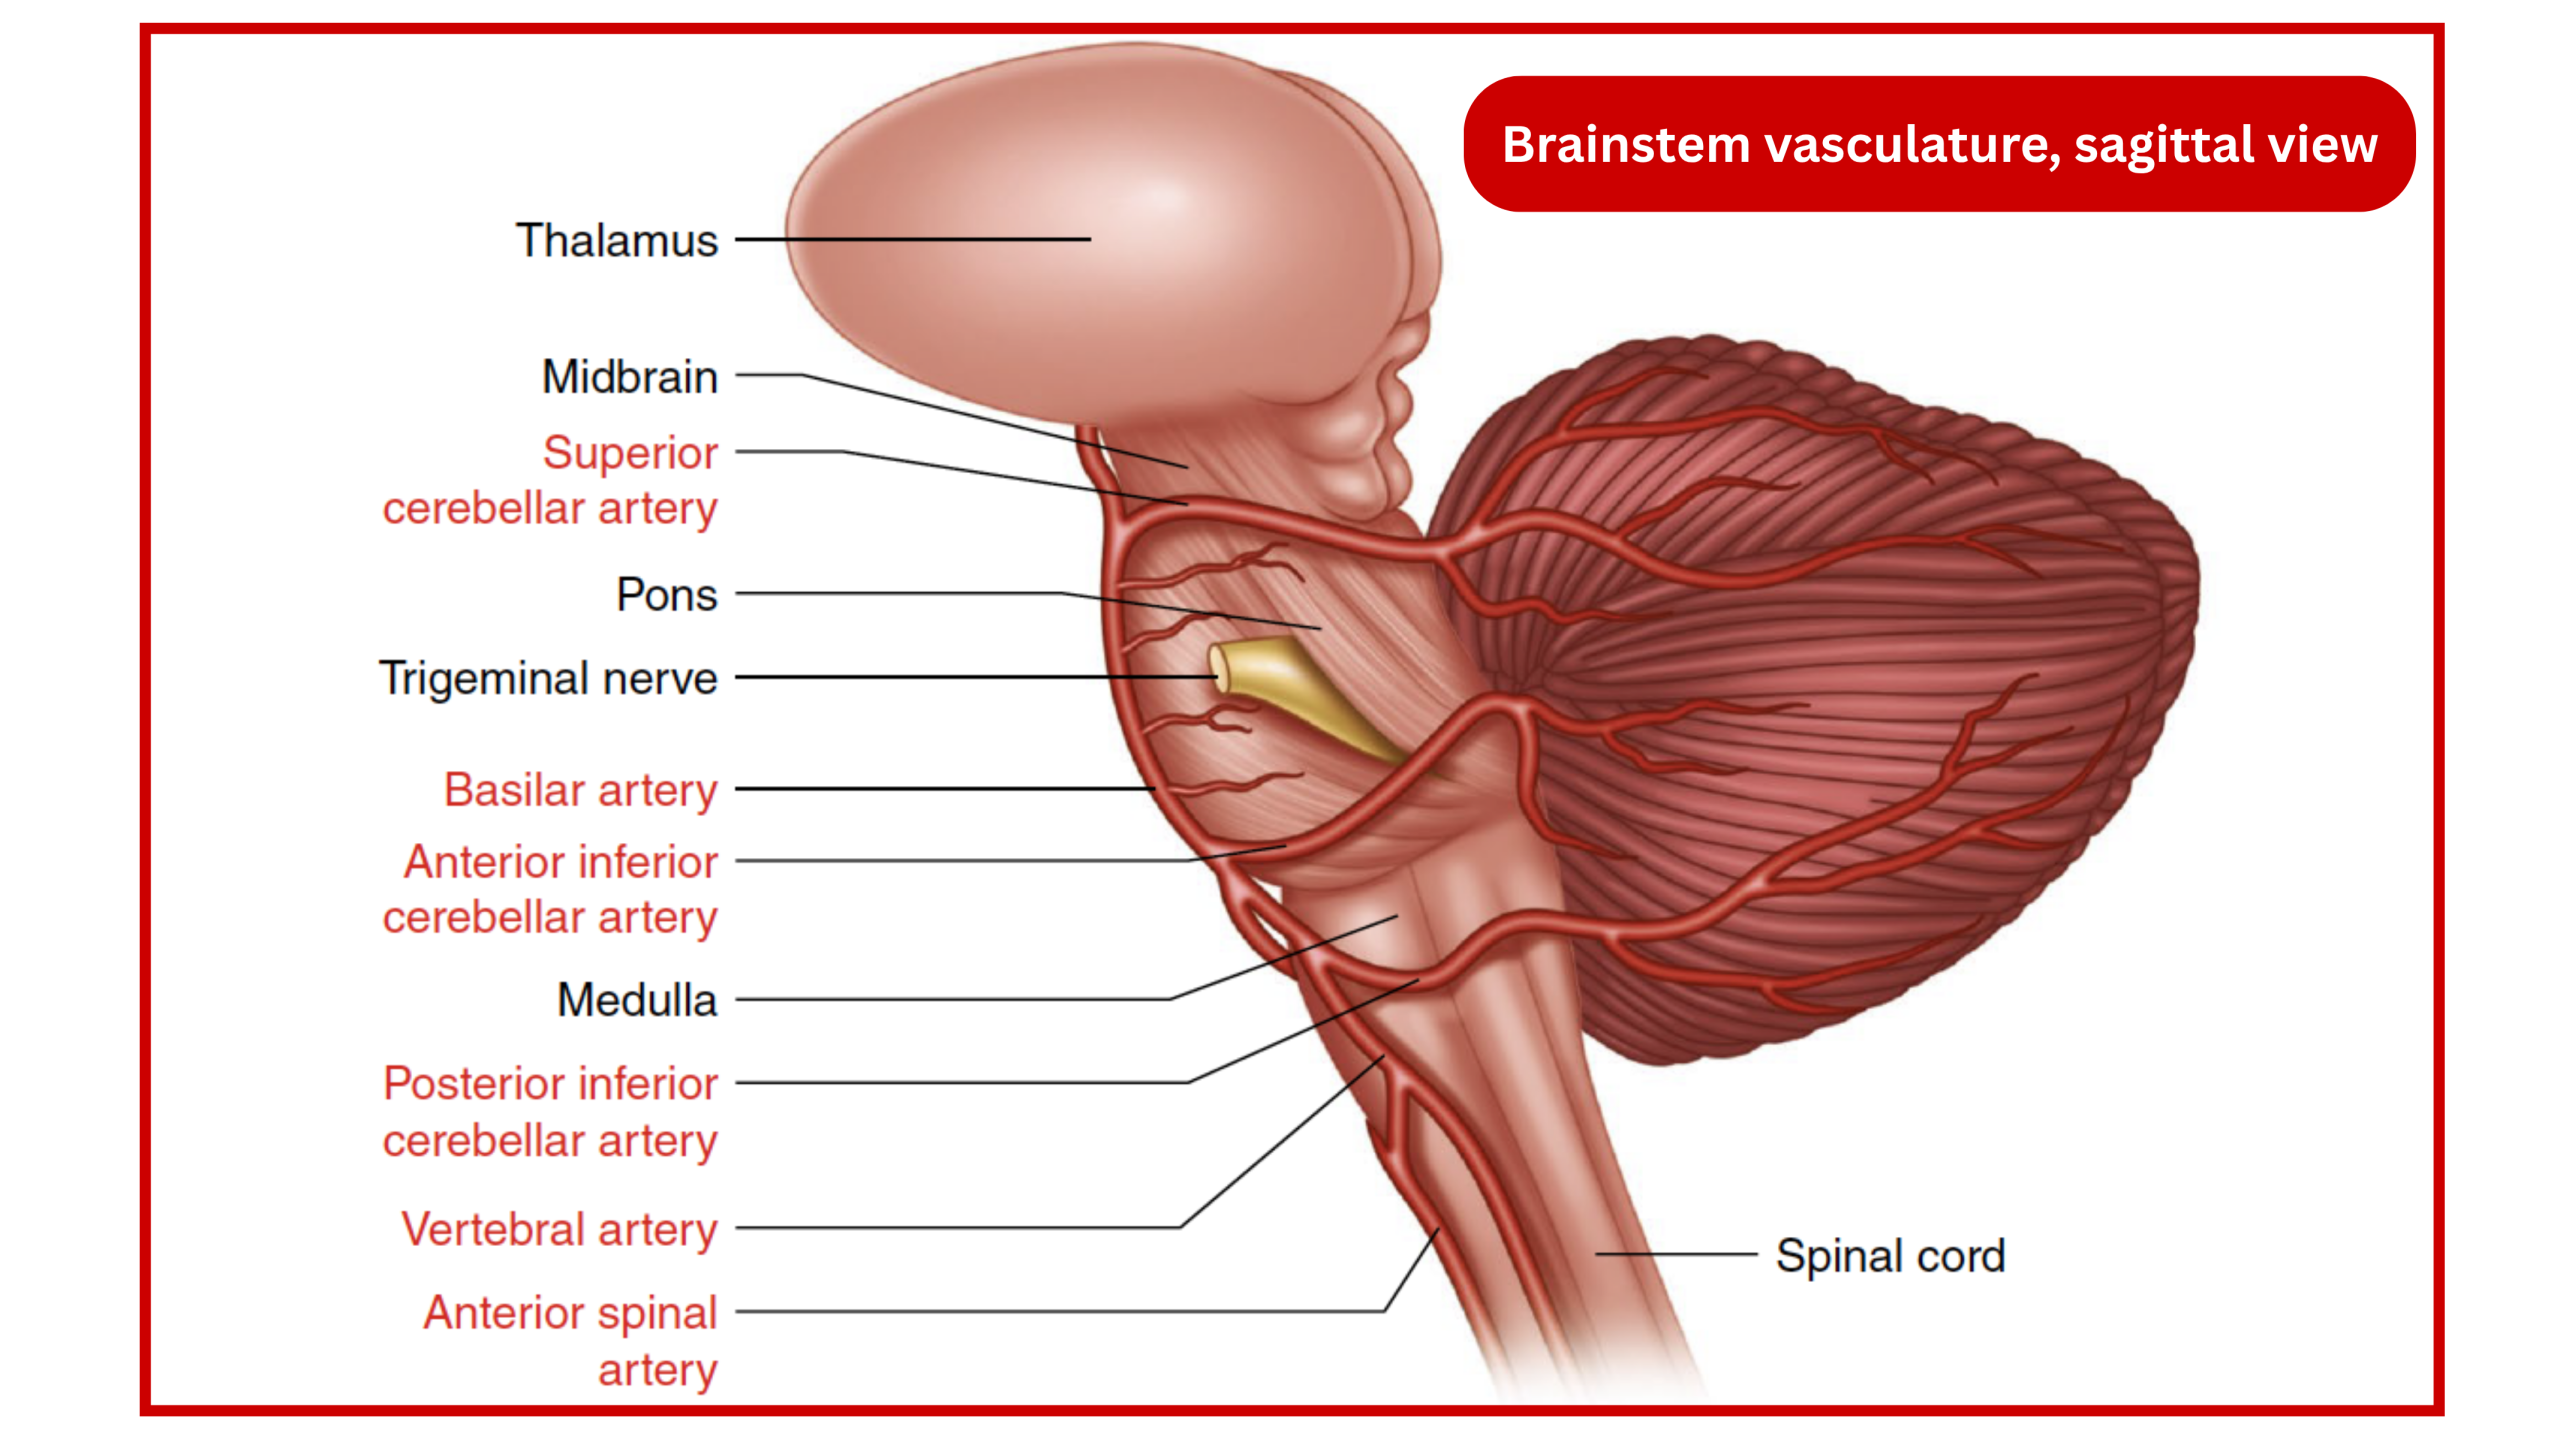
◾️The Vascular territory and correlated neuroanatomy of posterior circulation is illustrated in the following Carousel👇
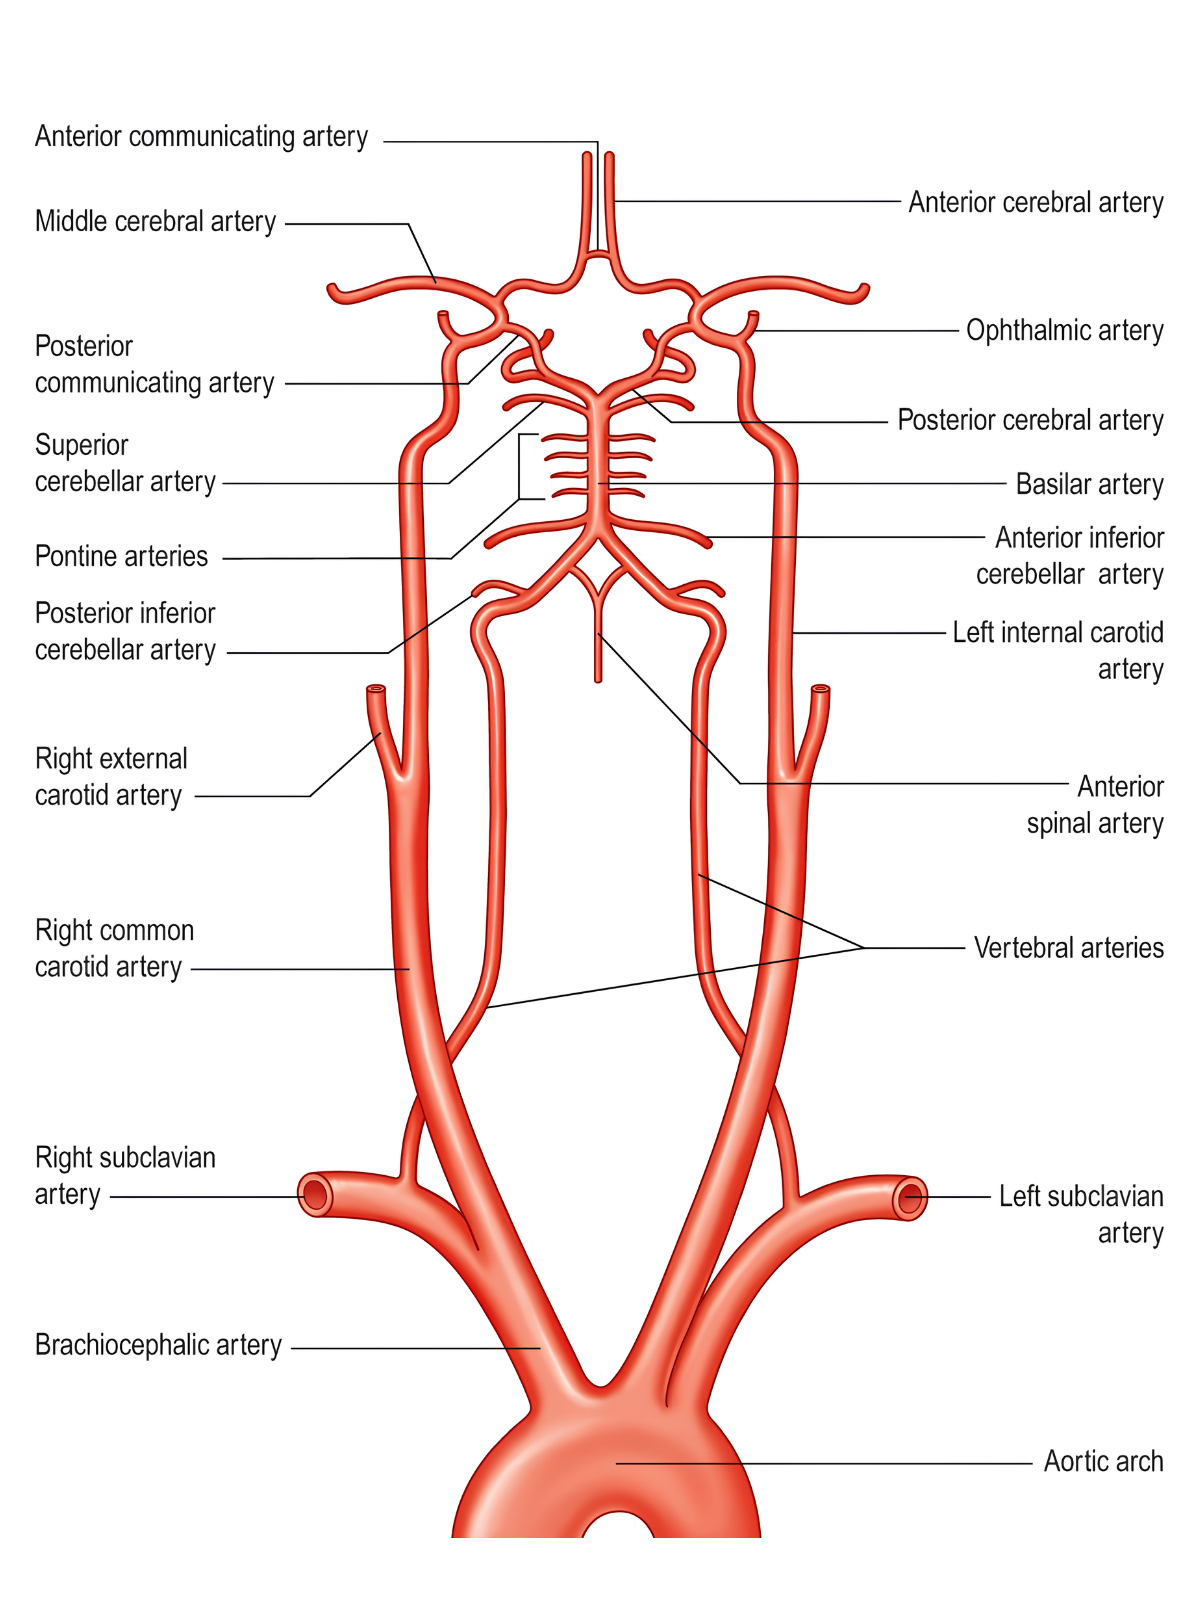
The following table provides a systematic anatomical review of the posterior circulation, detailing the arterial branches and their specific vascular territories to facilitate accurate lesion localization.
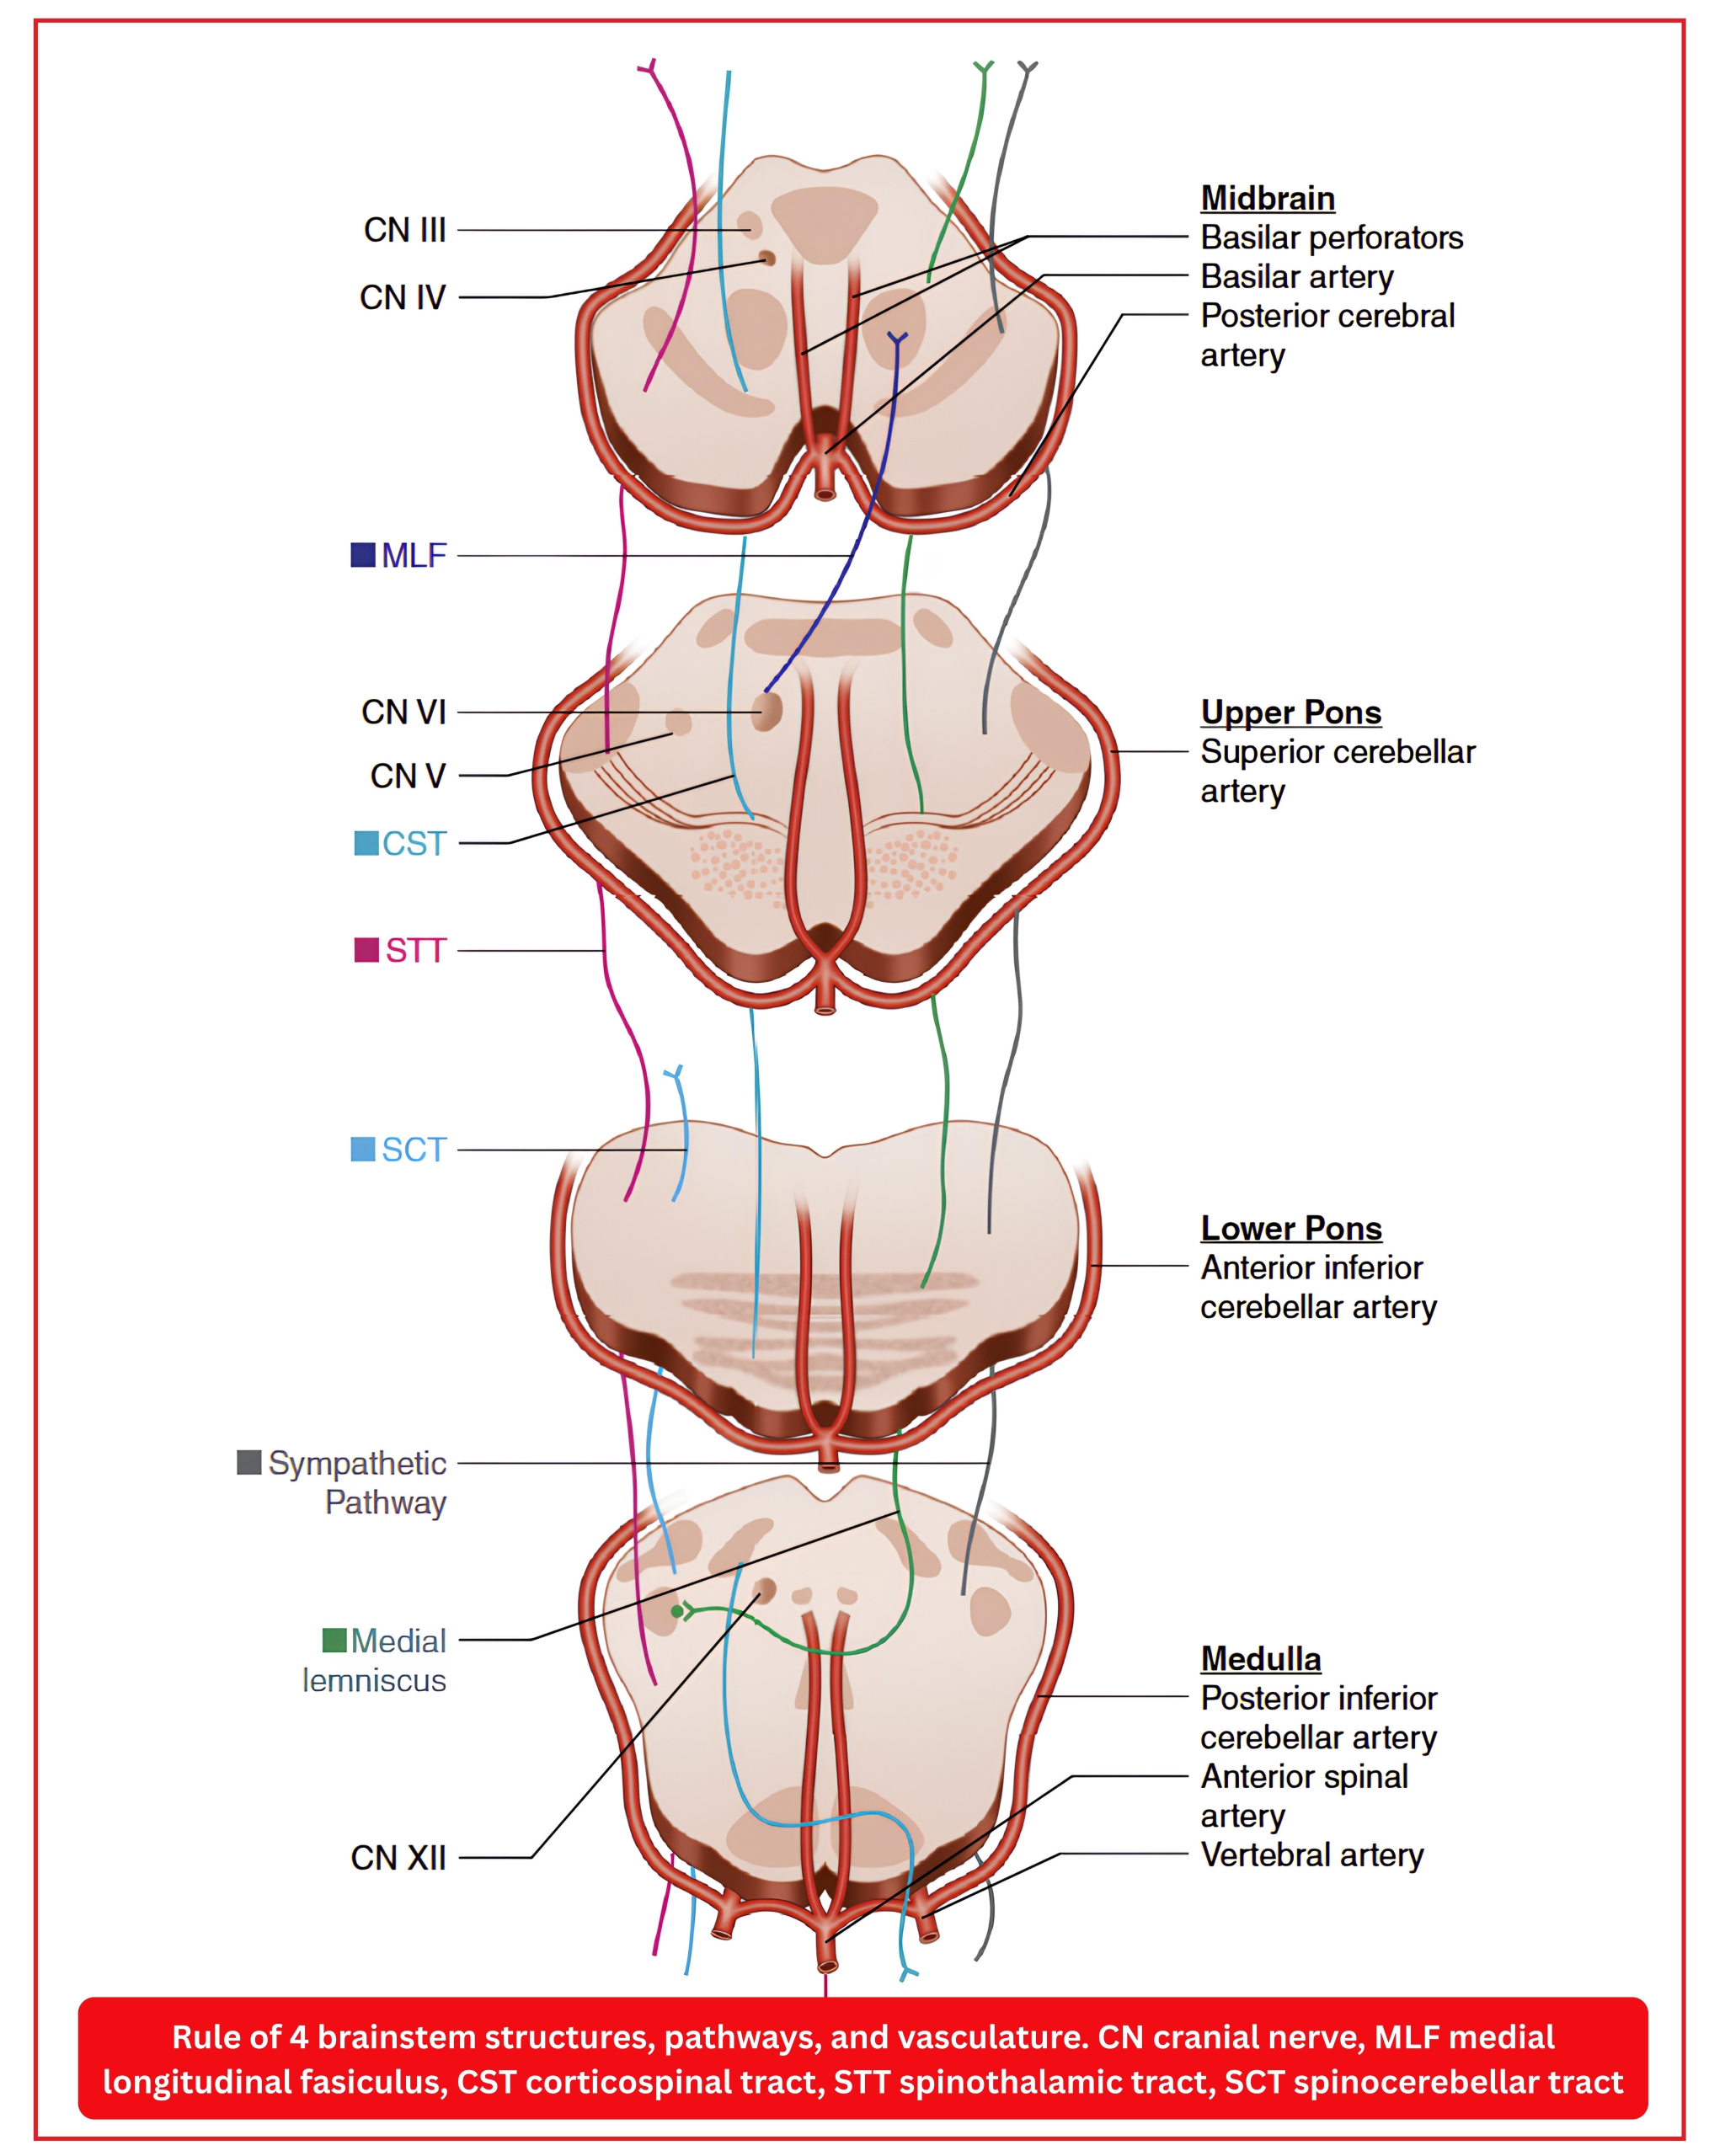
Clinical Presentation
◾️PCS may involve the brainstem, cerebellum, thalamus, or the occipital cortex *.
- Dizziness and vertigo are among the most common and clinically challenging symptoms, and may occur in isolation or alongside symptoms including headache, nausea and vomiting, visual disturbance, sensory symptoms, or confusion.
◾️Most common clinical symptoms of PCS
- Dizziness (47%) *
- Nausea and Vomiting (41%) *
- Unilateral limb weakness (41%)
- Dysarthria (31%)
- Headache (28%)
- Hiccups (25%)
◾️Most common signs of PCS
- Unilateral limb weakness (48%) *
- Dysarthria (48%)
- Gait ataxia (31%)
- Unilateral limb ataxia (30%)
- Nystagmus (24%)
- Visual field loss
- (Subtle) Ocular motor abnormalities including nystagmus
- Altered consciousness
- Other focal neurological deficits
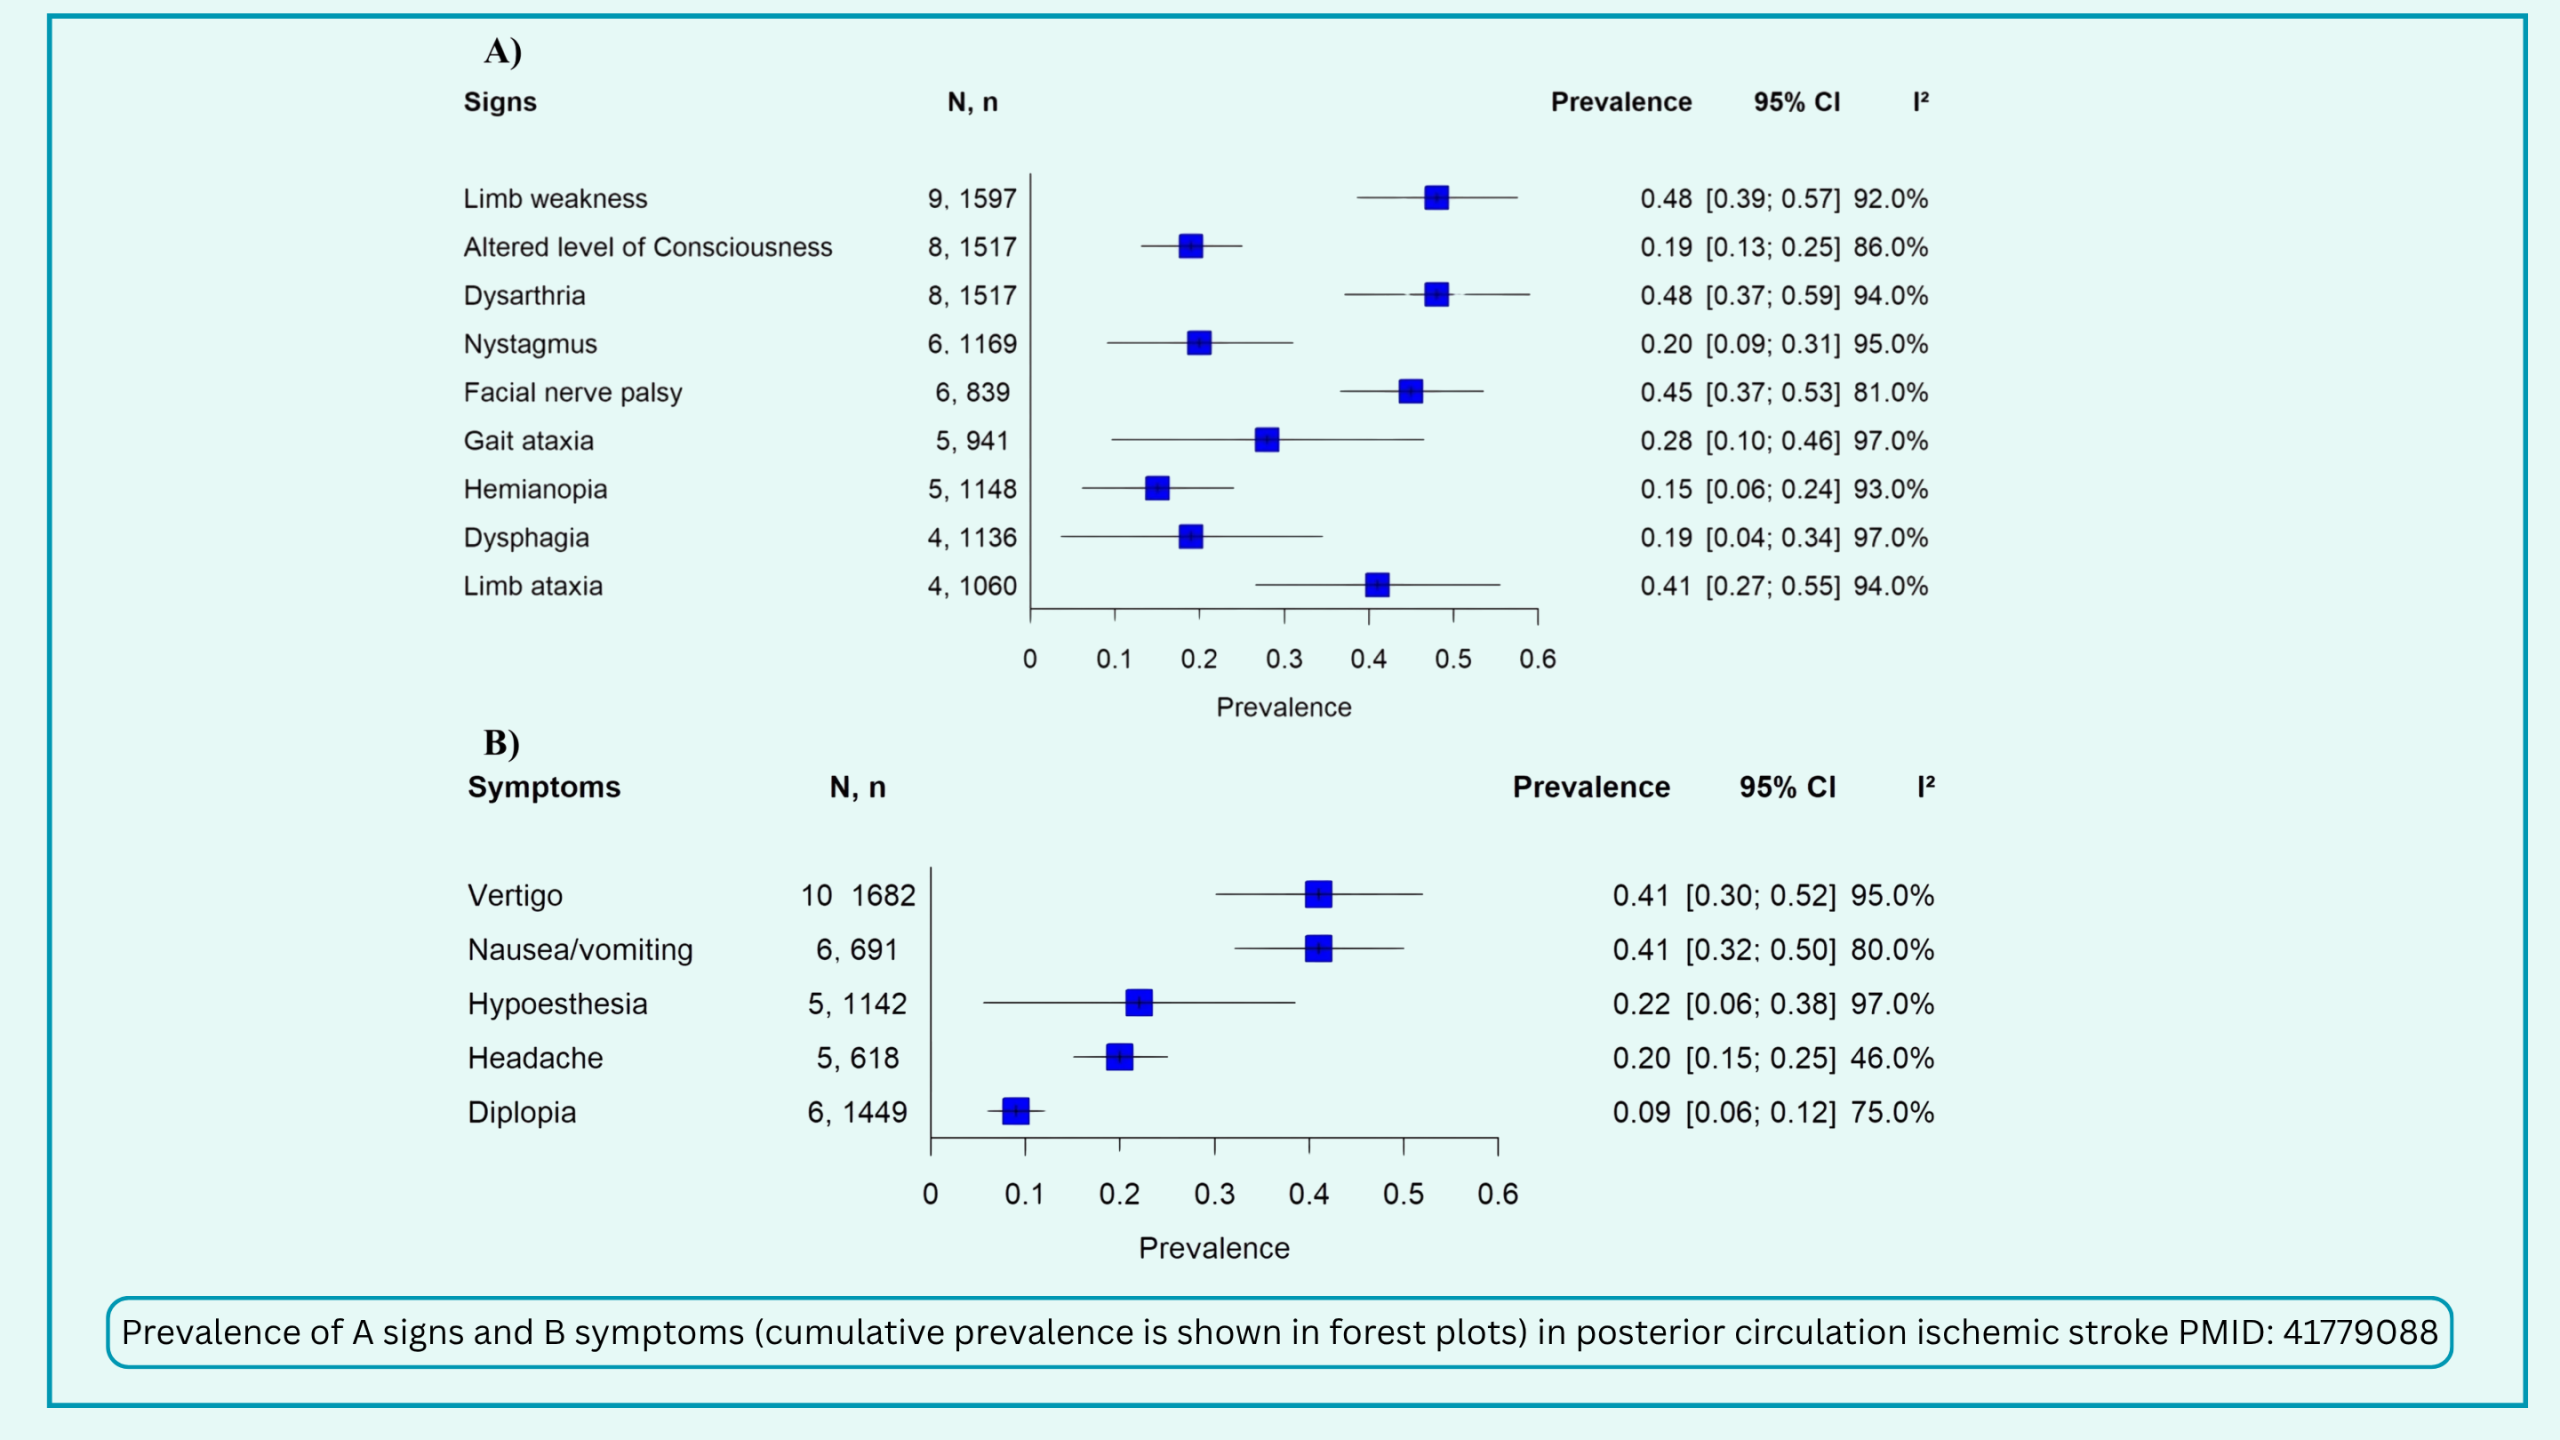
Posterior circulation stroke syndromes
◾️The clinical syndrome depends largely on the vascular territory affected (🎞️Carousel). The more comprehensive clinical syndromes of PCS are listed in the following table.
💡 The Bottom Line for the ED:
-
Vertigo + hearing loss = Think AICA.
-
Vertigo + crossed sensory signs + Horner’s = Think PICA (Wallenberg’s).
-
Vertigo + bilateral signs or “herald” hemiparesis = Think Basilar artery (a true emergency).
-
Sudden-onset “seizure-like” posturing + cranial nerve deficits = Suspect “Top of the Basilar” syndrome
Cerebellar stroke
While peripheral vertigo is common, central lesions involving the cerebellum can present with overlapping dizziness and subtle exam findings. Recognizing the hallmark ipsilateral ataxia and specific vascular territories of the PICA, AICA, and SCA syndromes is critical in the emergency department to rapidly differentiate benign vertigo from life-threatening posterior circulation strokes.
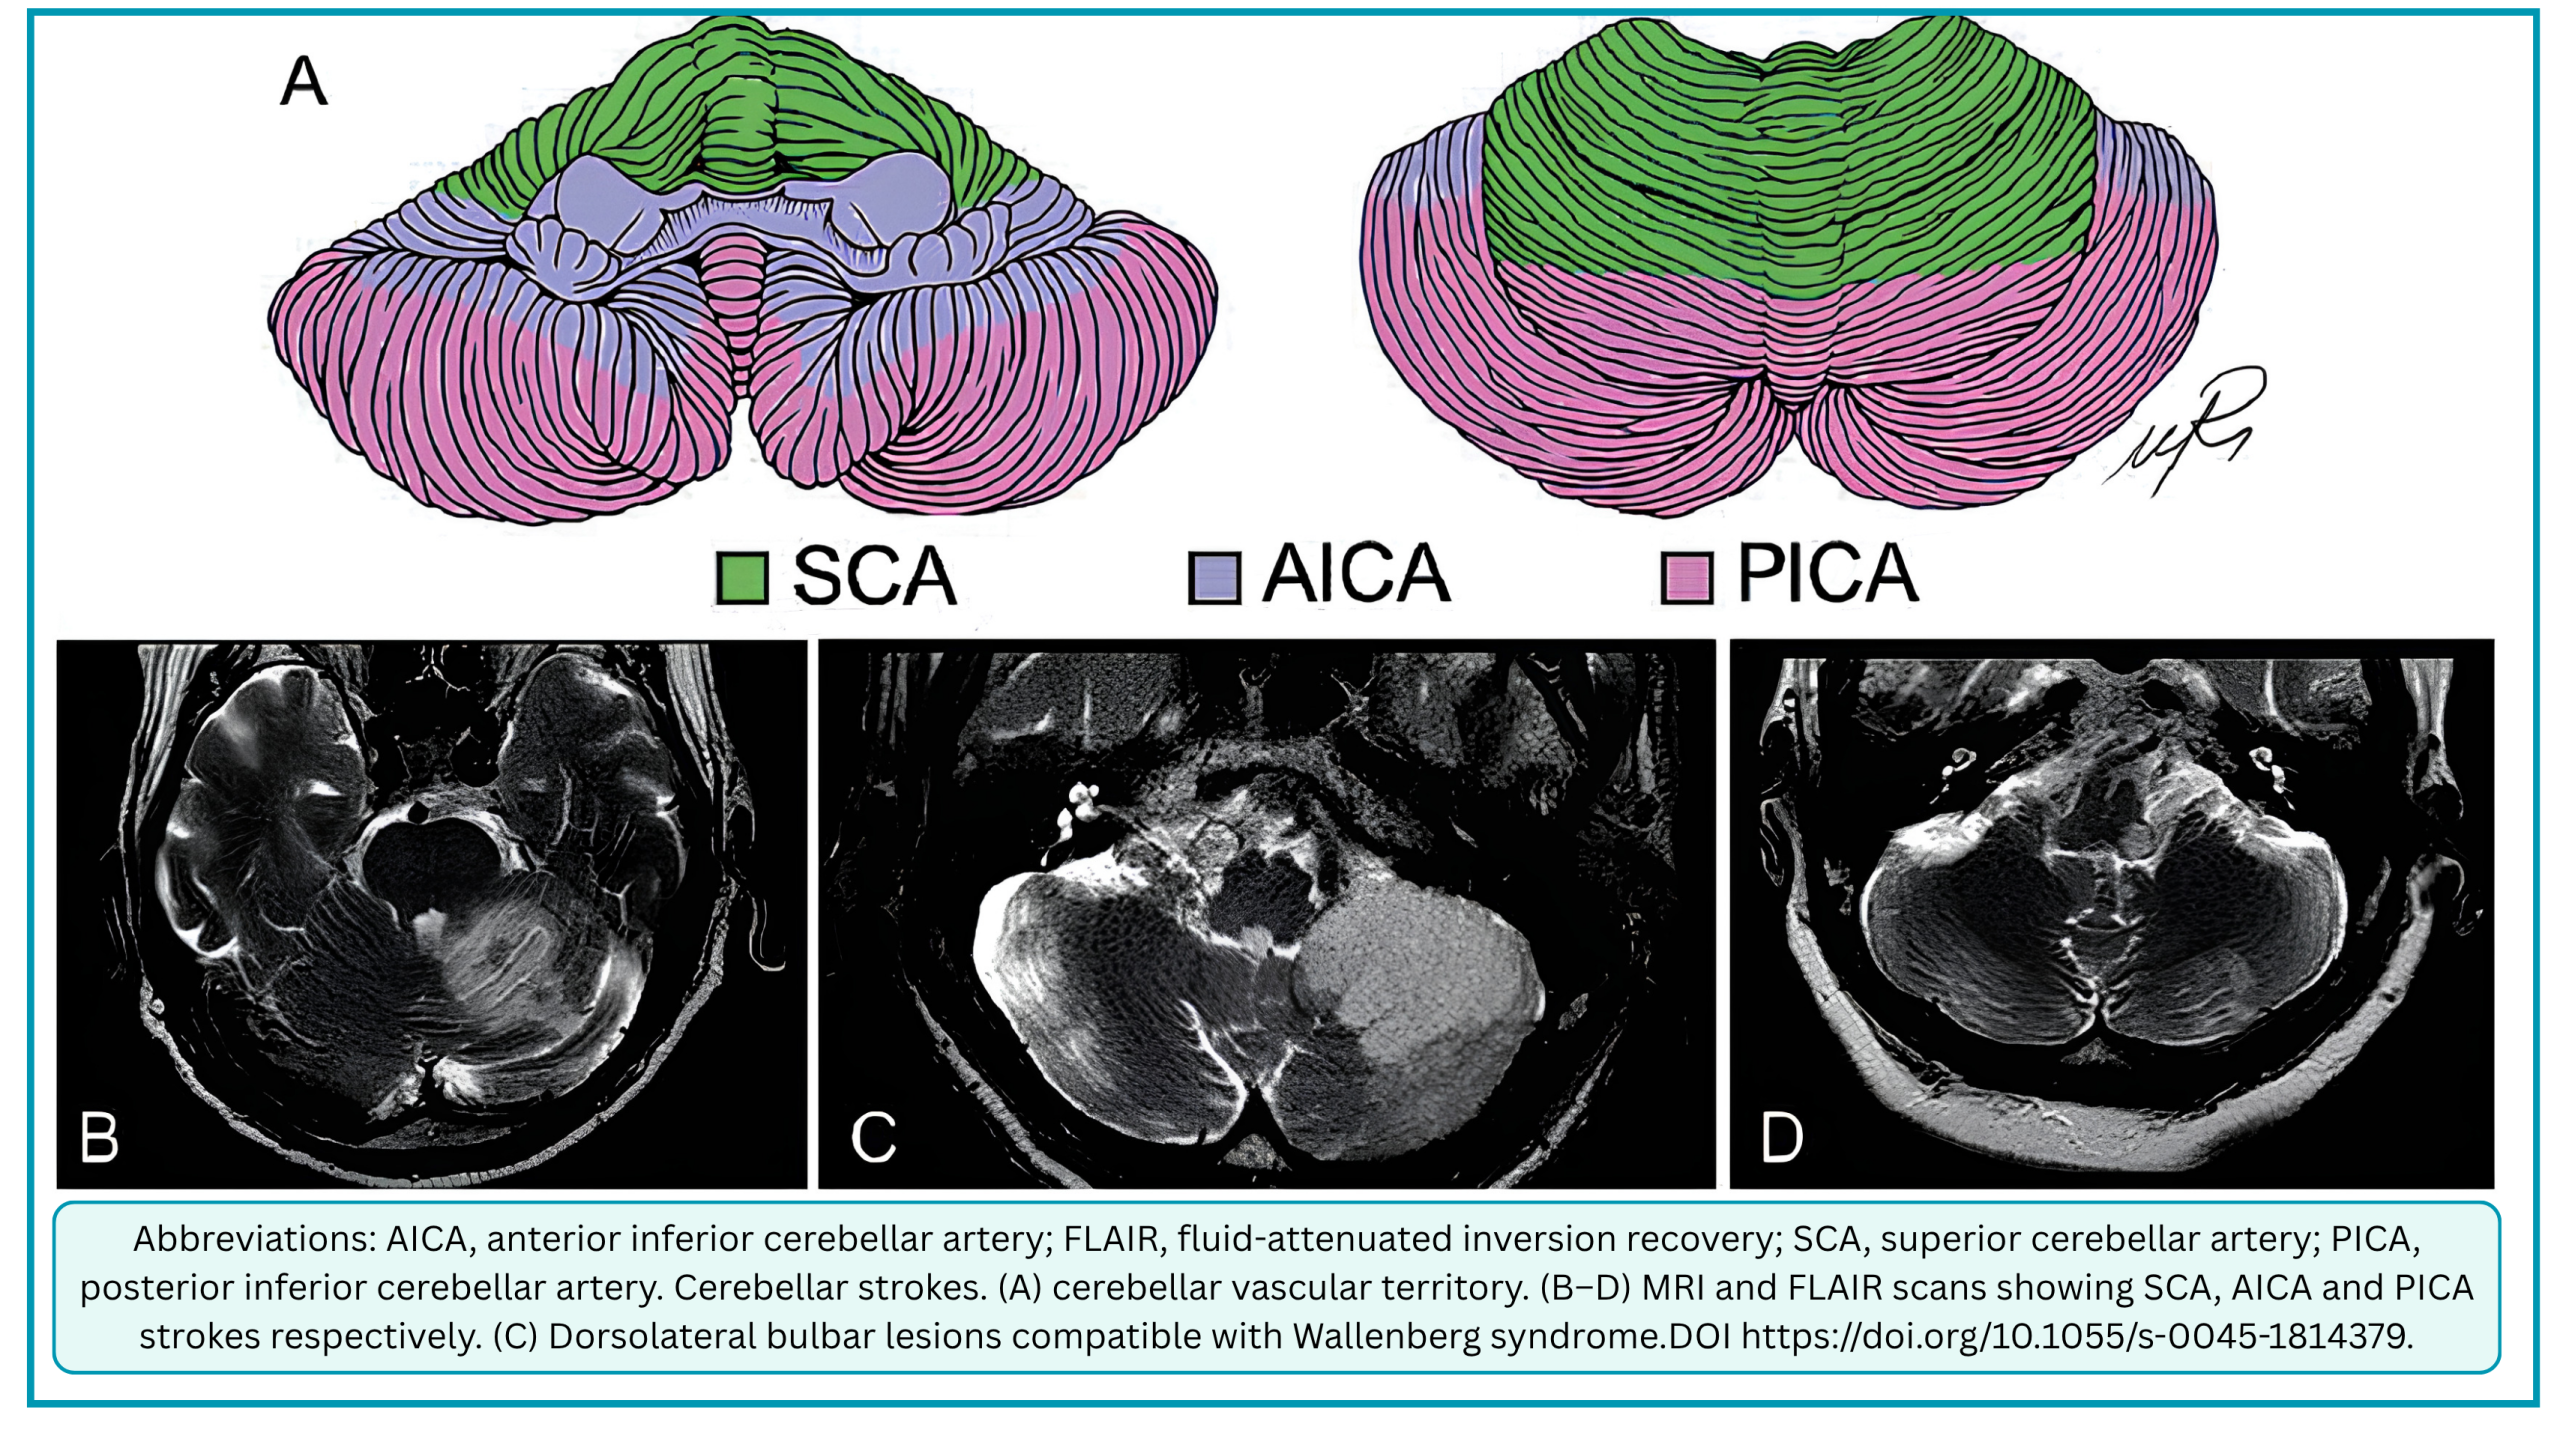
PCS With Dizziness
😵💫 The Most Common Syndromes Presenting With Dizziness Are PICA and AICA Stroke.
- PICA strokes are among the most common vascular causes of dizziness and vertigo *.
- Medial PICA territory infarction often presents with isolated dizziness or vertigo, meaning dizziness or vertigo without other obvious central findings such as limb weakness or dysarthria *, *.
- ⚠️This is the classic “stroke mimic” of vestibular neuritis (isolated dizziness, normal HIT, no other neuro signs) *.
- Lateral PICA territory involvement, by contrast, typically produces crossed brainstem findings (ipsilateral cranial nerve signs + contralateral sensory/motor deficits) *. They present with classic Wallenberg syndrome signs (crossed sensory, Horner’s, dysphagia).
- Medial PICA territory infarction often presents with isolated dizziness or vertigo, meaning dizziness or vertigo without other obvious central findings such as limb weakness or dysarthria *, *.
- AICA infarction should be suspected when dizziness or vertigo is accompanied by unilateral hearing loss *.
👣 SCA presents more with cerebellar signs (ataxia, dysarthria) rather than isolated vertigo.
Table 1. Affected Anatomical Structures and Typical Clinical Findings by Vascular Territory in PCS Presenting with Acute Dizziness and Vertigo (Click to Expand)
Reference: Seetge J, Tarnutzer AA. Diagnostic challenges in posterior circulation ischemic stroke presenting with acute dizziness and vertigo. Front Neurol 2026;17:1960712. doi: 10.3389/fneur.2026.1960712. Table adapted from Table 1 of the article.
Treatment
BPPV
- Patients who are diagnosed with pc-BPPV can be treated with the Epley maneuver during their ED visit.
- Patients with hc-BPPV are treated with the Gufoni maneuver.
- Since the episodes of BPPV typically last 15 to 30 seconds, do not prescribe vestibular suppressants.
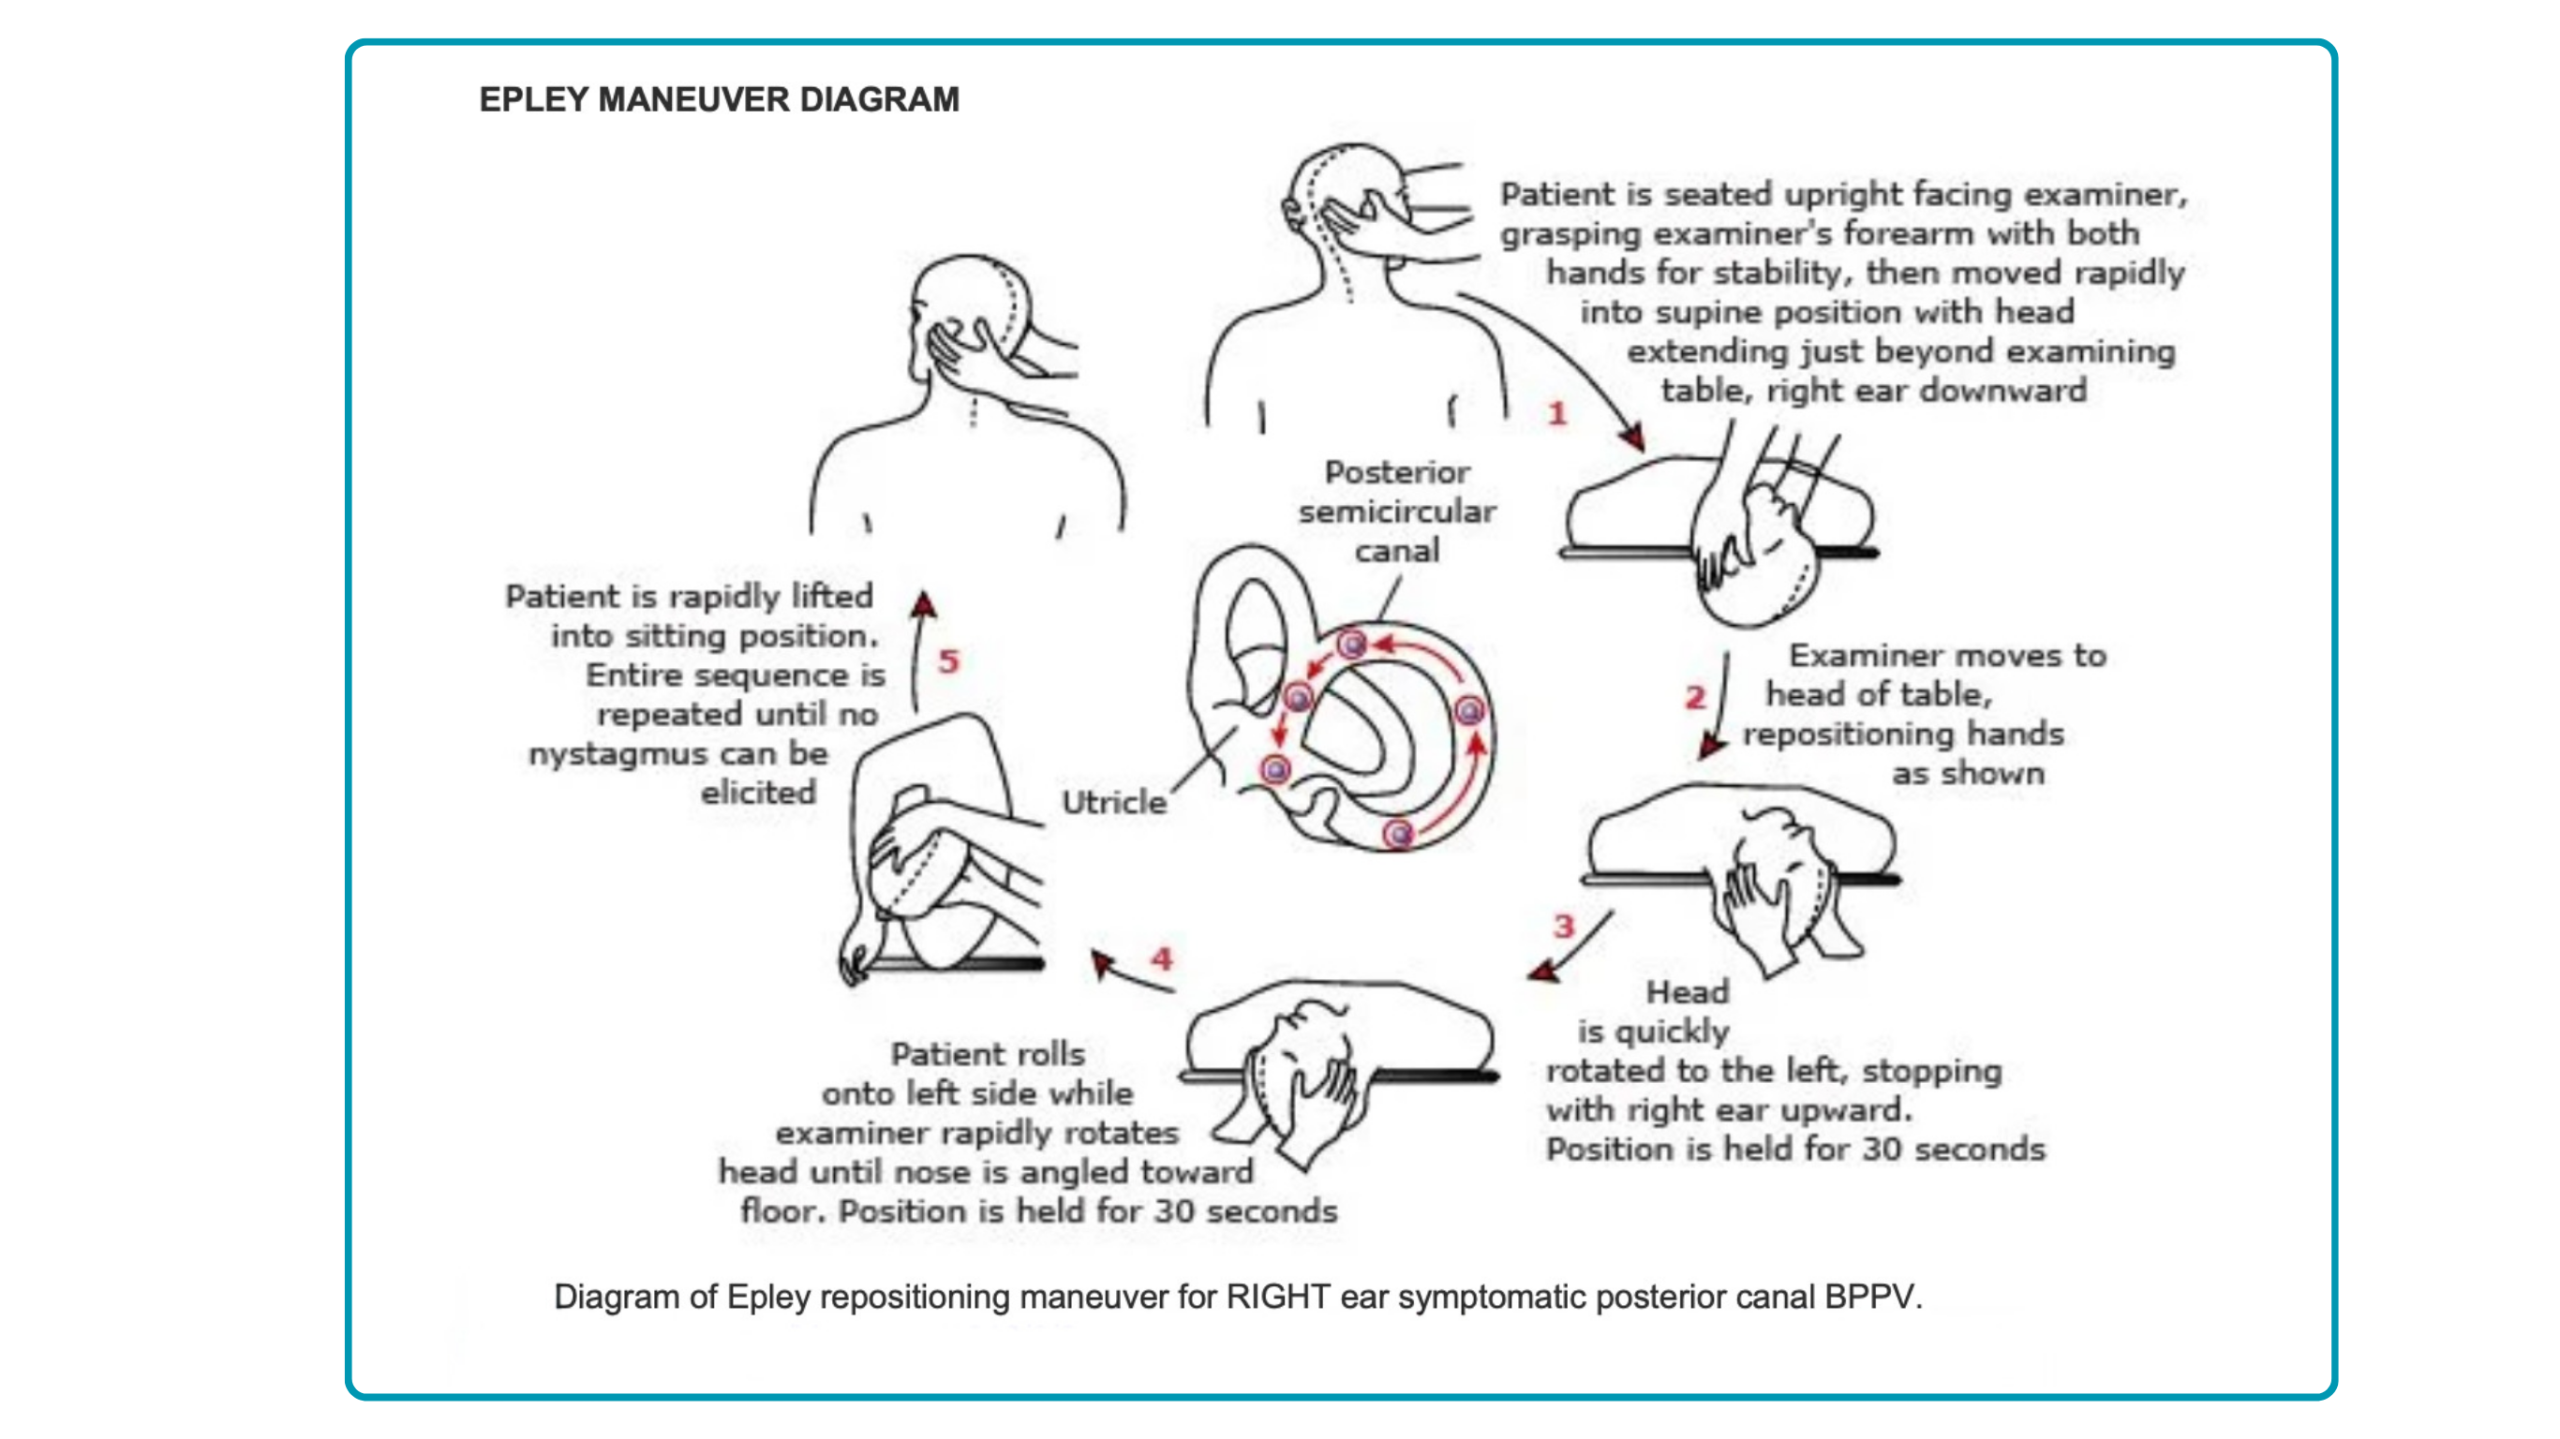
📝 Click to read the clinical description
For horizontal and anterior canal variants, the following videos demonstrate the corresponding canal-specific repositioning maneuvers, which differ fundamentally from the Epley maneuver in both technique and biomechanical rationale 👇
Medication
Short-term pharmacotherapy is a mainstay for symptom control in peripheral vertigo (except BPPV) and specific central conditions. The goal is rapid symptom relief, but medications must be withdrawn as early as possible to facilitate central vestibular compensation.
-
First-Line (Symptom Control): Anticholinergics (e.g., transdermal scopolamine) and H1-antihistamines (meclizine, diphenhydramine) reduce vertigo via anticholinergic effects.
-
Second-Line (Refractory/Rescue): Calcium channel blockers (cinnarizine) for refractory vertigo. Antidopaminergic neuroleptics (promethazine, metoclopramide) for nausea/vomiting. Ondansetron (5-HT3 antagonist) is useful for intractable vertigo in brainstem/MS disorders.
-
Adjuncts & Specifics: Benzodiazepines (short-term, <3 days) for acute vestibular neuritis; Betahistine for Ménière’s (facilitates compensation); Gabapentin for MS-associated dizziness.
-
Critical Cautions: Avoid combinations of overlapping anticholinergic and antidopaminergic drugs. Do not use antivertigo medications for non-vertiginous disequilibrium of aging or orthostatic dizziness. Withdraw all symptomatic treatments as soon as possible.
💊 Pharmacology of Vertigo and Dizziness (Click to Expand)
Disposition
🏥 Admission Criteria
- AVS with concerning findings
- Admit patients with a concerning HINTS exam, focal neurologic deficits, or an inability to ambulate independently (note: early DWI-MRI has a 20% false-negative rate for posterior circulation stroke).
- Serious underlying causes
- Admit for metabolic, infectious, or cardiogenic etiologies as clinically indicated.
- Intractable symptoms
- Observe until vomiting is controlled. Patients must tolerate oral liquids and ambulate independently before discharge; if they cannot walk, admit to exclude a central cause.
🚶➡️Discharge Criteria
- AVS (reassuring HINTS)
- Discharge if no focal deficits and steady gait. Provide reassurance, a short course (3–4 days) of vestibular suppressants, consider oral steroids, and arrange ENT/Neurology follow-up (plus PT if feasible).
- s-EVS (resolved symptoms)
- Refer for outpatient evaluation. If posterior circulation TIA is suspected, initiate a rapid standard TIA workup (vessel imaging, cardioembolic source) and consider antiplatelets + neurology referral, as stroke risk peaks in the first 48 hours.
- t-EVS (BPPV)
- Treat with a targeted canalith repositioning maneuver. If untreated (due to lack of training), discharge is safe only if there is no downbeat nystagmus, no central findings, and the patient walks independently.
- t-EVS (orthostatic hypotension)
- Discharge is safe if symptoms are controlled in the ED and the underlying cause is not serious.
Case Resolution and Clinical Pearls
⚡️RECAP
- The description of symptoms quality alone by patients (Dizziness, vertigo, etc.) is unreliable for risk stratification.
- Movement making dizziness worse does not prove a peripheral cause. Central causes, including stroke, can worsen with movement too. What matters is whether head movement triggers the symptoms in the first place, not whether it merely aggravates them.
- Acute vestibular syndrome is defined as sudden onset, continuous vertigo lasting > 24 h with associated nystagmus, nausea, vomiting, and postural instability, all of which are worsened with head movement.
- Note that absence of nystagmus in patients who otherwise meet AVS criteria doesn’t rule out a central cause.
- Almost 20% of patients who meet the definition of acute vestibular syndrome harbor posterior circulation infarction.
- HINTS is ONLY for Spontaneous Nystagmus: Do not use HINTS in patients without nystagmus or those with triggered nystagmus (like BPPV). It will be inaccurate.
- HINTS Exam: Sensitivity: 92.9%, Specificity: 83.4% when performed correctly by a trained clinician.
- In AVS Patients: Sensitivity is 93.1%
- The diagnostic accuracy of HINTS drops significantly if performed by untrained clinicians
- It has higher diagnostic accuracy for stroke than an early MRI-DWI in the first 24–48 hours. Early MRI was falsely negative in 15% of strokes (sensitivity 85.1%), whereas HINTS sensitivity was 95.3% *.
📽️Media
◾️Localizing Forms of Nystagmus
◾️HINTS Exam
◾️Central HINTS (With an Abnormal Head Impulse Sign) in the Acute Vestibular Syndrome
◾️Wallenberg Syndrome in MS
◾️HINTS Exam and Saccadic Dysmetria in Lateral Medullary Stroke
📝 Click to read the full clinical vignette and findings
 Going further
- Digital Library Collection
- Nystagmus (Eye Wiki)
- Peter Johns (YouTube Channel)
- The HINTS+ Exam Masterclass
 Guidelines
📚 References
1. PMID: 37166022. Edlow JA, et al. Guidelines for reasonable and appropriate care in the emergency department 3 (GRACE-3): Acute dizziness and vertigo in the emergency department. Acad Emerg Med. 2023 May;30(5):442-486. doi: 10.1111/acem.14728.
2. PMID: 39973600. Kaski D, et al. The International Classification of Vestibular Disorders: Achievements, challenges, and future directions. J Vestib Res. 2025 May;35(3):105-112. doi: 10.1177/09574271251313803. Epub 2025 Jan 8.
3. PMID: 29395695. Edlow JA, Gurley KL, Newman-Toker DE. A New Diagnostic Approach to the Adult Patient with Acute Dizziness. J Emerg Med. 2018 Apr;54(4):469-483. doi: 10.1016/j.jemermed.2017.12.024. Epub 2018 Feb 1.
4. PMID: 40308011. Lee SU, Tarnutzer AA. Usefulness of Nystagmus Patterns in Distinguishing Peripheral From Central Acute Vestibular Syndromes at the Bedside: A Critical Review. J Clin Neurol. 2025 May;21(3):161-172. doi: 10.3988/jcn.2025.0105.
5. PMID: 31256095. Eggers SDZ, Bisdorff A, von Brevern M, Zee DS, Kim JS, Perez-Fernandez N, Welgampola MS, Della Santina CC, Newman-Toker DE. Classification of vestibular signs and examination techniques: Nystagmus and nystagmus-like movements. J Vestib Res. 2019;29(2-3):57-87. doi: 10.3233/VES-190658
6. PMID: 42766300. Sars C, Lelli D, Tse D, Johns P. When to Use the HINTS Examination in Patients With Dizziness: A Review. JAMA Neurol. 2026 Sep 21. doi: 10.1001/jamaneurol.2026.2942. Epub ahead of print.
7. PMID: 41770418. Coban FA, Tarnutzer AA. The epidemiology and clinical presentation of acute vestibular syndromes: a systematic review of the literature. J Neurol. 2026 Mar 2;273(3):173. doi: 10.1007/s00415-026-13720-5.
8. PMID: 41263134. Kaski D. Acute vertigo: stroke or not? Curr Opin Neurol. 2026 Feb 1;39(1):65-71. doi: 10.1097/WCO.0000000000001444. Epub 2025 Nov 24.
9. PMID: 30637123. Kattah JC. Use of HINTS in the acute vestibular syndrome. An Overview. Stroke Vasc Neurol. 2018 Jun 23;3(4):190-196. doi: 10.1136/svn-2018-000160.
10. PMID: 24920847. Saber Tehrani AS, Kattah JC, Mantokoudis G, Pula JH, Nair D, Blitz A, Ying S, Hanley DF, Zee DS, Newman-Toker DE. Small strokes causing severe vertigo: frequency of false-negative MRIs and nonlacunar mechanisms. Neurology. 2014 Jul 8;83(2):169-73. doi: 10.1212/WNL.0000000000000573. Epub 2014 Jun 11.
11. PMID: 37038843. Tarnutzer AA, et al. Impact of Clinician Training Background and Stroke Location on Bedside Diagnostic Test Accuracy in the Acute Vestibular Syndrome – A Meta-Analysis. Ann Neurol. 2023 Aug;94(2):295-308. doi: 10.1002/ana.26661. Epub 2023 Apr 27.
12. PMID: 28248609. Bhattacharyya N, et al. Clinical Practice Guideline: Benign Paroxysmal Positional Vertigo (Update). Otolaryngol Head Neck Surg. 2017 Mar;156(3_suppl):S1-S47. doi: 10.1177/0194599816689667.
13. PMID: 33283066. Carvalho V, Cruz VT. Clinical presentation of vertebrobasilar stroke. Porto Biomed J. 2020 Nov 24;5(6):e096. doi: 10.1097/j.pbj.0000000000000096.
14. PMID: 41731878. Liu M, Dai Y, Qiu T, Qiu X, Li T, Li Z, Le W. The clinical features, imaging profiles, and management strategies of cerebellar infarction: an update. Int J Surg. 2026 Feb 1;112(2):4850-4860. doi: 10.1097/JS9.0000000000003939. Epub 2025 Nov 17.
15. PMID: 19797177. Lee H, Kim JS, Chung EJ, Yi HA, Chung IS, Lee SR, Shin JY. Infarction in the territory of anterior inferior cerebellar artery: spectrum of audiovestibular loss. Stroke. 2009 Dec;40(12):3745-51. doi: 10.1161/STROKEAHA.109.564682. Epub 2009 Sep 24.
16. PMID: 12805095. Kim JS. Pure lateral medullary infarction: clinical-radiological correlation of 130 acute, consecutive patients. Brain. 2003 Aug;126(Pt 8):1864-72. doi: 10.1093/brain/awg169. Epub 2003 May 21.
17. PMID: 42618916. Zhang S, Xie Y, Hu Z, Chen Y, Su Y, Ma Z. Recurrent brief positional vertigo as the initial presentation of medial branch of the posterior inferior cerebellar artery territory cerebellar infarction: a case report. BMC Neurol. 2026 Aug 19;26(1):526. doi: 10.1186/s12883-026-05299-1.
18. PMID: 34630309. Bhandari A, Bhandari R, Kingma H, Strupp M. Diagnostic and Therapeutic Maneuvers for Anterior Canal BPPV Canalithiasis: Three-Dimensional Simulations. Front Neurol. 2021 Sep 24;12:740599. doi: 10.3389/fneur.2021.740599.
19. PMID: 38823940. Expert Panel on Neurological Imaging; Wang LL, et al. ACR Appropriateness Criteria® Dizziness and Ataxia: 2023 Update. J Am Coll Radiol. 2024 Jun;21(6S): S100-S125. doi: 10.1016/j.jacr.2024.02.018.
20. PMID: 37738525. Nikles F, et al. Do monosymptomatic stroke patients with dizziness present a vestibular syndrome without nystagmus? An underestimated entity. Eur J Neurol. 2024 Jan;31(1):e16066. doi: 10.1111/ene.16066. Epub 2023 Sep 22.
21. PMID: 32094268. Johns P, Quinn J. Clinical diagnosis of benign paroxysmal positional vertigo and vestibular neuritis. CMAJ. 2020 Feb 24;192(8):E182-E186. doi: 10.1503/cmaj.190334.
22. PMID: 41770418. Coban FA, Tarnutzer AA. The epidemiology and clinical presentation of acute vestibular syndromes: a systematic review of the literature. J Neurol. 2026 Mar 2;273(3):173. doi: 10.1007/s00415-026-13720-5.
23. PMID: 41324222. Villar-Martinez MD, Abdalla A, Goadsby PJ. Vestibular migraine. Clinical and diagnostic challenges, and emerging therapeutic approaches. Curr Opin Neurol. 2026 Feb 1;39(1):42-47. doi: 10.1097/WCO.0000000000001447. Epub 2025 Dec 2.
24. PMID: 34719447. Lempert T, Olesen J, Furman J, Waterston J, Seemungal B, Carey J, Bisdorff A, Versino M, Evers S, Kheradmand A, Newman-Toker D. Vestibular migraine: Diagnostic criteria1. J Vestib Res. 2022;32(1):1-6. doi: 10.3233/VES-201644.
25. PMID: 40023138. Toplu ACO, Aslan IK, Akoglu EU, Ozturk TC. The role of the HINTS exam, TriAGe+ score, and ABCD2 score in predicting stroke in acute vertigo patients in the ED. Am J Emerg Med. 2025 May;91:110-117. doi: 10.1016/j.ajem.2025.02.027. Epub 2025 Feb 20

Add comment