


 Shahriar Lahouti
Jan, 25, 2022 via Shahriar Lahouti. Last Update 20 July 2026.
CONTENTS
- Preface
- Background
- Approach to hypertensive emergencies
- Management
- Initial measures
- Antihypertensive treatment
- RECAP
- Going further
- References
Preface
Most patients with significantly elevated blood pressure have no acute, end-organ injury. Various retrospective reviews from adult emergency departments found that hypertensive emergencies account for less than 1% of all visits, with an estimated population incidence (based upon large claims databases) of one to two cases per million per year 1.
The most common mistake in practice is overdiagnosis of hypertensive emergency among patients with scary high blood pressure but no target organ damage. In this post, hypertensive emergency is reviewed with more focus on hypertensive emergency without a known cause.
Case Scenario
A 68-year-old woman with known hypertension and obstructive sleep apnea comes to the ED and reports headaches and blurred vision for the past 2 days. Her prescribed medications include amlodipine, hydrochlorothiazide, telmisartan, and bisoprolol. She uses CPAP for a sleep breathing disorder, but she acknowledges poor adherence and has not taken any of the drugs in approximately 1 week. On examination, she is confused but comfortable. The average of multiple blood pressure measurements is 231/137 mmHg, and the heart rate is 68 bpm; oxygen saturation is 96% RA. The electrocardiogram shows left ventricular hypertrophy. POCUS and other laboratory tests are unremarkable. Emergency CT of the head shows heterogeneous hypoattenuation of subcortical white matter in the posterior parieto-occipital regions bilaterally but no hemorrhage or infarction. How would you further evaluate and treat this patient?
Background
Mean arterial blood pressure (MAP)
MAP is the average blood pressure in a subject during the cardiac cycle. It represents the best single index of organ perfusion status and more closely correlates with risk of development of target organ damage. MAP is the preferred measurement of blood pressure for the following reasons:
- MAP is what the automated BP cuff is actually measuring: Automated oscillometric BP cuffs measure the MAP directly (whereas the systolic and diastolic BP are estimated using proprietary algorithms). This could make the MAP the most accurate measurement.
- While SBP is the focus of attention, the risk of hypertensive emergency seems overall to be more closely related to the diastolic pressure than the systolic pressure.
- By and large, MAP is probably the single parameter that is most closely related to the risk of hypertensive emergency.
- MAP is also the preferred BP index in therapy. The dosing of any antihypertensive drug can be more easily titrated against a single variable. Trying to titrate an antihypertensive infusion against systolic and diastolic blood pressure simultaneously is often impossible and confusing (for example, what happens if the systolic target is reached but not the diastolic!)
Definitions
◾️Definition of hypertension (HTN)
- The Joint National Committee 8 guidelines retained the same definitions of normal BP as the Joint National Committee 7 guidelines, with an average SBP <120 mm Hg and an average DBP <80 mm Hg. Hypertension is defined as office SBP values ≥ 140 mmHg and/or diastolic BP (DBP) values ≥ 90 mmHg.
- It should be noted that the number cutoffs (in the classification of BP and grading of HTN) are arbitrary and based on consensus opinion from the Joint National Committee 8 and thus should be used in the context of the specific clinical scenario (i.e., not all patients with markedly elevated BP have a hypertensive emergency).
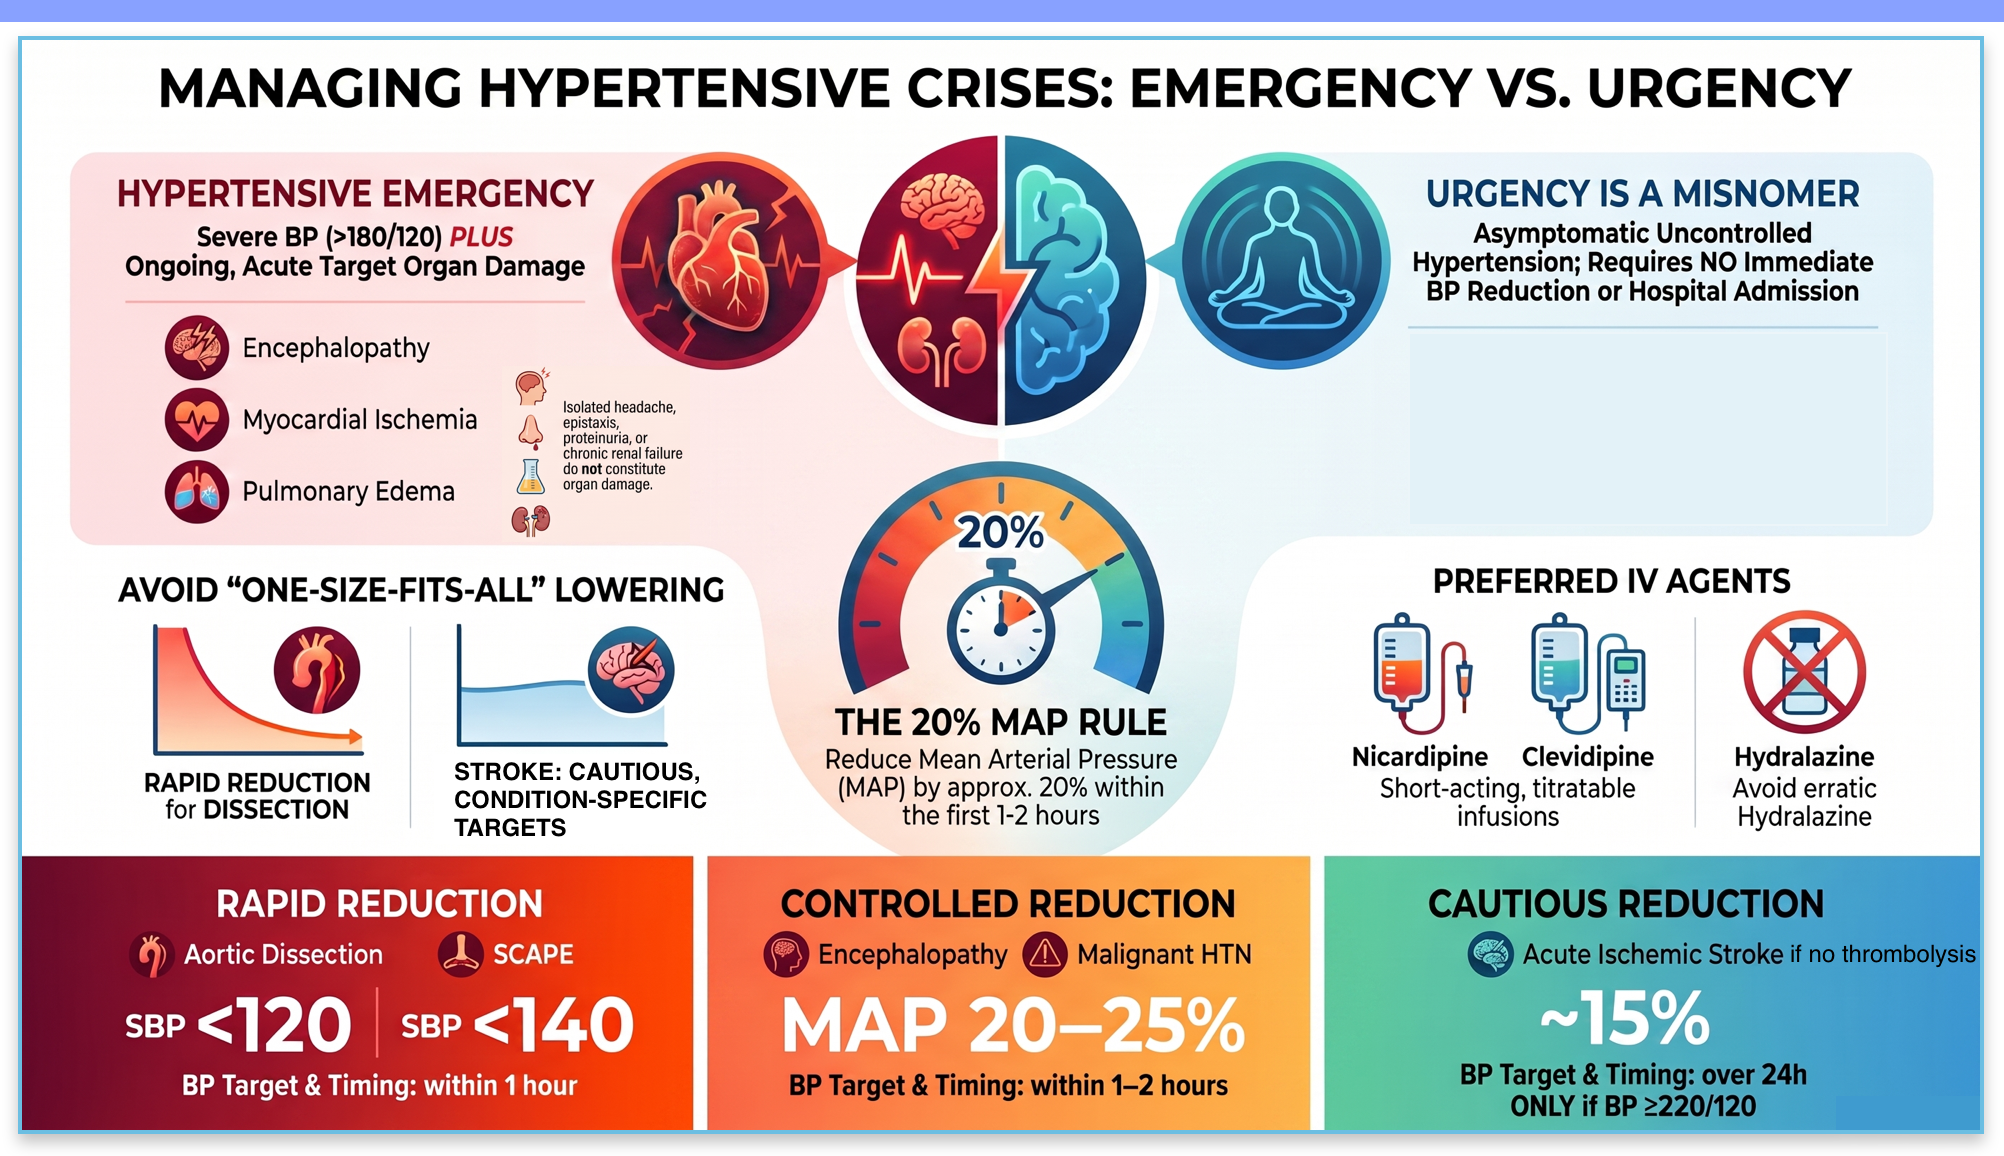
◾️Hypertensive emergency: It should be considered in any patient presenting with severely elevated BP (typically >180/120 mm Hg) and the presence of ongoing target organ damage.
- Keep in mind that normotensive individuals may develop hypertensive emergency at substantially lower BPs, in part because the adaptive vascular changes that protect organs from changes in BP have not developed 2. Alternatively, patients with chronic hypertension may have extremely elevated BP without hypertensive emergency.
Pathophysiology
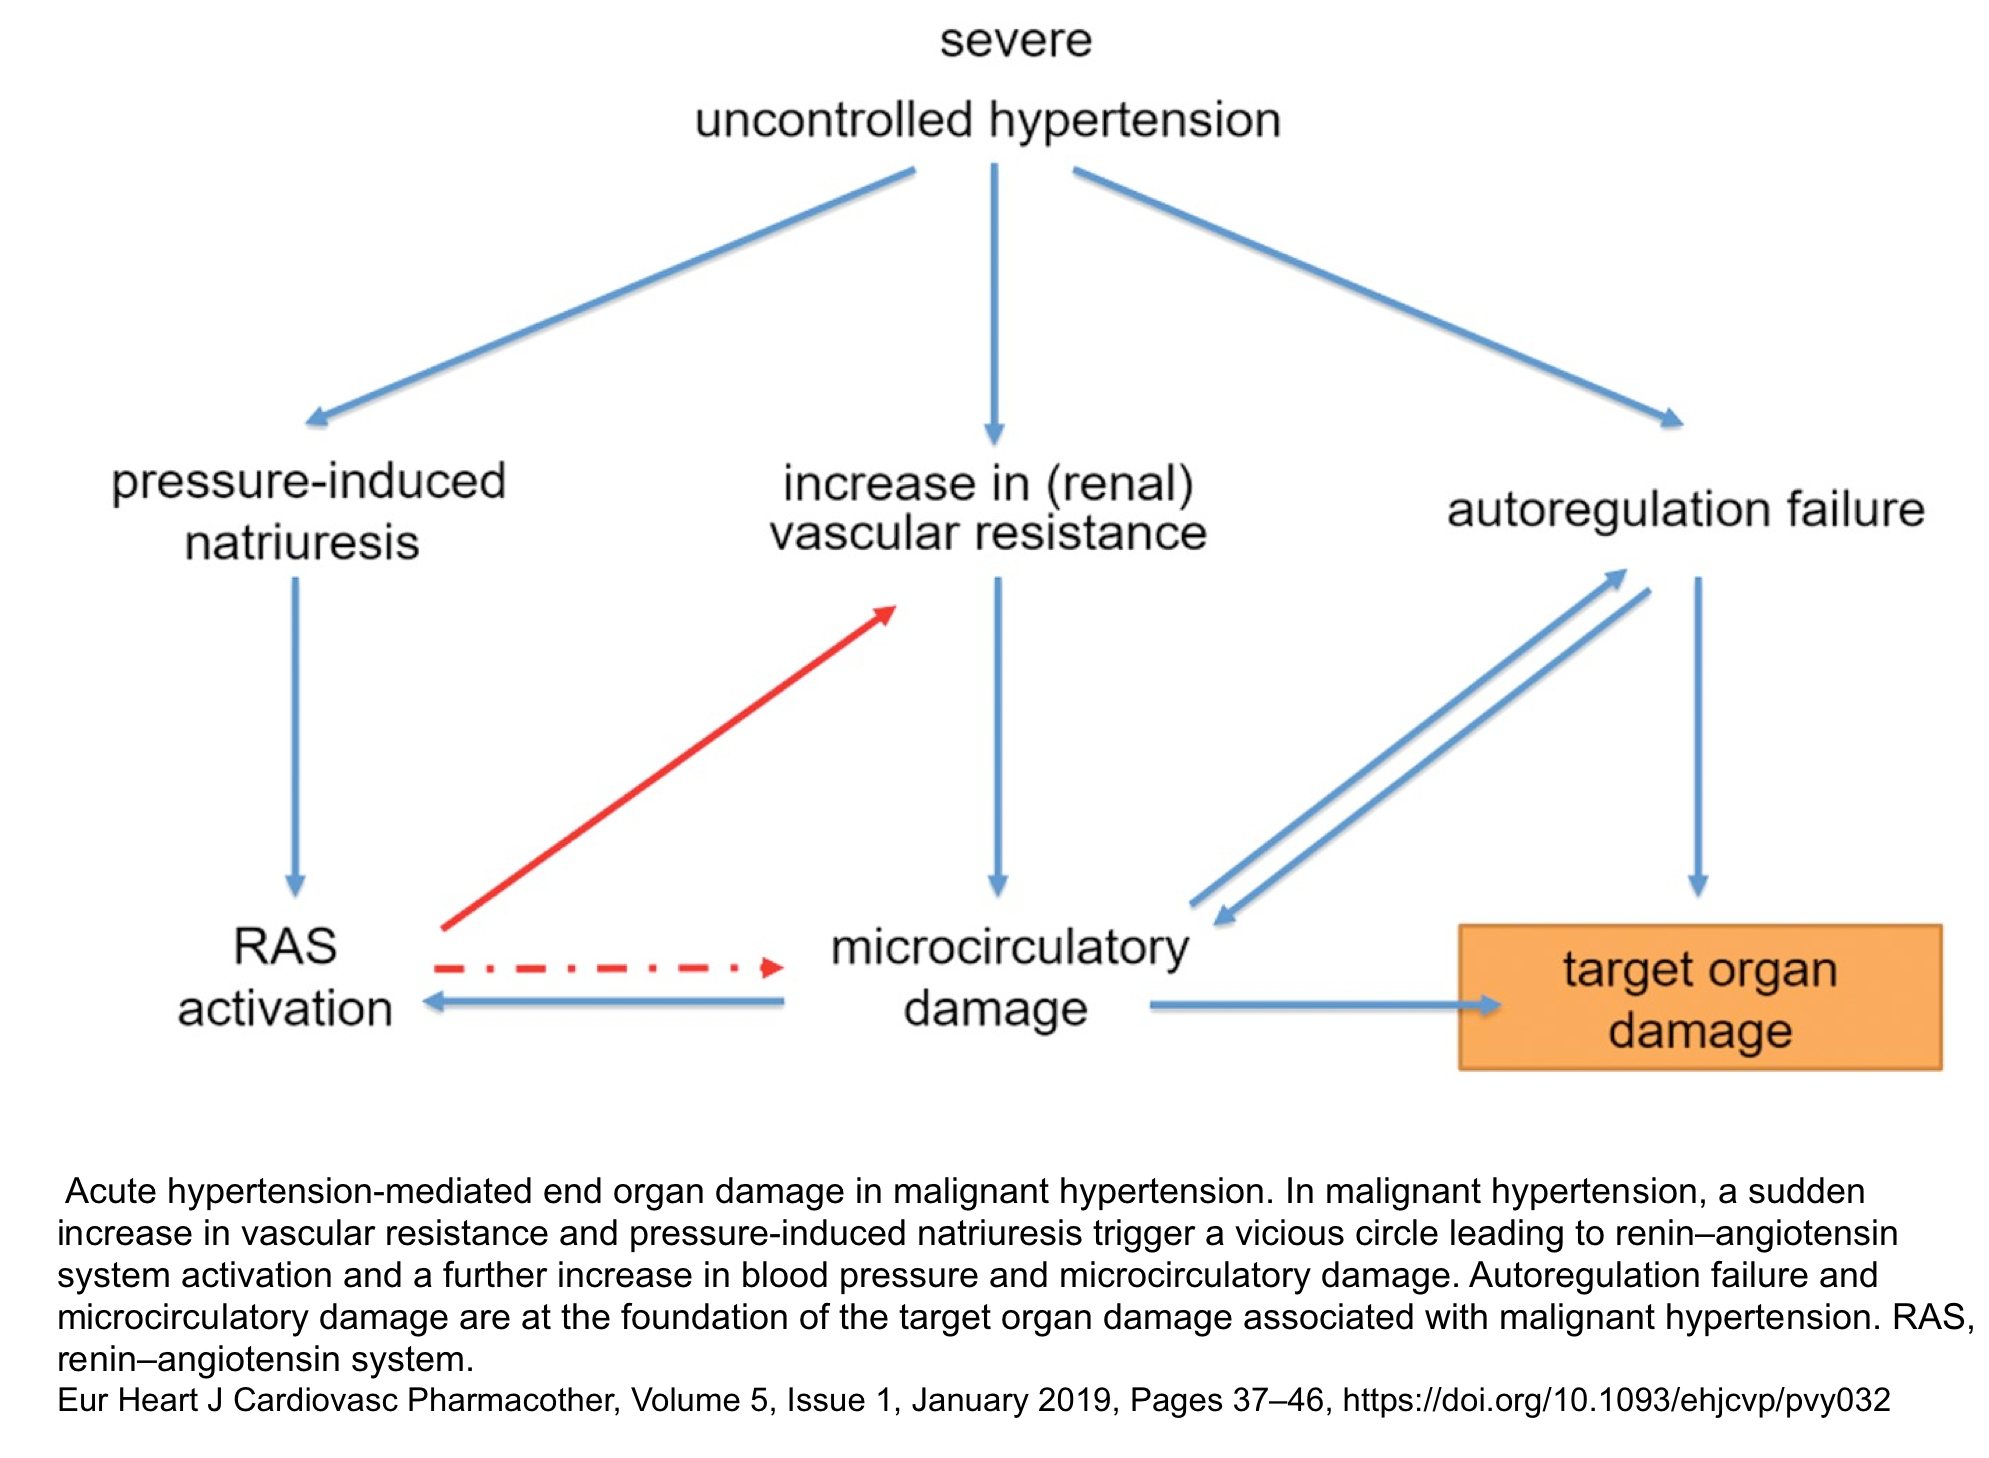
Chronic uncontrolled hypertension leads to progressive microvascular damage. This will cause a vicious spiral that perpetuates target organ damage (figure below) 3.
- The core of this spiral is that hypertension causes microcirculatory damage that impairs renal perfusion, leading to activation of the renin-angiotensin system (RAS). RAS activation, in turn, causes vasoconstriction, which leads to worsening hypertension.
- Pressure-induced natriuresis further contributes to the contraction of blood volume and activation of the renin–angiotensin system.
- Microvascular damage and autoregulation failure are at the foundation of the target organ damage associated with malignant hypertension and result in hypertensive retinopathy, TMA, and encephalopathy, complications that are not observed in patients with chronic uncontrolled hypertension.
Approach to hypertensive emergencies
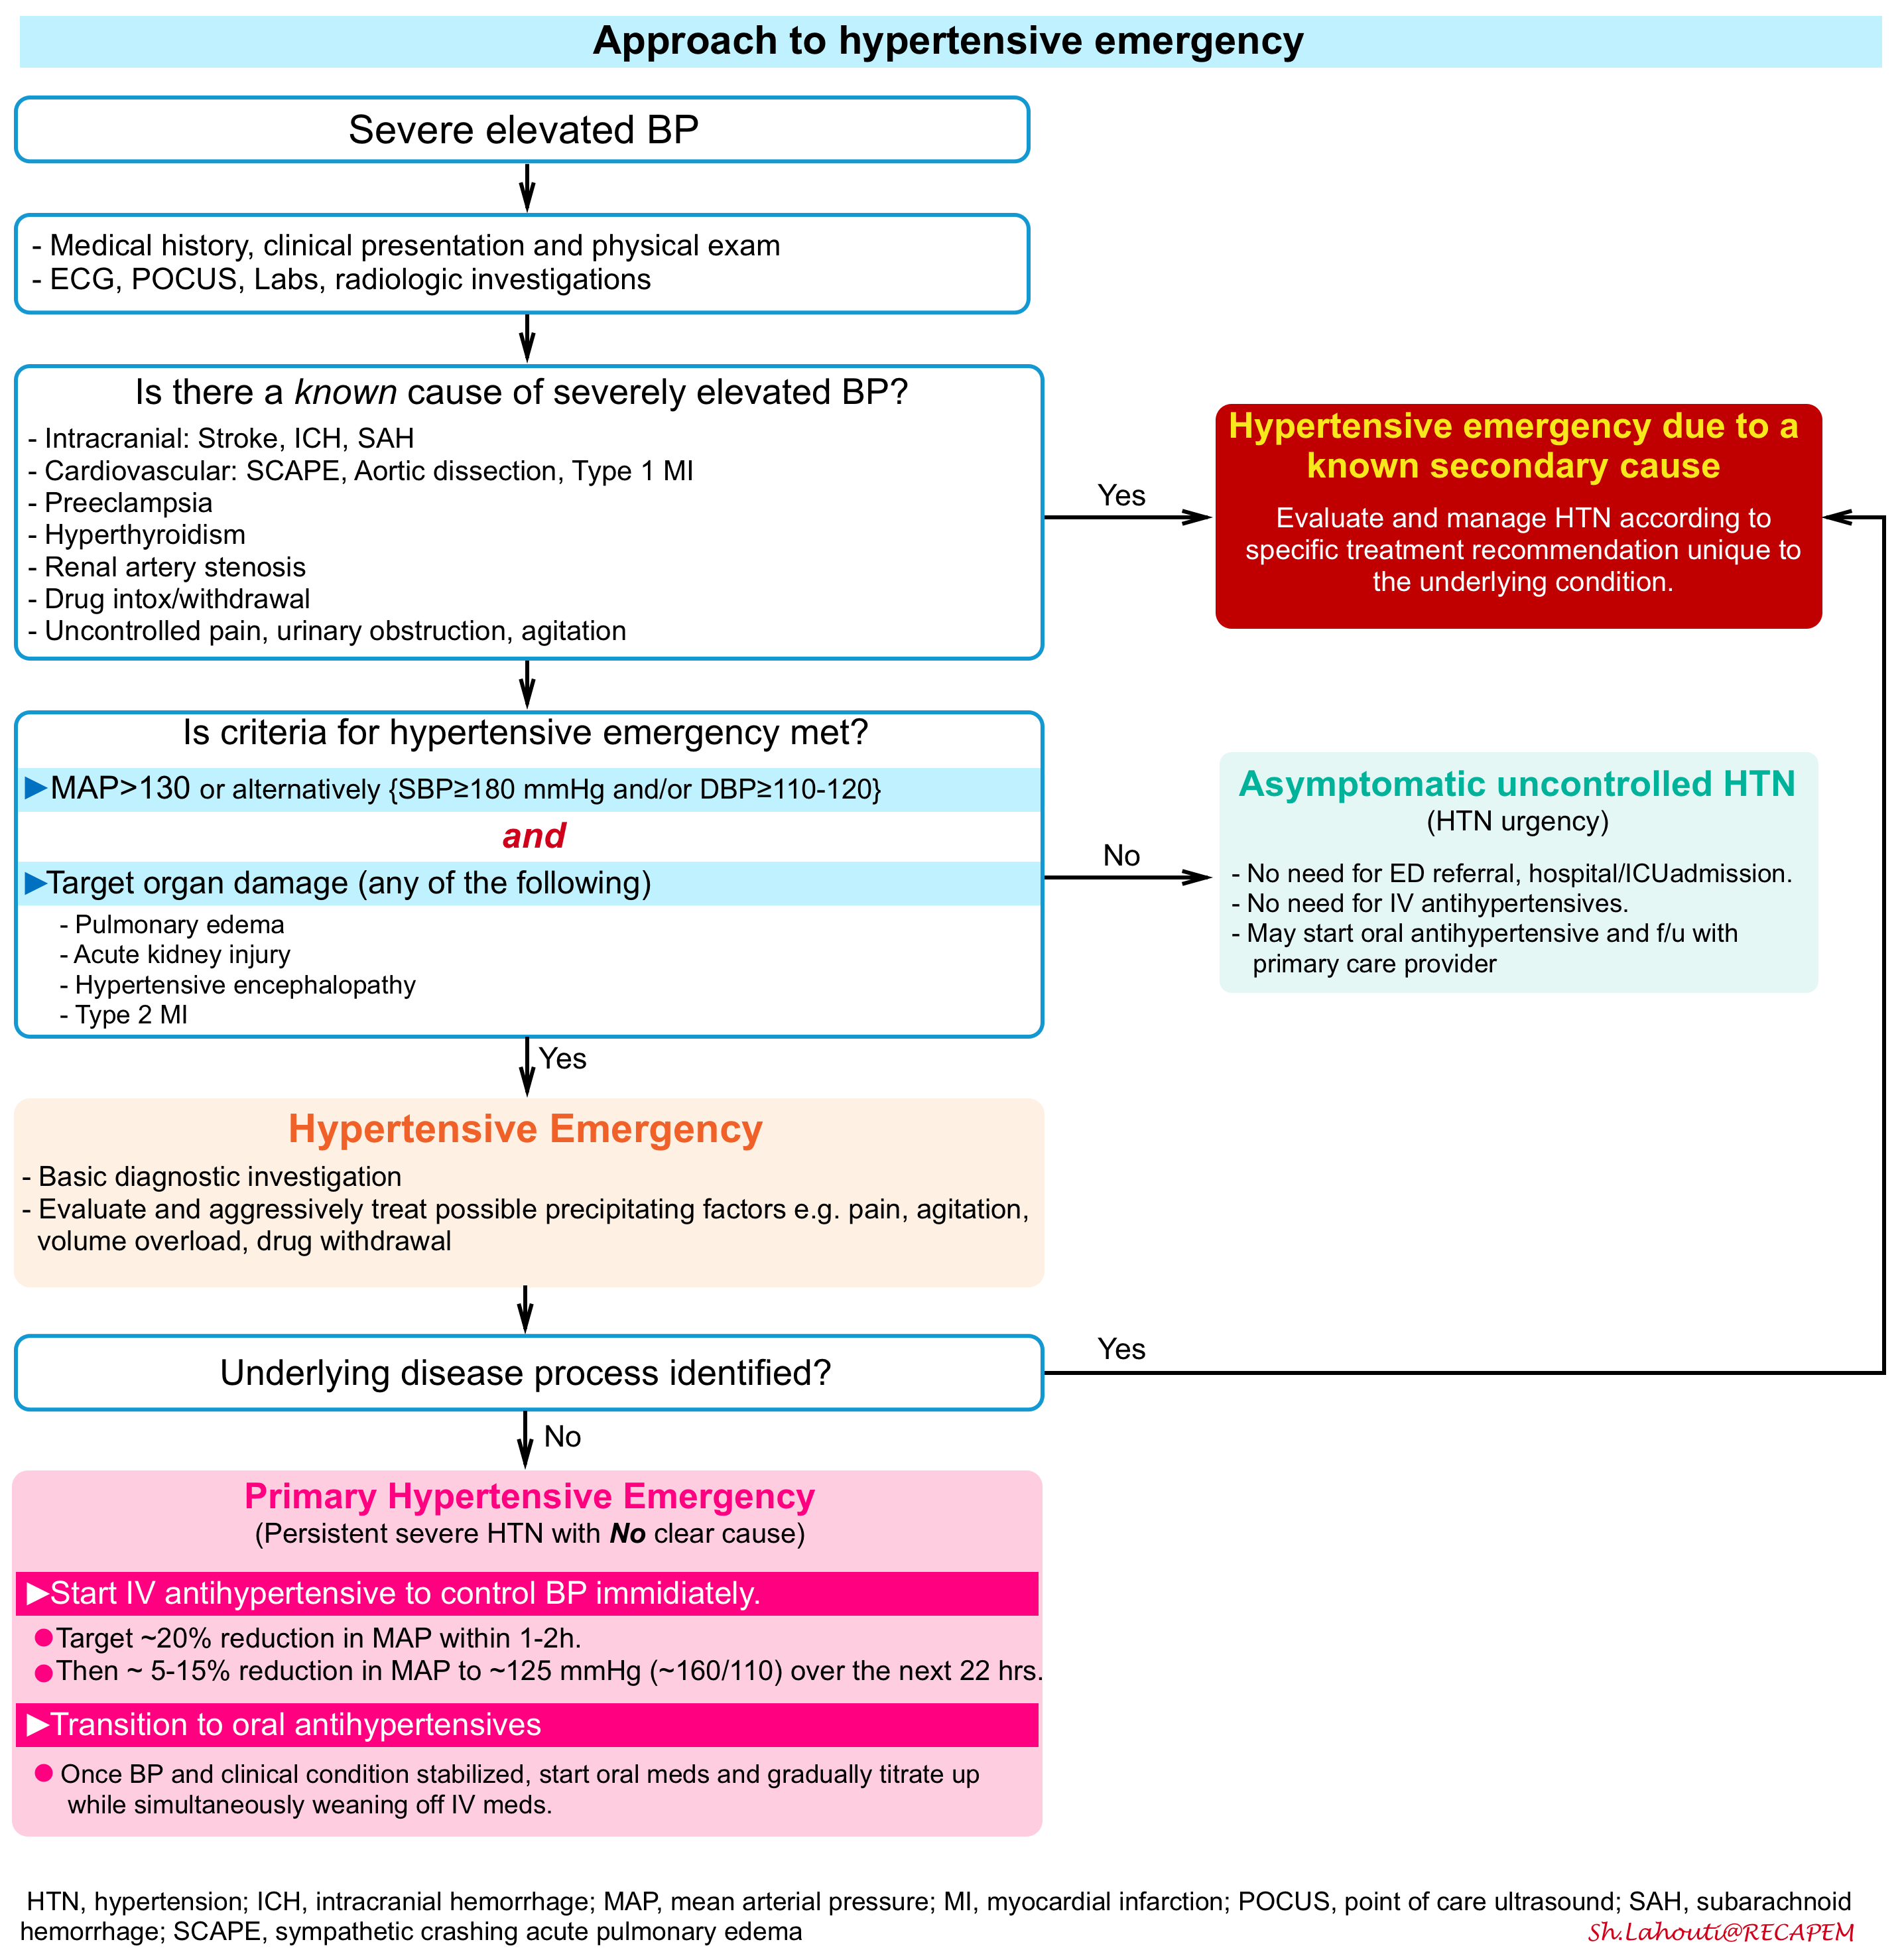
The evaluation of a patient with severely elevated blood pressure can be challenging, as the optimal management strategy hinges on a single, critical distinction: is there acute, progressive target organ damage (TOD)?
The following algorithm provides a structured framework to guide the clinician through this process. It emphasizes the following key steps:
- Ruling out a secondary cause: Identifying specific conditions (e.g., aortic dissection, stroke, preeclampsia) that dictate a unique treatment approach.
- Making the Emergency vs. Urgency distinction: Differentiating a true hypertensive emergency (severe BP + TOD) from asymptomatic uncontrolled hypertension (severe BP, no TOD).
- Implementing controlled BP reduction: For true emergencies, initiating a staged, cautious reduction in blood pressure tailored to the patient’s specific condition and baseline.
🚨The goal is to prevent the two most common errors:
- Over-treating patients with asymptomatic hypertension
- Applying a “one-size-fits-all” approach to all hypertensive emergencies.
Algorithm: An overview of the approach to hypertensive emergency is shown below *.
Etiology of Secondary hypertensive emergencies
Severely elevated BP can be the result of some other primary process 4. In most cases, the primary process will be more obvious clinically, dominating the initial clinical presentation (e.g., aortic dissection, sympathetic crashing acute pulmonary edema, etc.). Prompt management of BP is recommended; however, treatment will vary widely, depending on the specific context. Some clinically common examples include 5:
- Aortic dissection
- SCAPE (sympathetic crashing acute pulmonary edema)
- Intracranial: Acute Ischemic Stroke, ICH , SAH
- Preeclampsia
- Endocrinopathy (e.g., pheochromocytoma, hyperthyroidism).
- Renal (scleroderma renal crisis, acute glomerulonephritis, renal artery stenosis).
- Drug withdrawal/intoxication: Withdrawal (e.g., from alcohol or benzodiazepines) / Sympathomimetic drug intoxication e.g., cocaine or methamphetamines.
- Other medications (e.g. cyclosporine, tacrolimus, erythropoietin, steroid, NSAIDs, anti-angiogenic drugs).
- Pain, urinary obstruction, anxiety.
- Volume overload
🚩In this post, the discussion is centered on primary hypertensive emergency. For the pharmacologic approach to hypertensive emergencies with a known cause, see the following table.
Diagnostic criteria
Hypertensive emergency
- Severe hypertension
- Usually, a MAP of at least >135 mm is needed to cause a hypertensive emergency (SBP ≥180 mmHg and/or DBP ≥120 mmHg) *.
- However, these numbers may vary considerably depending on the patient’s baseline BP.
- The relative change in blood pressure from baseline is more important than its absolute value.
- Usually, a MAP of at least >135 mm is needed to cause a hypertensive emergency (SBP ≥180 mmHg and/or DBP ≥120 mmHg) *.
- Ongoing target organ damage
- Pulmonary edema
- Acute kidney injury (often with microscopic hematuria)
- Hypertensive encephalopathy (e.g., delirium, visual disturbance, seizure).
- Myocardial ischemia (Type II Myocardial Ischemia). This should be a true myocardial infarction, not solely an elevated troponin.
🚨Headache, epistaxis, proteinuria, and chronic renal failure do not constitute target organ damage in a hypertensive emergency.
- The diagnosis of a hypertensive emergency requires evidence of acute, progressive end-organ injury (e.g., encephalopathy, myocardial ischemia, pulmonary edema, acute kidney injury) *. These chronic or non-specific findings should not trigger immediate, aggressive blood pressure reduction, as this may cause harm in patients with asymptomatic uncontrolled hypertension.
Hypertensive urgency
This is a term that has been used to refer to patients with severely elevated BP (>180/120) who do not have target organ damage. However, this is a misnomer because there is no “urgent” need to reduce the BP 6, and:
- There is NO need for referral to the emergency department.
- There is NO need for hospital admission.
- There is NO need for ICU admission.
It would probably be ideal to eliminate the term “hypertensive urgency” and replace it with the term “asymptomatic uncontrolled hypertension” (which might discourage over-reacting to this condition) 7.
If a patient with hypertensive urgency is encountered in the outpatient context, it might be reasonable to start them on a low dose of a chronic oral antihypertensive agent with a relatively benign side-effect profile (e.g. amlodipine). It might also be reasonable to arrange close follow-up with their primary care provider for the management of their blood pressure. Obtaining adequate follow-up and ambulatory blood pressure measurement is probably more important than immediate patient management. This is not a critical care topic, so it’s beyond the scope of this book.
Evaluation
- Repeat blood pressure measurement
- History
- Baseline BPs
- History of hypertension?
- Antihypertensive regimen?
- Compliance with regimen?
- Sleep-disordered breathing?
- Nonadherence with CPAP or BiPAP therapy?
- Any prior episodes of hypertensive emergency?
- Illicit drug use?
- Symptoms
- Chest discomfort
- Dyspnea
- Delirium or depressed level of consciousness, visual disturbance, seizure, vomiting, and headache are found in patients with hypertensive encephalopathy or posterior reversible encephalopathy syndrome (PRES).
- POCUS
- Evidence of aortic dissection?
- Pulmonary edema on lung ultrasonography?
- IVC: Volume status?
- Optic nerve sheath diameter: Increased optic nerve sheath diameter on ultrasound might support the diagnosis of hypertensive encephalopathy with increased intracranial pressure.
- Renal ultrasound (postrenal obstruction, kidney size, left-to-right difference)
- ECG
- Labs
- Basic labs (chemistries, CBC, coagulation studies).
- PBS: blood smear may be required to search for microangiopathic anemia (schistocytes).
- Troponin (only if ECG/clinical evidence to support MI).
- Urinalysis: May reveal proteinuria or hematuria in patients with renal damage
- Urine toxicology screen may be considered.
- Pregnancy evaluation as appropriate
- Non-contrast head CT: If the presentation is worrisome for possible intracranial hemorrhage.
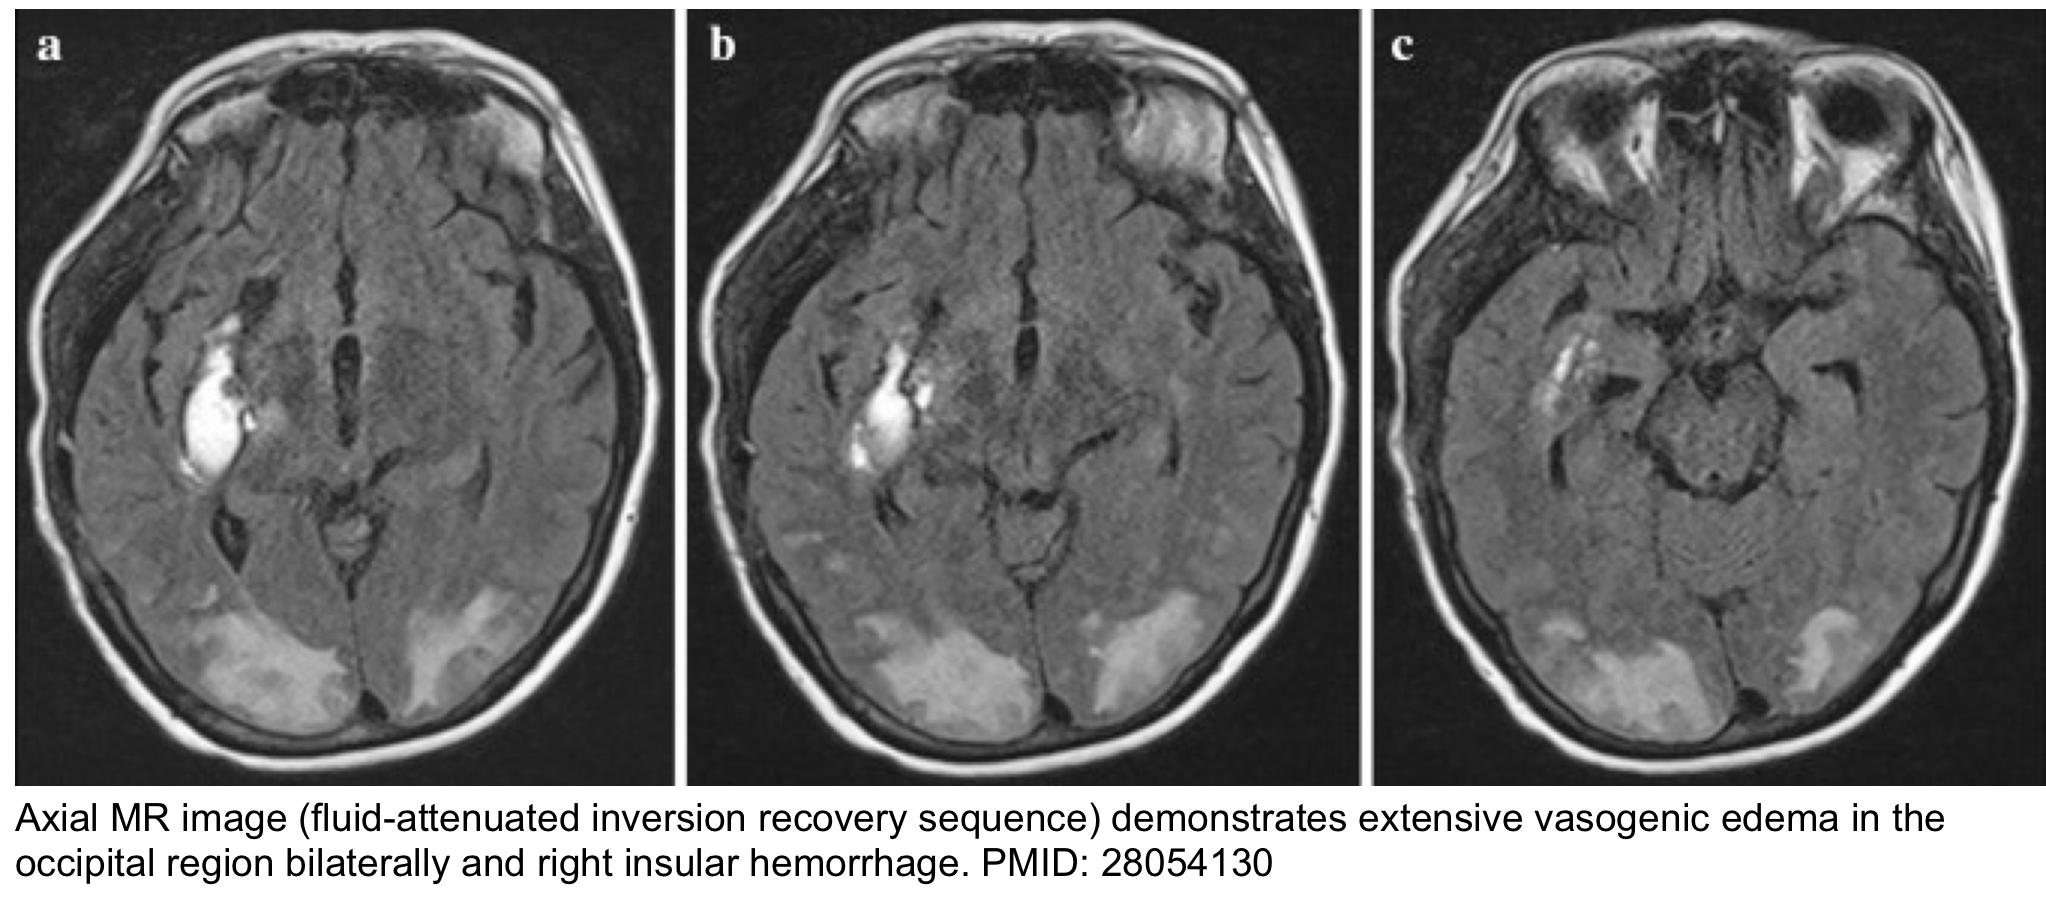
- Brain MRI: T2/FLAIR MRI is often required to confirm a clinical diagnosis of posterior reversible encephalopathy syndrome (PRES). Vasogenic edema is invariably seen on MRI and appears as hyperintensity on T2/FLAIR (figure below).
- CT-angiography of thorax and abdomen (If acute aortic disease suspected)
Management
Initial measures
Management begins with appropriate monitoring including serial automated BP assessments, and cardiac telemetry. Ensure a patent airway, and supplement oxygen as needed. Obtain bilateral, large-bore (i.e., 18-20 g) peripheral venous access.
◾️Arterial line: Indications for an arterial line might include:
- Very labile blood pressure.
- Profound hypertension (too high to be real?).
- Clinical deterioration despite noninvasive management.
◾️Initial diagnostic/therapeutic measures
- Before initiation of antihypertensives, consider some simple interventions that may be highly effective in reducing blood pressure. Interventions that may rapidly reduce blood pressure:
-
- Pain: Treat with appropriate analgesia.
- Agitation: Treat with antipsychotics, dexmedetomidine, or benzodiazepines.
- Volume overload: Treat with diuresis or dialysis.
- Alcohol withdrawal: Phenobarbital.
- Urinary retention: Foley catheter.
Antihypertensive treatment
Target BP
🎯Goals
- The initial goal is to decrease the MAP by ~20% within 1-2 hours 9.
- If this reduction is tolerated, decrease the MAP by ~5-15% to ~125 mmHg (~ 160/110) over the next 2-6 hours *.
- The blood pressure may subsequently be gradually decreased further over a period of days, as clinically tolerated.
- These general recommendations may not hold for every patient. Consider the patient’s baseline pressure and how rapidly the pressure increased.
- For a patient with chronic hypertension, a more gradual approach to lowering the BP may be wise.
- For a patient with very acute development of hypertension (e.g. due to an acute sympathomimetic drug intoxication), a more rapid reduction of BP may be reasonable.
🧰 Troubleshooting: If BP drops following IV antihypertensive medications:
- Pathophysiologic background
- Patients have excessive vasoconstriction, which is driving their hypertension.
- Most hypertensive emergency patients are volume-depleted due to the phenomenon of pressure natriuresis.
- When treated with vasodilation, these patients may develop hypotension (due to unmasking of their hypovolemia). As such, IV fluid administration should be considered, which may prevent iatrogenic hypotension when antihypertensives are initiated.
Overview of treatment strategy
The management of a hypertensive emergency requires a nuanced approach, as the optimal speed and extent of blood pressure (BP) reduction depend heavily on the specific underlying condition. The fundamental principle is to avoid an excessively rapid and uncontrolled decrease in BP, which can precipitate cerebral, cardiac, or renal ischemia, especially in patients with chronic hypertension whose autoregulatory curves are shifted to the right.
The following table categorizes hypertensive emergencies into three strategic groups based on the urgency of BP control:
- Rapid Reduction (within 1 hour): For conditions where elevated BP directly and immediately threatens life or organ integrity. This includes aortic dissection (where SBP must be lowered to <120 mm Hg and heart rate to 60-70 bpm to prevent propagation), SCAPE (flash pulmonary edema, requiring rapid afterload reduction), eclampsia/preeclampsia, and pheochromocytoma crisis.
- Controlled Reduction (over 1-2 hours): For malignant hypertension and hypertensive encephalopathy/PRES, a more gradual reduction of the mean arterial pressure (MAP) by 20-25% over the first 1-2 hours is recommended to prevent hypoperfusion while still halting progressive organ damage.
- Cautious Reduction or No Acute Reduction: For acute ischemic stroke, intracerebral hemorrhage (ICH), and subarachnoid hemorrhage (SAH) before the aneurysm is secured, the risks of lowering BP too quickly often outweigh the benefits, as cerebral autoregulation is impaired. Specific, cautious targets are applied in certain circumstances (e.g., before thrombolysis, when BP is extremely elevated, or to balance rebleeding risk against cerebral perfusion), but routine, aggressive lowering is generally avoided.
For each condition, the table below details the specific BP target, timing, recommended drugs, and key clinical considerations, based on the 2023 ESH Guidelines and the narrative review by Jolly et al.
📋 Treatment Strategies for Hypertensive Emergencies
▾| Category | Condition | BP Target & Timing | Drugs of Choice | Key Considerations |
|---|---|---|---|---|
| Rapid | Aortic dissection |
SBP <120 mm Hg HR 60–70 bpm within 1 hour |
|
Most urgent Measure BP in all limbs. Avoid hypotension Immediate surgical consultation. |
| Rapid | SCAPE (flash pulmonary edema) |
SBP <140 mm Hg rapidly (minutes to 1 hour) |
|
Afterload reduction is key Watch for rebound hypotension as SCAPE resolves. |
| Rapid | Eclampsia / severe preeclampsia |
SBP <160 mm Hg DBP <105 mm Hg within 1 hour |
|
Consider delivery. Monitor for HELLP. Avoid excessive reduction |
| Rapid | Pheochromocytoma crisis |
Titrate to normotension Alpha‑blockade first |
|
Beta‑blockers only after alpha‑blockade. Surgical resection after stabilization. Risk of hypertensive crisis |
| Controlled | Malignant hypertension (with TOD) |
Reduce MAP 20–25% within 1–2 hours then ~160/100–110 mm Hg over 2–6 h gradual over 24–48 h |
|
Avoid overshoot hypotension Patients often volume‑depleted. IVF may be needed if BP drops. |
| Controlled | Hypertensive encephalopathy / PRES |
Reduce MAP 20–25% within 1–2 hours Target MAP ~105–125 mm Hg |
|
Seizures common → EEG. Treat underlying cause. Avoid excessive reduction |
| Cautious | Acute ischemic stroke (no thrombolysis) |
If BP ≥220/120: Reduce ~15% over 24 h Otherwise: no treatment 48–72 h |
|
Risk of penumbral hypoperfusion Autoregulation impaired. Hypotension is dangerous. |
| Cautious | Acute ischemic stroke (thrombolysis / EVT) |
Before: <185/110 mm Hg After: <180/105 mm Hg maintain 24 hours |
|
Avoid SBP <140 mm Hg post‑EVT. Monitor for hemorrhagic transformation. |
| Cautious | Intracerebral hemorrhage (ICH) |
If SBP 150–220: Target SBP 130–150 mm Hg Avoid <130 mm Hg If SBP >220: target 140–180 |
|
Avoid hypotension – maintain CPP. Reverse anticoagulation immediately. Neurosurgical consultation. |
| Cautious | Subarachnoid hemorrhage (SAH) |
Before aneurysm secured: Target SBP <160–180 mm Hg After secured: permissive hypertension SBP <200 mm Hg (reduces likelihood of vasospasm) |
|
Avoid hypotension – maintain CPP. Treat pain first – analgesia lowers BP. Secure aneurysm promptly (<24–72 h). |
IV Antihypertensive medications
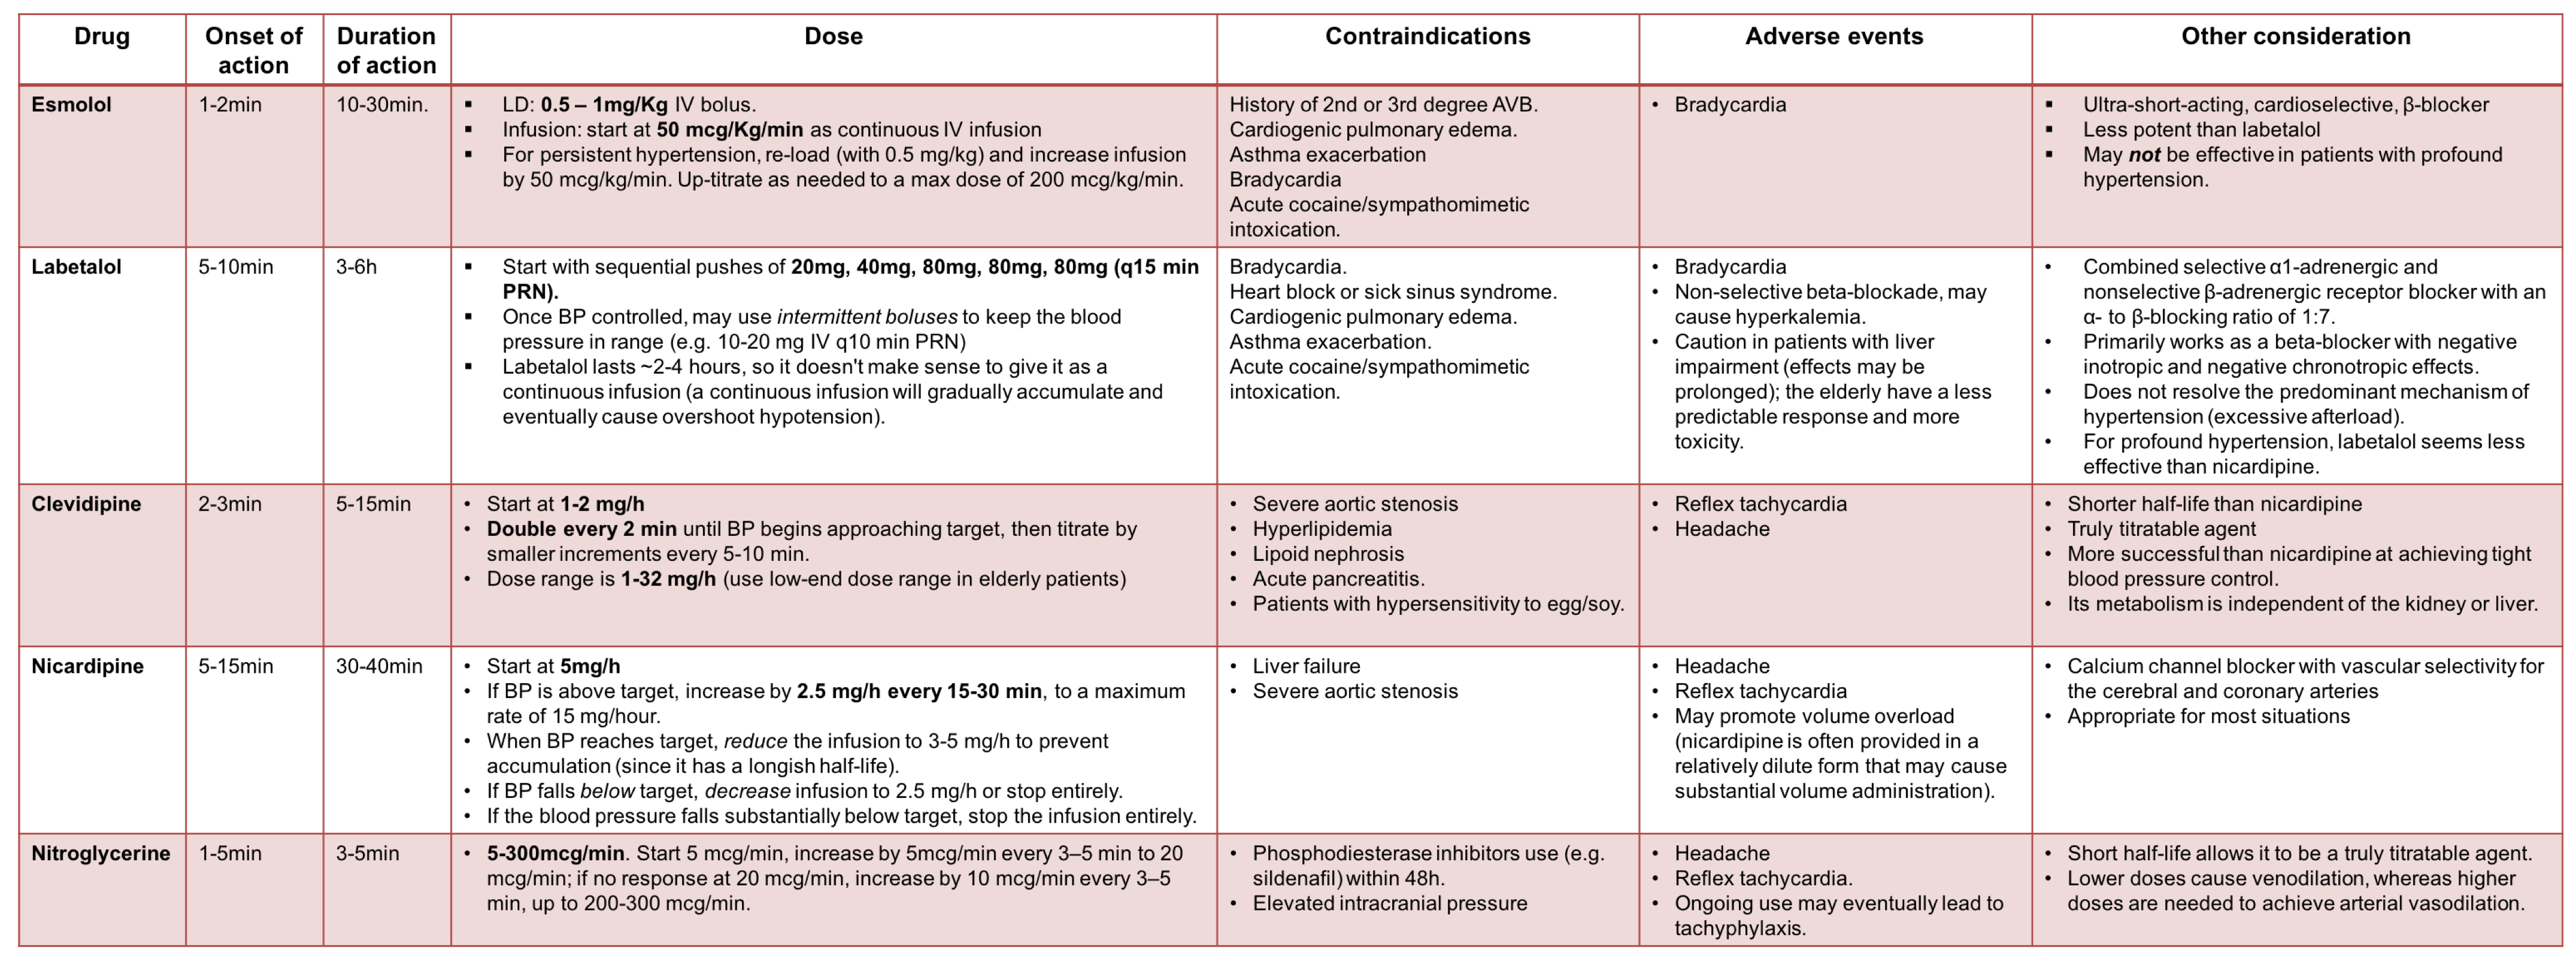
For most hypertensive emergencies, intravenous (IV) therapy is preferred due to its rapid onset and titratability. The selection of an IV antihypertensive agent should be guided by the specific clinical scenario, the drug’s pharmacokinetic profile, and the patient’s comorbidities 6, 8.
- In general, continuous infusions are used for drugs with a short half-life (e.g., nitroglycerine). The short half-life means that the drug needs to be infused continuously. It also makes the drug easily titratable.
- Intermittent boluses are used for drugs with longer half-lives (most drugs).
IV antihypertensive drugs can be classified into three categories based on their duration of action and ease of titration:
- Truly titratable agents (duration of action <30 minutes): These drugs are given as continuous infusions and are ideal for precise BP control. Examples include nitroglycerine, esmolol, and clevidipine.
- Partially titratable agents (duration of action 1-2 hours): These are also given as continuous infusions but require more careful monitoring to avoid accumulation and overshoot hypotension. Examples include nicardipine and diltiazem.
- Bolus agents (duration of action >1-2 hours): These are best administered as intermittent boluses rather than infusions, as infusions tend to accumulate and become difficult to titrate. Examples include labetalol and metoprolol.
⚠️Agents to avoid in most hypertensive emergencies include
- Nitroprusside
- Can increase the intracranial pressure
- Can cause cyanide toxicity and lactic acidosis
- Tends to cause wide swings in the BP; therefore, an arterial line should be inserted to allow for adequate monitoring of these BP swings.
- Hydralazine.
- Effect is unpredictable
- Impossible to titrate
- In most situations, another agent will be equally effective and safer (one potential exception is preeclampsia with refractory hypertension).
📊The table below summarizes the IV antihypertensive agents commonly used in the management of hypertensive emergencies, including their onset, duration, dosing, and key considerations.
Oral antihypertensive medication
Transition to oral antihypertensive medication
After BP has been controlled for 12-24 hours, oral antihypertensive agents may be initiated while the patient is weaned off IV agents.
- Start oral antihypertensives after the patient has stabilized and improved on IV antihypertensives for several hours.
- Oral antihypertensives may be gradually up-titrated, with simultaneous weaning off IV antihypertensives.
- The key concern with oral antihypertensive agents is how rapidly they take effect.
- As in any other situation where you’re up-titrating medications, it’s important to allow one dose of medication to take effect before you escalate the dose.
- If doses are escalated before the last dose has taken effect, this may eventually lead to an excessive drop in blood pressure.
Factors to consider when selecting an oral antihypertensive
- Response to IV therapy:
- A favorable response to nicardipine suggests a dihydropyridine CCB like nifedipine XR; a response to labetalol suggests an alpha/beta-blocker like carvedilol.
- Onset of action:
- Choose agents that take effect within ~2 hours to allow rapid titration and weaning of IV drugs. This allows for a fairly prompt up-titration of oral doses, which allows rapid weaning of the IV antihypertensive agent
- Avoid slow-onset drugs:
- Amlodipine takes days to work and has no role in acute management. Metoprolol lowers heart rate but is relatively ineffective for BP control.
- Consider comorbidities:
- For HFrEF, prioritize carvedilol or ACEi/ARB; for CAD, consider beta-blockers.
- Review home regimen:
- Always consider the patient’s home antihypertensive regimen. This provides valuable clues about the required number and doses of agents. In many cases—especially when nonadherence was the trigger—resuming some or all of the patient’s home medications is the most appropriate and effective strategy.
Oral antihypertensive drugs
The table below summarizes commonly used oral antihypertensives for this transition, with their onset, dosing, and key considerations
💊 Oral Antihypertensive Agents for Transition
▾| Drug | Onset | Duration | Starting Dose | Key Considerations | Indications | Contraindications | Adverse Events |
|---|---|---|---|---|---|---|---|
| Nifedipine XR Dihydropyridine CCB Recommended | ~2–4 h | ~24 h |
|
|
|
|
|
| Isradipine Dihydropyridine CCB Alternative | ~1–2 h | ~12 h |
|
|
|
|
|
| Carvedilol Alpha/Beta-blocker Recommended | ~2–4 h | ~10 h |
|
|
|
|
|
| Labetalol Alpha/Beta-blocker Recommended | ~2 h | ~10 h |
|
|
|
|
|
| Captopril ACE inhibitor Recommended | ~15–30 min | ~6 h |
|
|
|
|
|
| Losartan ARB Alternative | ~4–6 h | ~24 h |
|
|
|
|
|
| Clonidine Centrally acting Special Use | ~1 h | ~12 h |
|
|
|
|
|
| Diltiazem Non-DHP CCB Alternative | ~2–4 h | ~24 h |
|
|
|
|
|
| Metoprolol Beta-1 blocker NOT RECOMMENDED | ~1–2 h | ~6–12 h |
|
|
|
|
|
| Amlodipine Dihydropyridine CCB NOT RECOMMENDED | ~6–12 h | ~24–48 h |
|
|
|
|
|
CCB: Calcium channel blocker ACEi: ACE inhibitor ARB: Angiotensin receptor blocker HFrEF: Heart failure with reduced ejection fraction AKI: Acute kidney injury AS: Aortic stenosis XR: Extended release IR: Immediate release ER: Extended release CAD: Coronary artery disease MI: Myocardial infarction SCAPE: Sympathetic crashing acute pulmonary edema GDMT: Guideline-directed medical therapy DILI: Drug-induced liver injury
⚠️ Key takeaway: Prioritize rapid-onset agents (nifedipine XR, captopril, labetalol, carvedilol, isradipine) for transition. Avoid amlodipine and metoprolol as primary antihypertensives in this setting. Always consider the patient’s home regimen and response to IV therapy.
RECAP
-
Emergency vs. Urgency: The presence of acute, progressive target organ damage (e.g., encephalopathy, myocardial ischemia, pulmonary edema, acute kidney injury) defines a hypertensive emergency. Headache, epistaxis, proteinuria, and chronic renal failure do NOT qualify and should not trigger aggressive intervention.
-
Identify Secondary Causes: Always search for an underlying condition (e.g., aortic dissection, AIS, ICH, SCAPE, preeclampsia). The specific BP target and drug choice are dictated by the underlying cause, not just the BP level.
-
Controlled Reduction: For most emergencies, reduce MAP by ~20% within 1-2 hours, then by another 5-15% to ~125 mmHg over the next 22 hours. Avoid dropping BP too fast or too far — this can precipitate cerebral, cardiac, or renal ischemia.
-
A few exceptions where immediate BP lowering is warranted include Aortic dissection, SCAPE, Severe preeclapsia, pheochromocytoma crisis. See table above.
-
-
IV Drug Selection: Prefer titratable IV agents (e.g., clevidipine, nicardipine, esmolol) over bolus agents (e.g., labetalol, metoprolol) for precise control. Avoid nitroprusside (cyanide risk, wide swings) and hydralazine (unpredictable, non-titratable) in most cases.
-
Transition to Oral: Start oral therapy after 8-24 hours of stable IV control. Choose rapid-onset agents (nifedipine XR, captopril, labetalol, carvedilol) to facilitate IV weaning. Avoid amlodipine (too slow) and metoprolol (weak BP effect). Always review the home regimen — resuming it is often the best strategy, especially if nonadherence was the trigger.
-
Watch for Volume Depletion: Most hypertensive emergency patients are volume-depleted due to pressure natriuresis. If BP drops after starting IV vasodilators, evaluate for hypovolemia and consider IV fluid administration to prevent overshoot hypotension.
Going further
- Hypertensive emergencies (Emergency Medicine Cases)
- Emergencies with a Side of Hypertension (EMCrit)
- Hypertensive emergency (IBCC)
References
1. Astarita A, Covella M, Vallelonga F, Cesareo M, Totaro S, Ventre L, Aprà F, Veglio F, Milan A. Hypertensive emergencies and urgencies in emergency departments: a systematic review and meta-analysis. J Hypertens. 2020 Jul;38(7):1203-1210. doi: 10.1097/HJH.0000000000002372. PMID: 32510905
2. Williams B, Mancia G, Spiering W, Agabiti Rosei E, Azizi M, Burnier M, Clement DL, Coca A, de Simone G, Dominiczak A, Kahan T, Mahfoud F, Redon J, Ruilope L, Zanchetti A, Kerins M, Kjeldsen SE, Kreutz R, Laurent S, Lip GYH, McManus R, Narkiewicz K, Ruschitzka F, Schmieder RE, Shlyakhto E, Tsioufis C, Aboyans V, Desormais I; ESC Scientific Document Group. 2018 ESC/ESH Guidelines for the management of arterial hypertension. Eur Heart J. 2018 Sep 1;39(33):3021-3104. doi: 10.1093/eurheartj/ehy339. Erratum in: Eur Heart J. 2019 Feb 1;40(5):475. PMID: 30165516.
3. van den Born BH, Lip GYH, Brguljan-Hitij J, Cremer A, Segura J, Morales E, Mahfoud F, Amraoui F, Persu A, Kahan T, Agabiti Rosei E, de Simone G, Gosse P, Williams B. ESC Council on hypertension position document on the management of hypertensive emergencies. Eur Heart J Cardiovasc Pharmacother. 2019 Jan 1;5(1):37-46. doi: 10.1093/ehjcvp/pvy032. Erratum in: Eur Heart J Cardiovasc Pharmacother. 2019 Jan 1;5(1):46. PMID: 30165588.
4. Peixoto AJ. Acute Severe Hypertension. N Engl J Med. 2019 Nov 7;381(19):1843-1852. doi: 10.1056/NEJMcp1901117. PMID: 31693807
5.Johnson W, Nguyen ML, Patel R. Hypertension crisis in the emergency department. Cardiol Clin. 2012 Nov;30(4):533-43. doi: 10.1016/j.ccl.2012.07.011. Epub 2012 Oct 2. PMID: 23102030
6. Whelton PK, Carey RM, Aronow WS, Casey DE Jr, Collins KJ, Dennison Himmelfarb C, DePalma SM, Gidding S, Jamerson KA, Jones DW, MacLaughlin EJ, Muntner P, Ovbiagele B, Smith SC Jr, Spencer CC, Stafford RS, Taler SJ, Thomas RJ, Williams KA Sr, Williamson JD, Wright JT Jr. 2017 ACC/AHA/AAPA/ABC/ACPM/AGS/APhA/ASH/ASPC/NMA/PCNA Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults: Executive Summary: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Hypertension. 2018 Jun;71(6):1269-1324. doi: 10.1161/HYP.0000000000000066. Epub 2017 Nov 13. Erratum in: Hypertension. 2018 Jun;71(6):e136-e139. Erratum in: Hypertension. 2018 Sep;72(3):e33. PMID: 29133354
7. Jolly H, Freel EM, Isles C. Management of hypertensive emergencies and urgencies: narrative review. Postgrad Med J. 2021 Oct 20:postgradmedj-2021-140899. doi: 10.1136/postgradmedj-2021-140899. Epub ahead of print. PMID: 34670853.
8. Leiba A, Cohen-Arazi O, Mendel L, Holtzman EJ, Grossman E. Incidence, aetiology and mortality secondary to hypertensive emergencies in a large-scale referral centre in Israel (1991-2010). J Hum Hypertens. 2016 Aug;30(8):498-502. doi: 10.1038/jhh.2015.115. Epub 2015 Dec 17. PMID: 26674757.
9. Elliott WJ. Clinical features in the management of selected hypertensive emergencies. Prog Cardiovasc Dis. 2006 Mar-Apr;48(5):316-25. doi: 10.1016/j.pcad.2006.02.004. PMID: 16627047


Add comment